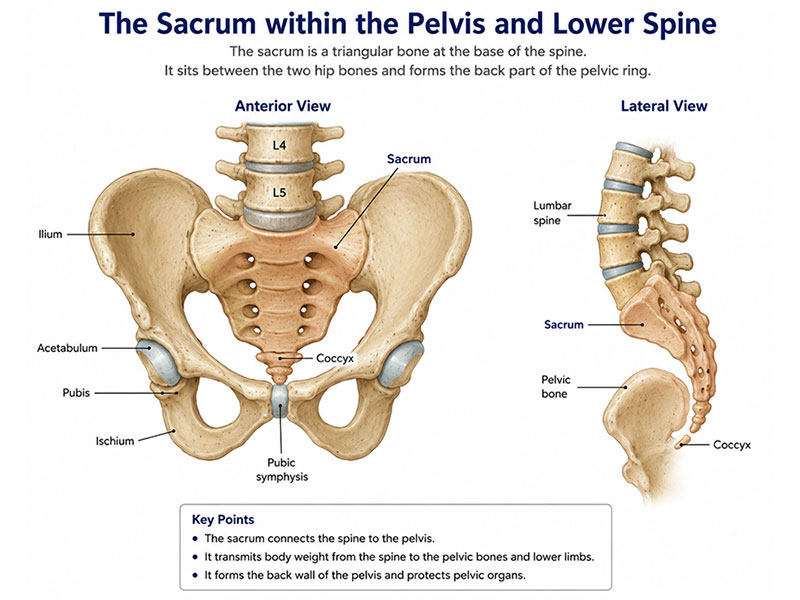
Figure 1. Anatomy of the sacrum within the pelvis and lower spine.
The sacrum connects the lower spine to the pelvis and forms the back of the pelvic ring.
Quick Summary
Key Points at a Glance
- Sacral bone tumors are rare, and many are not cancerous.
- The sacrum supports the spine and protects nerves controlling the legs, bowel, bladder, and sexual function.
- MRI, CT scans, and a carefully planned biopsy are essential before treatment.
- Surgery is recommended only when it offers the best balance between tumor control and preservation of function.
- Modern surgery aims to remove the tumor completely while preserving important nerves whenever oncologically safe.
- Selected tumors, such as chordoma, may also benefit from advanced radiotherapy, including proton beam therapy.
- Recovery involves structured rehabilitation, and many patients regain good mobility and independence.
Reassurance
A diagnosis of a sacral bone tumor can be overwhelming, but treatment has advanced considerably. Careful planning by an experienced multidisciplinary team has significantly improved both survival and functional outcomes.
Understanding the Sacrum and Why It Matters
The sacrum is a large triangular bone located at the base of the spine between the hip bones. It transfers body weight from the spine to the pelvis and legs, making it essential for standing, walking, and maintaining balance.
Unlike most bones, the sacrum contains multiple sacral nerve roots, which control movement of the legs as well as bowel, bladder, and sexual function. Because tumors often grow close to these nerves, treatment requires careful planning to remove the tumor while preserving neurological function whenever possible.
The Sacrum
The sacrum is formed by the fusion of five vertebrae (S1–S5) and serves several important functions:
- Supports body weight
- Connects the spine to the pelvis
- Protects lower spinal nerves
- Provides pelvic stability
- Serves as an attachment for muscles and ligaments
Tumors may originate within the sacrum or spread there from cancers elsewhere in the body.
Sacral Nerve Roots
The level of nerve involvement strongly influences surgical planning and expected recovery.
Whenever possible, surgeons preserve unaffected nerve roots. However, complete removal of a malignant tumor remains the priority when nerve preservation would compromise cancer control.
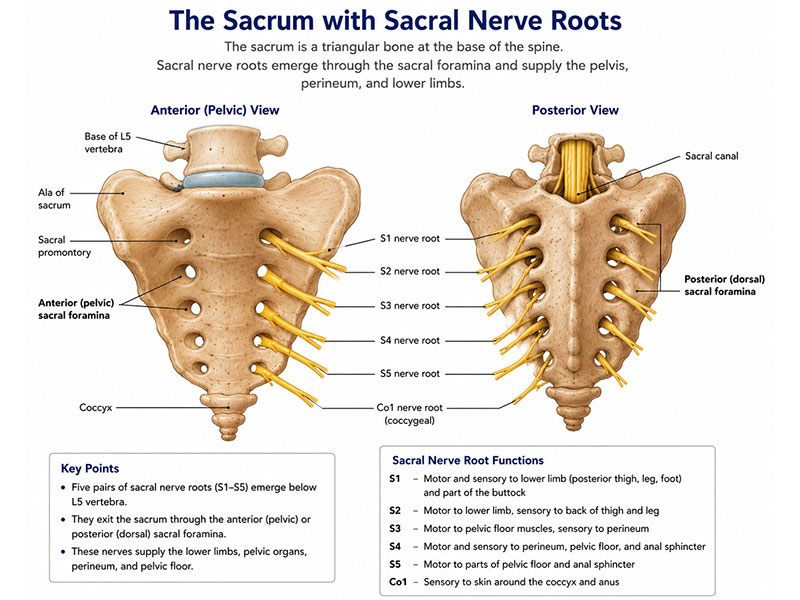
Figure 2. Sacral nerve roots and their relationship to the sacrum.
The sacral nerves pass through openings in the sacrum and control important functions of the legs, pelvis and pelvic floor.
Doctor Explains
Sacral surgery does not always result in paralysis or permanent bowel and bladder dysfunction. Functional outcomes depend largely on which sacral nerve roots are involved and whether they can be safely preserved.
Nearby Organs and Structures
The sacrum lies close to several vital structures, including the:
- Rectum
- Bladder
- Pelvic floor muscles
- Major pelvic blood vessels
- Sacroiliac joints
Large tumors involving these structures may require a combined operation involving orthopaedic oncologists, spine surgeons, colorectal surgeons, vascular surgeons, urologists, or plastic surgeons.
Did You Know?
Complex sacral tumor surgery is often performed by a multidisciplinary surgical team, improving both tumor control and functional recovery.
Clinical Pearl
The level of the tumor within the sacrum is often more important than its size. A small tumor involving the upper sacral nerve roots may have greater functional implications than a larger tumor located lower in the sacrum.
Patient Tip
When discussing surgery, ask your surgeon which sacral nerve roots are involved and what functions are expected to be preserved. This provides a better understanding of the likely recovery and functional outcome.
Reassurance
Every sacral bone tumor is unique. Treatment recommendations are based on detailed imaging, biopsy findings, your overall health, and personal goals. The aim is always to achieve the best possible balance between complete tumor removal and preservation of function.
What Are Sacral Bone Tumors?
A sacral bone tumor is an abnormal growth arising within the sacrum, the triangular bone at the base of the spine. These tumors may originate in the sacral bone itself (primary bone tumors) or spread from cancers elsewhere in the body (metastatic bone tumors).
Although rare, sacral tumors require specialized treatment because of their close relationship to the sacral nerves, pelvic organs, and major blood vessels. They are classified as:
- Benign: Slow-growing, non-cancerous tumors that do not spread.
- Locally aggressive: Tumors that rarely spread but can damage nearby bone and soft tissues.
- Malignant: Cancerous tumors that invade surrounding tissues and may spread to distant organs.
Accurate diagnosis is essential because treatment varies significantly between tumor types. While MRI and CT scans define the tumor’s extent, a biopsy is usually required to confirm the diagnosis before treatment.
Doctor Explains
MRI and CT scans cannot reliably determine whether a sacral tumor is benign or malignant. A carefully planned biopsy performed by a musculoskeletal oncology team is usually essential before deciding on treatment.
Common Sacral Bone Tumors
Several different tumors can affect the sacrum, each requiring a different treatment approach.
Chordoma
Chordoma is the most common primary malignant sacral tumor. It grows slowly but is locally invasive, often involving nearby nerves and pelvic structures. Treatment usually involves wide surgical removal, with selected patients benefiting from advanced radiotherapy such as proton beam therapy.
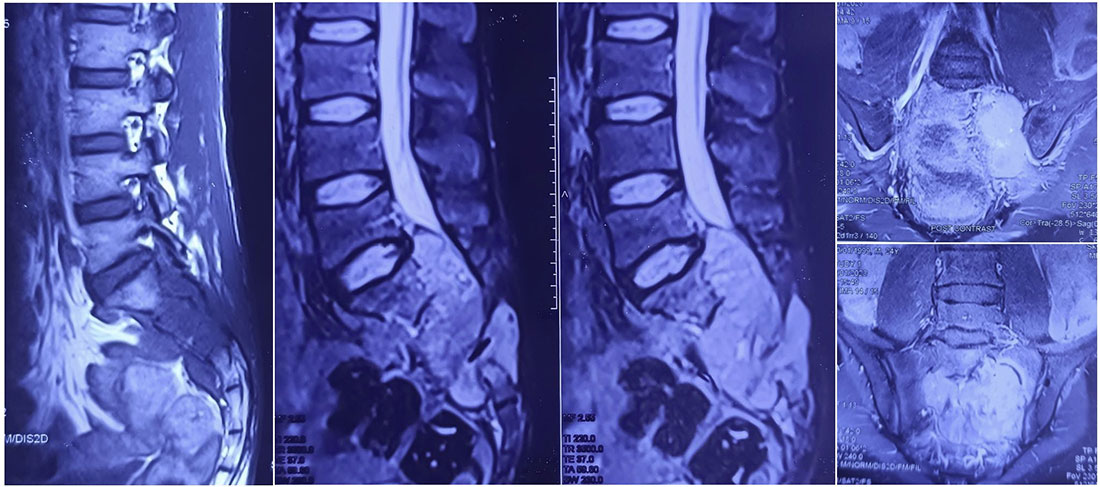
Figure 3. MRI appearance of a sacral chordoma.
MRI shows a large sacral tumor arising from the lower sacrum, typical of a chordoma
Giant Cell Tumor of Bone
A giant cell tumor (GCT) is a locally aggressive tumor that commonly affects young adults. Because it can grow large before causing symptoms, treatment may include:
- Denosumab to shrink the tumor
- Selective arterial embolization in selected cases
- Surgery when indicated
Although GCT rarely spreads, it has a risk of local recurrence.
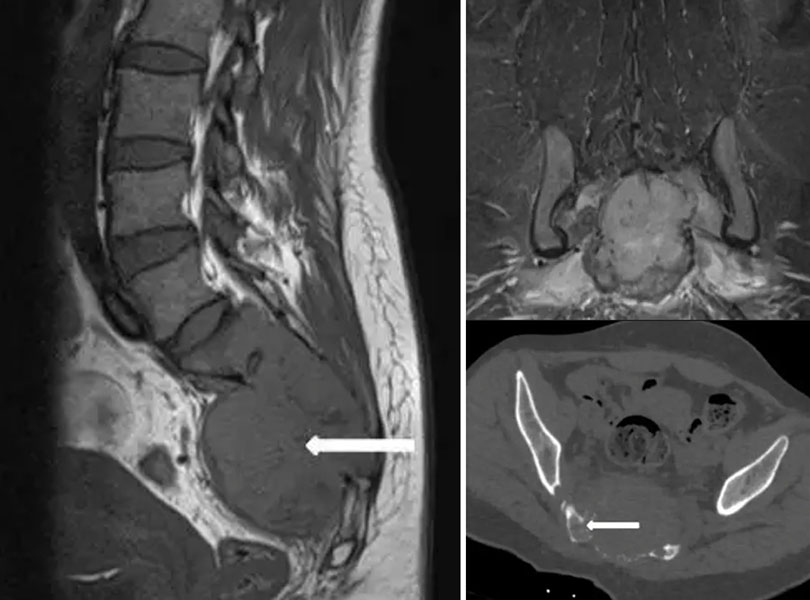
Figure 4. Imaging of a giant cell tumor of the sacrum.
MRI and CT demonstrate an expansile sacral tumor involving the lower sacrum.
Chondrosarcoma
Chondrosarcoma is a malignant cartilage-forming tumor that responds poorly to chemotherapy and conventional radiotherapy. Complete surgical removal offers the best chance of long-term disease control.
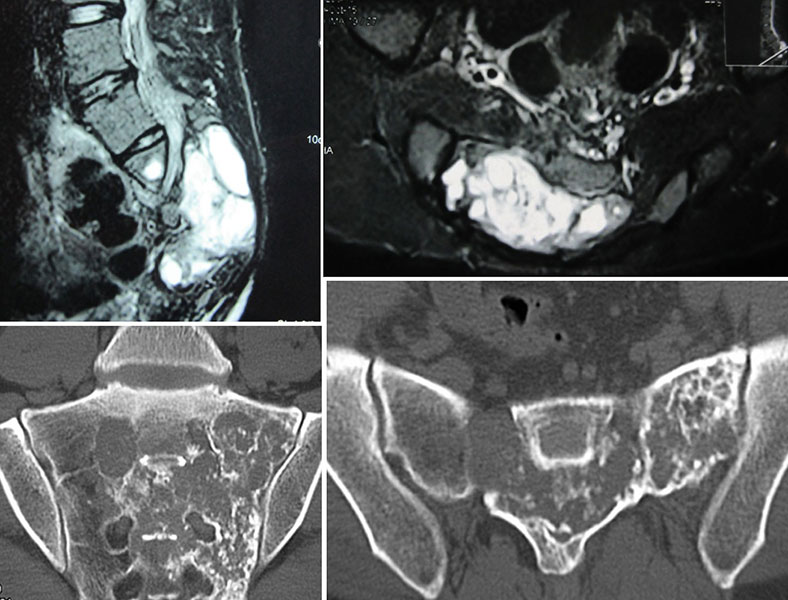
Figure 5. Imaging features of sacral chondrosarcoma.
MRI and CT show a destructive tumor involving the sacrum with extension into the surrounding tissues.
Osteosarcoma
Osteosarcoma is a malignant bone-forming tumor that rarely affects the sacrum. Treatment typically combines chemotherapy and surgery, with radiotherapy used in selected cases.
Ewing Sarcoma
Ewing sarcoma is an aggressive tumor affecting children and young adults. Treatment usually involves chemotherapy, followed by surgery and/or radiotherapy, making its management very different from that of chordoma.
Metastatic Sacral Tumors
The sacrum is also a common site for bone metastases, particularly from cancers of the:
- Breast
- Prostate
- Lung
- Kidney
- Thyroid
Treatment focuses on relieving pain, preserving neurological function and mobility, and controlling the underlying cancer through surgery, radiotherapy, systemic therapy, or a combination of these treatments.
Clinical Pearl
Although many sacral tumors cause similar symptoms, their treatments differ considerably. Establishing the correct diagnosis through biopsy is the most important step in planning treatment.
Doctor Insight
The “best” treatment depends on the tumor diagnosis, not its size alone. Two tumors that appear similar on MRI may require completely different treatment strategies once biopsy results are available.
Did You Know?
Chordoma accounts for nearly half of all primary malignant tumors of the sacrum, making it the most common cancerous tumor in this location.
Reassurance
A diagnosis of a bone tumor does not always mean bone cancer. Many sacral tumors are benign or locally aggressive rather than malignant. Even when cancer is diagnosed, modern surgery, advanced radiotherapy, and multidisciplinary care have significantly improved treatment outcomes.
Symptoms of Sacral Bone Tumors
The symptoms of a sacral bone tumor often develop gradually and can resemble common conditions such as lower back pain, sciatica, or degenerative spine disease, leading to delayed diagnosis. Symptoms depend on the type, size, and location of the tumor, as well as whether it involves the sacral nerve roots or nearby pelvic organs. While some tumors are discovered incidentally on imaging, others present with progressive pain or neurological symptoms requiring prompt evaluation.
Persistent Lower Back or Buttock Pain
Pain is the most common symptom of a sacral bone tumor. Unlike mechanical back pain, tumor-related pain typically:
- Persists for weeks or months
- Gradually worsens over time
- Occurs at night or interrupts sleep
- Does not improve with rest or routine pain medication
- May worsen while sitting due to pressure over the sacrum
Persistent or unexplained back pain should always be evaluated, particularly if it is progressive.
Pain Radiating to the Legs (Sciatica)
Tumors involving the sacral nerve roots may cause symptoms similar to sciatica, including:
- Pain radiating into one or both legs
- Burning or electric shock-like sensations
- Tingling (“pins and needles”)
- Numbness
- Altered sensation in the buttocks, thighs, or feet
Although a slipped disc is the most common cause of sciatica, persistent symptoms that fail to improve warrant further investigation.
Weakness and Difficulty Walking
As the tumor enlarges, it may affect the nerves supplying the legs, leading to:
- Difficulty climbing stairs
- Reduced walking endurance
- Foot weakness or frequent tripping
- Difficulty standing on tiptoes
- Poor balance
These changes usually develop gradually and may initially be subtle.
Bowel Dysfunction
Tumors involving the lower sacral nerves may affect bowel control, causing:
- Constipation
- Difficulty emptying the bowels
- Reduced bowel sensation
- Loss of bowel control in advanced cases
These symptoms generally occur only when the lower sacral nerve roots are significantly involved.
Bladder Dysfunction
Patients may develop:
- Difficulty passing urine
- Weak urinary stream
- Incomplete bladder emptying
- Urinary retention
- Loss of bladder control in advanced disease
Prompt medical assessment is important to prevent urinary complications.
Sexual Dysfunction
The sacral nerves also contribute to sexual function. Depending on the tumor location, patients may experience:
- Erectile dysfunction
- Reduced genital sensation
- Difficulty achieving orgasm
- Pain during sexual activity
Doctor Explains
Not every patient develops bowel, bladder, or sexual dysfunction. These problems depend largely on which sacral nerve roots are affected, and many patients retain normal function when the nerves can be preserved.
Swelling or a Palpable Mass
Because the sacrum lies deep within the pelvis, swelling is uncommon. Larger tumors may cause:
- Fullness over the lower back
- Swelling near the tailbone
- A firm buttock mass
- Discomfort while sitting
Symptoms According to Tumor Location
The location of the tumor often predicts the symptoms.
When Should You Seek Specialist Evaluation?
Although most back pain is not caused by a bone tumor, specialist assessment is recommended if you experience:
- Persistent back or buttock pain lasting more than 4–6 weeks
- Progressive or night pain
- Leg weakness or numbness
- Persistent numbness around the buttocks or groin
- Difficulty controlling bowel or bladder function
- A history of cancer with new sacral pain
- An unexplained sacral lesion detected on imaging
Clinical Pearl
Progressive night pain that does not improve with rest is an important warning sign of a bone tumor and should never be ignored.
Patient Tip
Before your appointment, keep a record of your symptoms, including pain severity, numbness, weakness, and any bowel or bladder changes. This information helps your doctor determine whether further investigations are needed.
Did You Know?
Sacral tumors often grow silently because there is ample space within the pelvis. As a result, they may become quite large before producing obvious symptoms.
Reassurance
Most cases of lower back pain are caused by common conditions such as muscle strain or arthritis—not a sacral bone tumor. However, persistent, progressive, or neurological symptoms should be evaluated promptly so that, if a tumor is present, treatment can begin before significant complications develop.
Diagnosis and Preoperative Evaluation
Accurate diagnosis is essential because many sacral tumors produce symptoms similar to common conditions such as sciatica or degenerative spine disease. The goals of evaluation are to confirm the diagnosis, determine the tumor type, define its extent, assess nerve and organ involvement, detect spread, and plan the safest treatment. Importantly, definitive surgery should not be performed without establishing a diagnosis, except in rare emergencies.
Clinical Assessment
Evaluation begins with a detailed medical history and physical examination.
Your doctor will assess:
- Pain characteristics and duration
- Leg weakness or numbness
- Bowel, bladder, and sexual function
- Previous cancers or surgeries
- Walking pattern, muscle strength, sensation, and reflexes
Although clinical examination identifies neurological deficits, imaging is necessary to accurately define the tumor.
Plain X-rays
X-rays use low-dose radiation to evaluate bones and are often the first imaging study performed.
They may demonstrate:
- Bone destruction
- Abnormal bone formation
- Calcification
- Pathological fractures
However, because the sacrum is surrounded by the pelvis, small sacral tumors are often poorly visualized, making further imaging necessary.
Magnetic Resonance Imaging (MRI)
Magnetic resonance imaging (MRI) uses magnetic fields and radio waves to produce detailed images of bone, nerves, muscles, and other soft tissues. It is the most important investigation for sacral bone tumors.
MRI accurately shows:
- Tumor size
- Sacral nerve involvement
- Extension into muscles and pelvic organs
- Relationship to blood vessels
- Bone marrow involvement
These findings are critical for surgical planning.
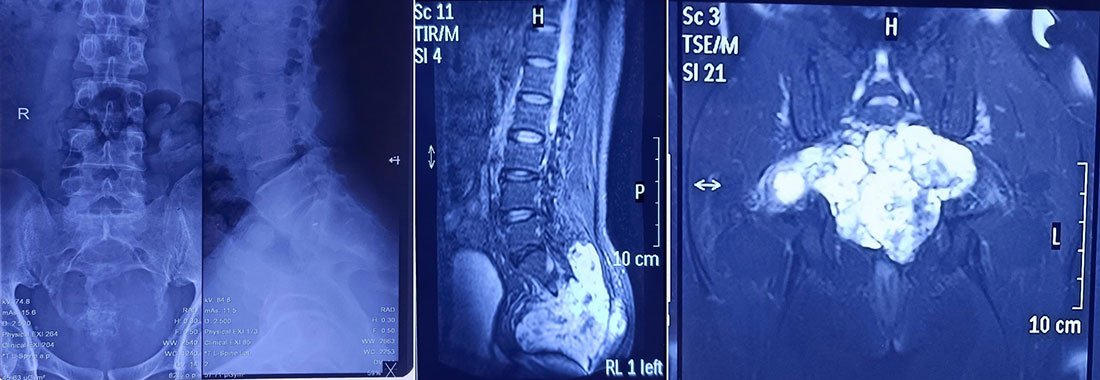
Figure 6. Radiological evaluation of a sacral bone tumor.
X-rays and MRI help assess the location, extent and relationship of the tumor to the sacrum and surrounding structures.
Computed Tomography (CT)
A computed tomography (CT) scan provides excellent visualization of bone anatomy.
CT is particularly useful for assessing:
- Bone destruction
- Cortical bone involvement
- Tumor calcification
- Sacroiliac joint involvement
It is also commonly used to guide core needle biopsies with precision.
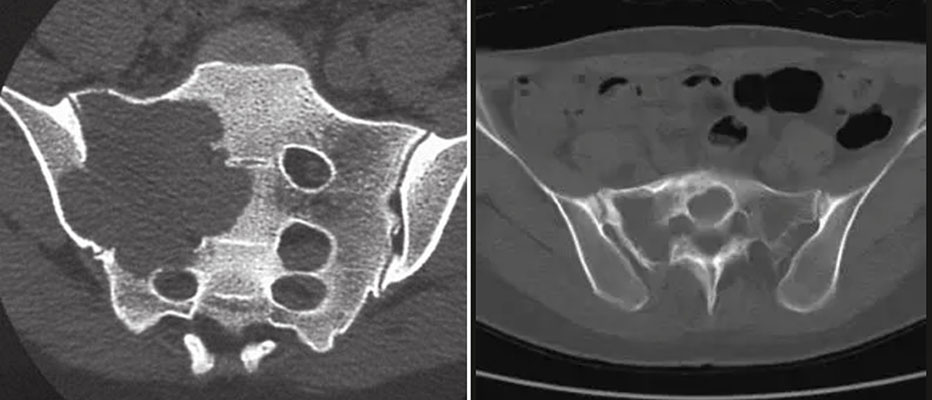
Figure 7. CT evaluation of a sacral tumor.
CT provides detailed information about bone destruction and helps plan sacral tumor surgery.
PET-CT and Bone Scan
Additional imaging may be recommended depending on the diagnosis.
PET-CT (positron emission tomography-computed tomography) evaluates the whole body for metastatic disease, recurrence, or treatment response.
A bone scan detects areas of increased bone activity and may be useful in selected patients with metastatic or multifocal disease.
Why Is a Biopsy Necessary?
A biopsy involves removing a small tissue sample for microscopic examination and is the only reliable method of establishing the exact tumor type.
Most sacral tumors are diagnosed using a CT-guided core needle biopsy, which is accurate and minimally invasive.
Ideally, the biopsy should be performed at the same specialist center that will undertake definitive surgery, as improper biopsy placement can complicate future treatment.
Doctor Explains
A properly planned biopsy has an extremely low risk of spreading tumor cells and provides essential information that guides the choice of surgery, radiotherapy, or chemotherapy.
Staging: Has the Tumor Spread?
For malignant tumors, additional investigations determine whether the disease has spread.
These may include:
- CT scan of the chest
- PET-CT
- Additional MRI or CT scans
- Routine blood tests
Staging helps the multidisciplinary team determine the most appropriate treatment plan and estimate prognosis.
Clinical Pearl
MRI should ideally be performed before biopsy, as it provides the most accurate assessment of the tumor before tissue changes caused by biopsy occur.
🚩 Red Flag
Never perform an unplanned excision of a sacral lesion without appropriate imaging and biopsy. Inadequate planning may compromise future surgery and increase the risk of recurrence.
Patient Tip
Ask whether your biopsy will be performed by the same multidisciplinary team planning your surgery. Coordinated care helps optimize both diagnosis and treatment.
Did You Know?
Imaging shows where the tumor is and how far it extends, but only a biopsy can determine exactly what type of tumor it is.
Reassurance
Waiting for imaging and biopsy results can be difficult, but these investigations are essential for choosing the safest and most effective treatment. A carefully planned diagnosis significantly improves the chances of successful long-term outcomes.
Treatment Planning
Treatment for a sacral bone tumor is individualized because no single approach is appropriate for every patient. The treatment plan depends on the tumor type, its location within the sacrum, involvement of nearby nerves and organs, and the patient’s overall health and functional goals.
The main aims of treatment are to:
- Remove or control the tumor
- Preserve neurological function whenever oncologically safe
- Maintain pelvic stability
- Relieve pain
- Maximize long-term quality of life
Treatment decisions are best made by a multidisciplinary team (MDT) at a specialist bone tumor center.
The Multidisciplinary Team (MDT)
Sacral tumors often require input from several specialists, including:
- Orthopaedic oncologist
- Spine surgeon
- Musculoskeletal radiologist
- Pathologist
- Radiation oncologist
- Medical oncologist
- Plastic or reconstructive surgeon (when required)
- Rehabilitation physician and physiotherapist
The MDT reviews imaging, biopsy findings, and the patient’s overall condition to develop the safest and most effective treatment plan.
Factors Influencing Treatment
Several factors influence treatment decisions.
Tumor Type
The diagnosis largely determines treatment.
- Chordoma: Surgery, often combined with advanced radiotherapy.
- Giant cell tumor: Medication (such as denosumab), surgery, or both.
- Ewing sarcoma: Chemotherapy combined with local treatment.
- Metastatic tumors: Individualized treatment based on the primary cancer.
Tumor Location and Sacral Level
The location of the tumor affects:
- The type of surgery required
- Whether sacral nerve roots can be preserved
- The need for pelvic reconstruction
- Expected functional outcomes
Tumor Extent
Treatment planning also considers involvement of:
- Sacroiliac joints
- Pelvic organs
- Major blood vessels
- Adjacent muscles
- Lumbosacral junction
More extensive tumors often require combined surgery by multiple specialists.
Patient Factors
Treatment is also influenced by:
- Age and overall health
- Existing neurological function
- Previous surgery or radiotherapy
- Functional requirements
- Personal treatment goals
Shared decision-making ensures that patients understand the expected benefits and potential risks of each treatment option.
TABLE – Factors Influencing Treatment Planning
Doctor Insight
Treatment is determined primarily by the biological behavior of the tumor, not simply its size or appearance on imaging.
Clinical Pearl
A carefully planned multidisciplinary approach is one of the most important factors influencing successful long-term outcomes.
Patient Tip
Ask whether your case has been discussed at a multidisciplinary tumor board. Complex sacral tumors are best managed after review by specialists from multiple disciplines.
Reassurance
Although treatment planning may take several days after imaging and biopsy, this allows specialists to recommend the most appropriate treatment tailored to your individual situation.
When Is Surgery Recommended?
Not every sacral bone tumor requires surgery. The decision depends on the diagnosis, symptoms, expected benefits, and potential risks.
Benign Tumors
Small, asymptomatic benign tumors may be monitored with periodic imaging.
Surgery is considered when the tumor:
- Causes persistent pain
- Continues to grow
- Weakens the bone
- Compresses nearby nerves
Malignant Tumors
For most primary malignant sacral tumors, surgery offers the best chance of long-term local control.
The goals are to:
- Remove the tumor completely with adequate margins
- Minimize the risk of recurrence
- Preserve neurological function whenever possible
Depending on the diagnosis, surgery may be combined with chemotherapy or radiotherapy.
Metastatic Disease
Surgery for metastatic tumors is usually performed to:
- Relieve pain
- Maintain pelvic stability
- Treat or prevent nerve compression
- Improve mobility and quality of life
Many patients also receive radiotherapy or systemic cancer treatment.
TABLE – Common Indications for Surgery
Doctor Explains
Surgery is recommended only when its expected benefits outweigh the risks. In selected patients, particularly those with advanced metastatic disease or unresectable tumors, radiotherapy or other treatments may provide better outcomes than surgery alone.
Clinical Pearl
The objective of surgery is to achieve the best balance between complete tumor control and preservation of neurological function and quality of life.
🚩 Red Flag
Progressive leg weakness or new bowel and bladder dysfunction requires urgent specialist assessment, as delayed treatment may lead to permanent neurological damage.
Reassurance
Recommending surgery does not necessarily mean the condition is incurable or life-threatening. In many cases, surgery is performed to preserve function, relieve symptoms, and prevent future complications.
Types of Sacral Tumor Surgery
Surgery for sacral bone tumors is highly specialized and aims to completely remove the tumor while preserving as much nerve function and pelvic stability as possible. The type of operation depends on the tumor’s location, size, involvement of the sacral nerve roots, and whether nearby organs or joints are affected.
Unlike many other bone tumors, surgery of the sacrum requires careful planning because the sacral nerves control walking, bladder, bowel, and sexual function. Whenever oncologically safe, surgeons strive to preserve these nerves without compromising tumor removal.
Partial Sacrectomy
A partial sacrectomy involves removing only the portion of the sacrum affected by the tumor while preserving the remaining sacral bone and nerve roots.
This procedure is suitable for tumors confined to the lower or lateral sacrum.
Potential advantages include:
- Better preservation of walking ability
- Lower risk of bowel and bladder dysfunction
- Improved pelvic stability
- Faster rehabilitation
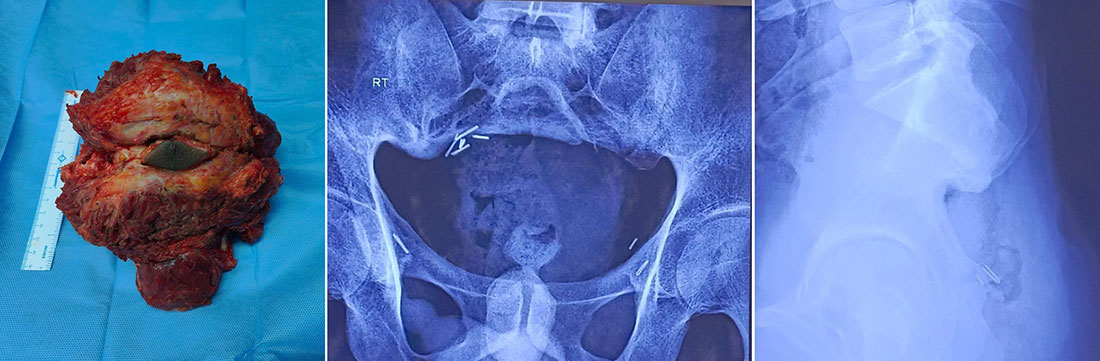
Figure 8. Partial sacrectomy for a sacral bone tumor.
The tumor is removed along with the involved portion of the sacrum while preserving as much normal bone and nerve function as possible.
Total Sacrectomy
A total sacrectomy involves removal of the entire sacrum and is reserved for extensive tumors involving most or all of the sacral bone.
Because this operation removes the connection between the spine and pelvis, complex spinopelvic reconstruction is usually required to restore stability.
Although technically demanding, total sacrectomy may provide the best chance of long-term tumor control in selected patients with large primary malignant tumors.
Figure 9. Sacral chordoma before surgery and postoperative reconstruction.
Imaging demonstrates a large sacral tumor and the postoperative appearance following tumor removal.
En Bloc Tumor Resection
For most primary malignant sacral tumors, surgeons aim to remove the tumor en bloc, meaning the entire tumor is removed in one piece with a surrounding margin of healthy tissue.
This technique helps:
- Reduce the risk of local recurrence
- Avoid tumor spillage
- Improve long-term oncological outcomes
Whenever possible, the tumor is removed without cutting through it.
Nerve Preservation
One of the most important aspects of sacral tumor surgery is preserving the sacral nerve roots whenever it is safe to do so.
The ability to preserve nerves depends on whether they are involved by the tumor.
Preserving more nerve roots generally results in better:
- Walking ability
- Bladder control
- Bowel control
- Sexual function
In some cases, sacrificing one or more nerve roots is necessary to achieve complete tumor removal.
Doctor Explains
Preserving nerves is important, but complete removal of a malignant tumor takes priority. Your surgeon carefully balances cancer control with maintaining the best possible quality of life.
Pelvic and Spinopelvic Reconstruction
After removing large sacral tumors, reconstruction may be required to restore stability between the spine and pelvis.
Reconstruction may involve:
- Metal rods and screws
- Titanium cages or custom implants
- Bone grafts
- Soft tissue reconstruction using muscle flaps
Not every patient requires reconstruction. The need depends on the amount of bone removed and whether the pelvic ring remains stable.
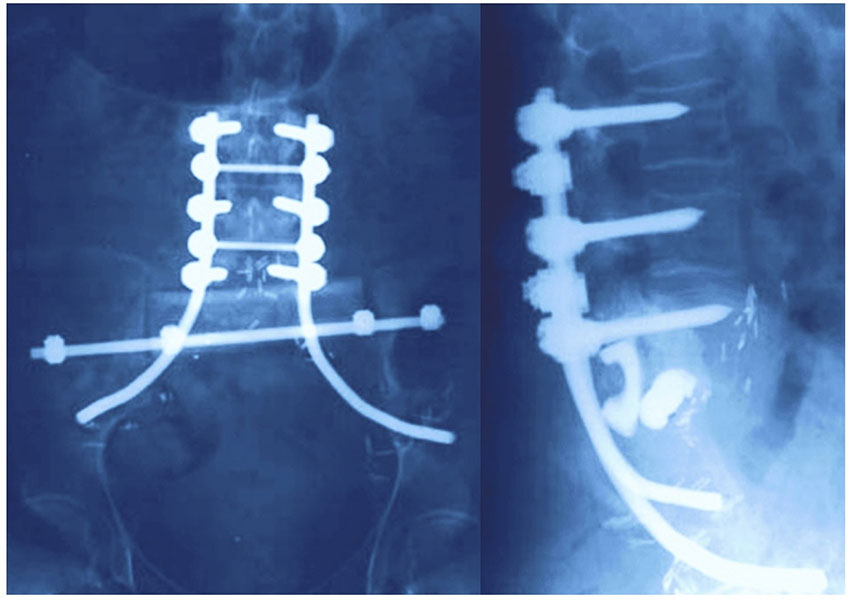
Figure 10. Spinal and pelvic reconstruction following sacral tumor surgery.
Postoperative X-rays demonstrate fixation used to restore stability after extensive sacral tumor resection.
Clinical Pearl
The level of sacral nerve preservation is often the strongest predictor of postoperative bowel, bladder, and walking function.
Patient Tip
Before surgery, ask your surgeon:
- Which sacral nerve roots are involved?
- Will reconstruction be required?
- What functional changes should I expect after surgery?
Did You Know?
Modern techniques such as 3D surgical planning, patient-specific cutting guides, computer navigation, and custom-made implants have significantly improved the precision and safety of complex sacral tumor surgery in specialized centers.
Reassurance
Sacral tumor surgery is among the most complex procedures in orthopaedic oncology, but careful preoperative planning and multidisciplinary care have greatly improved outcomes. Your surgical team will discuss the expected benefits, risks, and likely functional recovery before treatment.
Recovery and Rehabilitation After Sacral Tumor Surgery
Recovery after sacral tumor surgery varies depending on the extent of surgery, nerve preservation, reconstruction performed, and the patient’s overall health. While recovery may take several months, a structured rehabilitation program helps most patients regain independence and improve their quality of life.
Hospital Stay
Most patients remain in the hospital for 1–3 weeks, depending on the complexity of surgery and postoperative recovery.
During this period, the healthcare team focuses on:
- Pain control
- Wound care
- Prevention of blood clots and infections
- Early mobilization
- Monitoring bowel and bladder function
Physiotherapy and Rehabilitation
Rehabilitation begins soon after surgery.
A physiotherapist helps patients gradually:
- Sit, stand, and walk safely
- Improve muscle strength and balance
- Restore mobility
- Learn safe movement techniques after reconstruction
Patients with significant nerve loss may require walking aids or braces during recovery.
Bowel and Bladder Recovery
Recovery of bowel and bladder function depends largely on which sacral nerve roots were preserved.
Some patients regain normal function, while others may require:
- Bladder training
- Intermittent catheterization
- Bowel management programs
- Specialist rehabilitation support
Your healthcare team will provide individualized guidance based on your neurological recovery.
Returning to Daily Activities
Most patients gradually resume daily activities over the following weeks to months.
Return to work depends on:
- Type of surgery
- Physical demands of the job
- Functional recovery
- Need for additional treatments such as chemotherapy or radiotherapy
Heavy lifting and high-impact activities should be avoided until cleared by the treating surgeon.
Clinical Pearl
Early rehabilitation and regular physiotherapy play a vital role in improving mobility, reducing complications, and maximizing long-term function after sacral tumor surgery.
Patient Tip
Recovery is gradual. Setting realistic goals and actively participating in your rehabilitation program can significantly improve your functional outcome.
Reassurance
Although recovery after sacral surgery can be challenging, many patients regain good mobility and independence with comprehensive rehabilitation and ongoing support from their multidisciplinary care team.
Potential Risks and Complications of Sacral Tumor Surgery
Sacral tumor surgery is a complex procedure, and like any major operation, it carries potential risks. The likelihood of complications depends on the size and location of the tumor, the extent of surgery, nerve preservation, reconstruction performed, and the patient’s overall health. Careful preoperative planning and experienced multidisciplinary care help minimize these risks.
Neurological Complications
Because the sacral nerve roots control leg function, bowel, bladder, and sexual function, temporary or permanent neurological deficits may occur if these nerves are involved by the tumor or need to be removed.
Possible complications include:
- Leg weakness
- Numbness
- Bowel dysfunction
- Bladder dysfunction
- Sexual dysfunction
Wound Problems and Infection
The sacral region has limited soft tissue coverage, making wound healing more challenging than in many other parts of the body.
Potential complications include:
- Delayed wound healing
- Surgical site infection
- Wound breakdown
- Need for additional reconstructive procedures
Plastic surgical muscle flaps are sometimes used to reduce these risks.
Bleeding
Sacral tumors are often located close to major pelvic blood vessels and can be highly vascular.
To reduce blood loss, your surgical team may use:
- Preoperative embolization for selected tumors
- Blood conservation techniques
- Intraoperative blood transfusion when required
Implant or Reconstruction-related Complications
Patients undergoing spinopelvic reconstruction may experience:
- Implant loosening
- Hardware failure
- Non-union of bone grafts
- Need for revision surgery
Fortunately, these complications are uncommon with modern surgical techniques and appropriate follow-up.
Tumor Recurrence
Despite successful surgery, some tumors may recur locally, particularly if complete removal with adequate margins is not possible.
Regular follow-up with clinical examination and imaging is essential for early detection of recurrence.
Doctor Explains
Although complications are possible, they are carefully discussed before surgery. The surgical plan is designed to maximize tumor control while minimizing the risk of long-term disability.
Clinical Pearl
Surgery performed at specialized musculoskeletal oncology centers is associated with better oncological outcomes and lower complication rates for complex sacral tumors.
Patient Tip
Attend all scheduled follow-up visits, as early recognition of complications or recurrence allows timely treatment and improves long-term outcomes.
Reassurance
Reading about potential complications can be overwhelming, but most patients do not experience every complication listed. Your surgeon will discuss the specific risks that apply to your individual condition, helping you make an informed treatment decision.
Frequently Asked Questions (FAQs)
Can a sacral bone tumor be benign?
Yes. Not all sacral tumors are cancerous. Benign tumors such as osteoid osteoma, osteoblastoma, aneurysmal bone cyst, and giant cell tumor can occur in the sacrum. However, because benign and malignant tumors may appear similar on imaging, a biopsy is often required to establish the diagnosis.
Is surgery always necessary?
No. Treatment depends on the tumor type, symptoms, and extent of disease. Some benign tumors can be monitored, while others may be treated with medication or radiotherapy. Surgery is recommended when it offers the best chance of tumor control, pain relief, or preservation of function.
Will I be able to walk after sacral tumor surgery?
Many patients are able to walk independently after recovery. Walking ability largely depends on which sacral nerve roots are preserved, the extent of surgery, and participation in rehabilitation. Your surgeon will discuss the expected functional outcome based on your individual case.
Will surgery affect bowel or bladder function?
It can, particularly if the lower sacral nerve roots (S2–S5) are involved by the tumor or need to be removed. Whenever oncologically safe, surgeons aim to preserve these nerves to maintain bowel and bladder function.
How long does recovery take?
Most patients spend 1–3 weeks in the hospital, while complete recovery may take several months. Physiotherapy and rehabilitation are essential for regaining strength, mobility, and independence.
Can sacral bone tumors come back after treatment?
Some tumors, especially malignant tumors or those that cannot be completely removed, may recur. Regular follow-up with clinical examination and imaging helps detect recurrence early, when further treatment is most effective.
Is a biopsy safe?
Yes. A CT-guided core needle biopsy performed at a specialist bone tumor center is a safe and reliable procedure. It provides the diagnosis needed to plan the most appropriate treatment.
When should I seek a second opinion?
A second opinion is advisable if you have been diagnosed with a rare sacral tumor, advised to undergo major surgery, or if there is uncertainty regarding the diagnosis or treatment plan. Complex sacral tumors are best managed at specialist musculoskeletal oncology centers.
Medical Disclaimer
The information provided on this page is intended for educational purposes only and should not replace professional medical advice, diagnosis, or treatment. Every sacral bone tumor is unique, and treatment decisions should be based on an individual evaluation by a qualified orthopaedic oncologist or musculoskeletal tumor specialist. If you have persistent symptoms or have been diagnosed with a sacral bone tumor, consult your treating specialist to discuss the most appropriate management plan for your condition.
References
- Fiani B, Runnels J, Rose A, Kondilis A, Wong A, Musch BL. Clinical manifestations, classification, and surgical management of sacral tumors and the need for personalized approach to sacrectomy. Surg Neurol Int. 2021;12:209.
- Puri A, Agarwal MG, Shah M, et al. Decision making in primary sacral tumors. Spine J. 2009;9(5):396-403.
- Rose PS, Houdek MT. Team Approach: Oncologic Sacrectomy. JBJS Rev. 2020;8(9):e1900226.
- Bederman SS, Shah KN, Hassan JM, Hoang BH, Kiester PD, Bhatia NN. Surgical techniques for spinopelvic reconstruction following total sacrectomy: a systematic review. Eur Spine J. 2014;23(2):305-319.
 +91 93558 33005

