Quick Summary
A hip or pelvic bone tumor is an abnormal growth that develops in the bones forming the hip joint or pelvis. These tumors may be benign (non-cancerous) or malignant (cancerous). Although malignant tumors are uncommon, they require specialized evaluation and treatment because of the pelvis’s complex anatomy and its proximity to major nerves, blood vessels, and internal organs.
Modern treatment has changed dramatically over the past few decades. Advances in medical imaging, chemotherapy, surgical techniques, and customized reconstruction now allow limb salvage surgery—removing the tumor while preserving the leg—in many patients who would previously have required amputation.
Successful treatment is about much more than removing the tumor. Surgeons must also restore pelvic stability, preserve hip function whenever possible, and help patients return to independent daily activities. Every treatment plan is individualized based on the type of tumor, its location, whether the hip joint is involved, and the condition of the surrounding muscles, nerves, and blood vessels.
This guide explains:
- How hip and pelvic bone tumors are diagnosed
- When surgery is recommended
- What limb salvage surgery involves
- Different pelvic reconstruction options
- Recovery and rehabilitation
- What patients and families can realistically expect after treatment
Quick Summary Box
- Most hip and pelvic bone tumors are not cancerous, but every persistent bone lesion requires proper evaluation.
- Modern limb salvage surgery can preserve the leg in many patients with malignant tumors.
- Surgery should always be planned by a multidisciplinary bone tumor team, including an orthopaedic oncologist.
- Recovery depends not only on tumor removal but also on the type of reconstruction and postoperative rehabilitation.
Reassurance Box
A diagnosis of a hip or pelvic bone tumor can be overwhelming, but it does not automatically mean loss of the leg. With careful planning and modern reconstructive techniques, many patients achieve good pain relief, independent mobility, and an excellent quality of life.
Understanding the Hip & Pelvic Anatomy
Understanding the anatomy of the hip and pelvis makes it easier to appreciate why surgery in this region is more complex than surgery for tumors in many other bones.
The pelvis is a ring-shaped structure at the base of the spine that connects the upper body to the legs. It supports body weight while standing and walking, protects important organs such as the bladder and reproductive organs, and serves as an attachment point for many powerful muscles.
The pelvis is made up of three bones that fuse together during growth:
- Ilium – the broad, wing-shaped upper part of the pelvis.
- Ischium – the lower back portion that supports the body while sitting.
- Pubis – the front portion of the pelvic ring.
Together, these bones form the acetabulum, a cup-shaped socket that forms the hip joint.
The hip joint is a ball-and-socket joint, where the rounded head of the femur (thigh bone) fits into the acetabulum. This arrangement provides both stability and a wide range of movement, allowing activities such as walking, climbing stairs, sitting, and bending.
Tumors may arise in any part of the pelvis or the upper end of the femur. Their location has a major influence on surgical planning. For example, a tumor confined to the iliac wing may require a very different operation from one involving the acetabulum, where reconstruction of the hip joint may become necessary.
Unlike tumors in the arm or lower leg, pelvic tumors are often close to major blood vessels, important nerves (such as the sciatic nerve), and abdominal or pelvic organs. Surgeons must therefore balance two equally important goals:
- Completely removing the tumor with a safe margin of healthy tissue.
- Preserving as much normal anatomy and function as possible.
This careful planning is one reason why pelvic bone tumor surgery is performed in specialized musculoskeletal oncology centers.
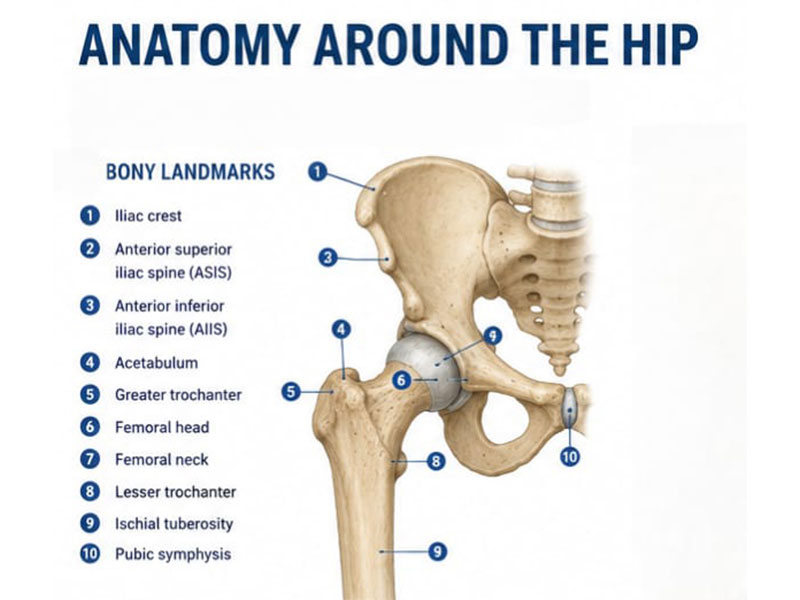
Figure 1. Normal anatomy of the hip and pelvis, showing the key bones and anatomical landmarks relevant to hip and pelvic bone tumor surgery.
Illustration showing:
- Ilium
- Ischium
- Pubis
- Acetabulum
- Sacrum
- Sacroiliac joint
- Proximal femur
- Hip joint
Did You Know?
The pelvis contains some of the body’s largest blood vessels and major nerves that control movement and sensation in the leg. This is one reason why pelvic bone tumor surgery requires careful preoperative planning and is usually performed by specialized orthopaedic oncology teams.
Clinical Pearl
The location of a pelvic tumor often influences surgical planning more than its size. A relatively small tumor involving the hip socket may require a more complex reconstruction than a larger tumor located away from the joint.
Doctor Explains
Patients often use the terms “hip” and “pelvis” interchangeably. Although they are closely connected, they are not the same. The pelvis is the bony ring that supports the body, while the hip joint is where the thigh bone meets the pelvis. Understanding which structure is affected helps explain why treatment varies from one patient to another.
Symptoms of Hip & Pelvic Bone Tumors
The symptoms of a hip or pelvic bone tumor vary depending on its size, location, and whether it is benign or malignant. Because these tumors are uncommon, they are sometimes mistaken for more familiar conditions such as arthritis, muscle strain, or lower back pain.
The most common symptom is persistent pain. Unlike pain from a minor injury, tumor-related pain usually does not improve with rest and may gradually worsen over weeks or months. Some patients notice pain that becomes more troublesome at night or interferes with sleep.
As the tumor grows, it may weaken the bone, leading to discomfort while walking, climbing stairs, or standing for long periods. Tumors involving the acetabulum or upper femur can alter the mechanics of the hip joint, resulting in a limp or reduced range of movement.
Some patients develop a swelling or lump, particularly when the tumor extends into the surrounding soft tissues. However, many pelvic tumors remain hidden deep within the body and may not produce a visible swelling.
In advanced cases, the weakened bone may break with minimal trauma, a condition known as a pathological fracture. Unlike a normal fracture caused by significant injury, a pathological fracture occurs because the bone has been weakened by disease.
Occasionally, a tumor may press on nearby nerves, causing symptoms such as numbness, tingling, weakness, or pain radiating into the leg.
Common Symptoms
- Persistent hip or pelvic pain
- Pain that gradually worsens over time
- Night pain
- Difficulty walking or limping
- Reduced hip movement
- Swelling or a deep pelvic mass
- Pain after minimal injury
- Unexplained pathological fracture
- Numbness or weakness due to nerve compression
Many of these symptoms can also occur with common conditions such as arthritis. The difference is that tumor-related symptoms often continue despite routine treatment or become progressively worse.
Patient Tip
Most hip pain is not caused by a bone tumor. However, persistent or unusual symptoms deserve proper assessment. Early evaluation often leads to earlier diagnosis and a wider range of treatment options.
Reassurance Box
Hip and pelvic pain is far more commonly caused by arthritis, muscle injuries, or spine problems than by bone tumors. Nevertheless, persistent pain that behaves differently from typical arthritis should be investigated so that any serious condition can be identified or excluded promptly.
Types of Hip & Pelvic Bone Tumors
Not all hip and pelvic bone tumors are cancerous. They range from benign (non-cancerous) lesions that may only require observation or limited surgery to malignant (cancerous) tumors that require specialized treatment.
The exact diagnosis is one of the most important factors determining whether surgery is needed, whether chemotherapy or radiotherapy is recommended, and what type of reconstruction may be required.
Rather than focusing on the tumor’s size alone, your treatment team considers its biological behavior, location, and relationship to the hip joint and surrounding structures.
Benign Bone Tumors
Benign tumors do not spread to other parts of the body, but some can weaken bone, destroy the hip joint, or behave aggressively enough to require surgery.
Common examples include:
- Giant Cell Tumor
- Osteochondroma
- Chondroblastoma
- Aneurysmal Bone Cyst
➡ Read more: Giant Cell Tumor of Bone, Osteochondroma, Chondroblastoma, and Aneurysmal Bone Cyst.
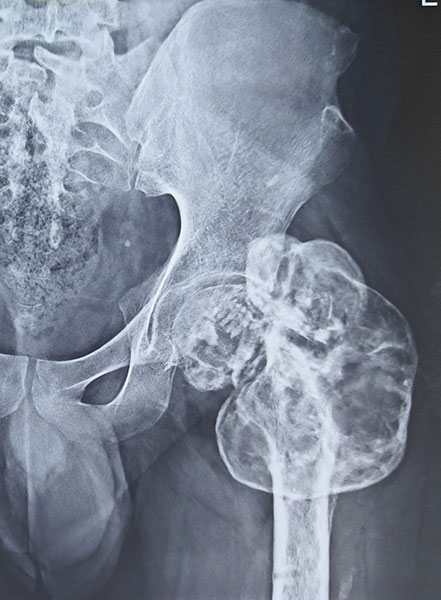
Figure 2. Giant cell tumor of the proximal femur involving the hip, with a large destructive bone lesion
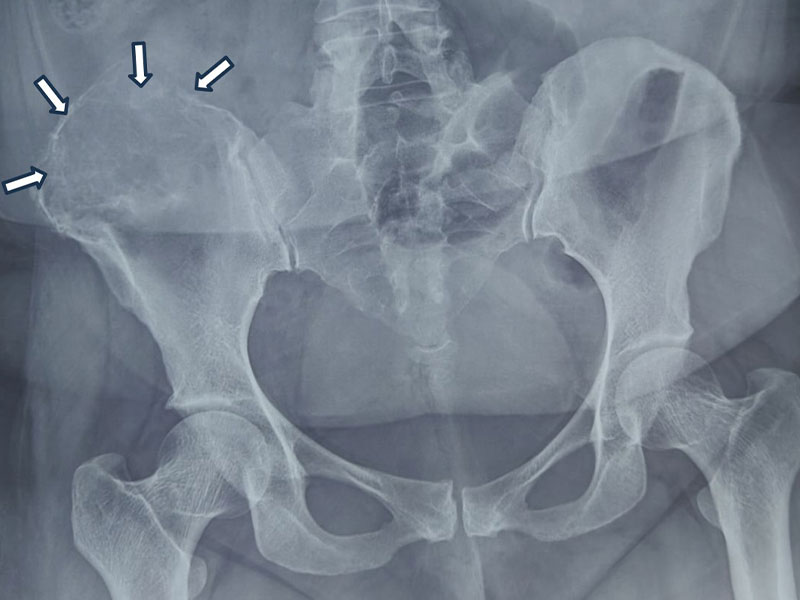
Figure 3. Giant cell tumor of the pelvis involving the iliac bone, shown on X-ray and MRI.
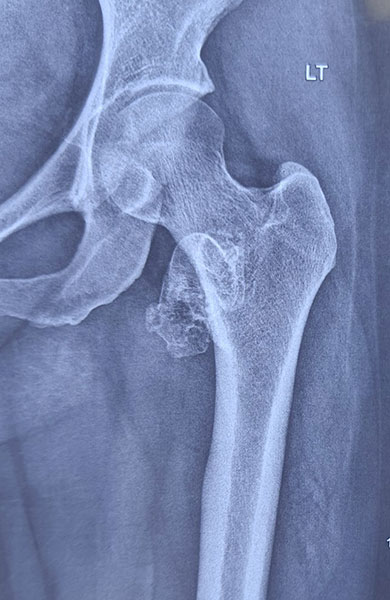
Figure 4. Osteochondroma of the proximal femur, a benign bone tumor arising near the hip.
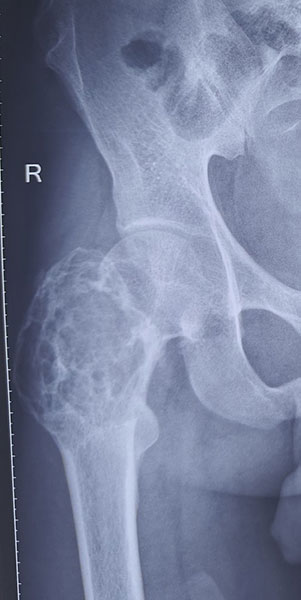
Figure 5. Aneurysmal bone cyst of the proximal femur, showing an expansile bone lesion around the hip.
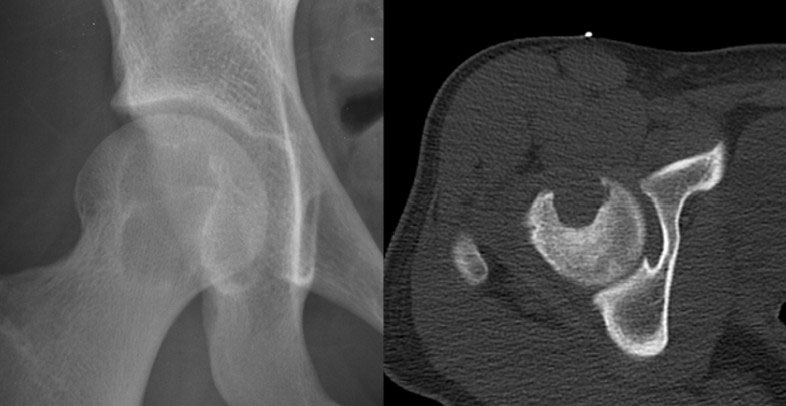
Figure 6. Chondroblastoma of the femoral head, a rare benign bone tumor involving the hip joint.
Malignant Bone Tumors
Primary bone cancers require treatment by a multidisciplinary musculoskeletal oncology team.
The most common malignant tumors around the pelvis include:
- Osteosarcoma
- Chondrosarcoma
- Ewing Sarcoma
➡ Read more: Osteosarcoma, Chondrosarcoma, and Ewing Sarcoma.
Metastatic Bone Disease
Sometimes a tumor found in the pelvis has spread from another cancer elsewhere in the body, such as the breast, prostate, lung, kidney, or thyroid.
Treatment depends on both the bone lesion and the primary cancer.
➡ Read more: Bone Metastasis
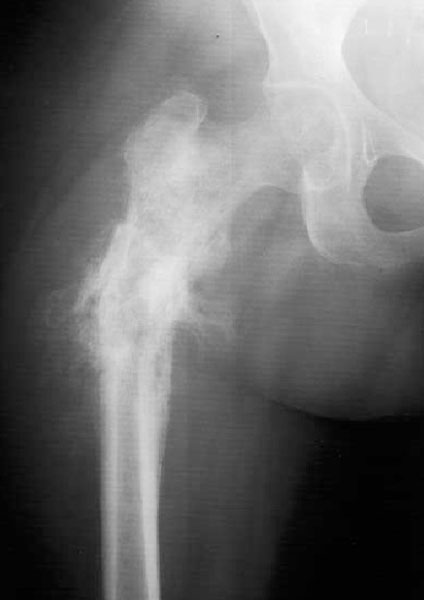
Figure 7. Osteosarcoma of the proximal femur, showing an aggressive bone tumor around the hip.
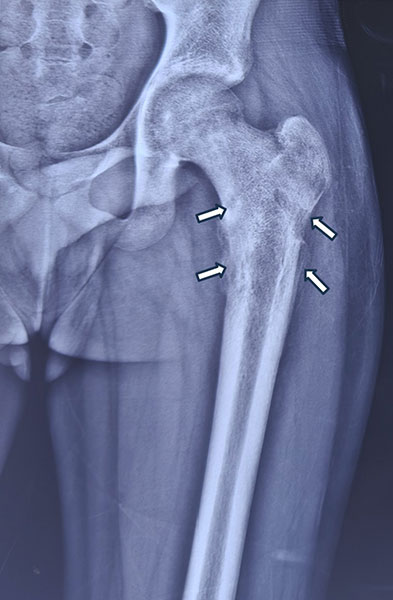
Figure 8. Ewing sarcoma of the proximal femur with an extensive tumor involving the bone and surrounding tissues.
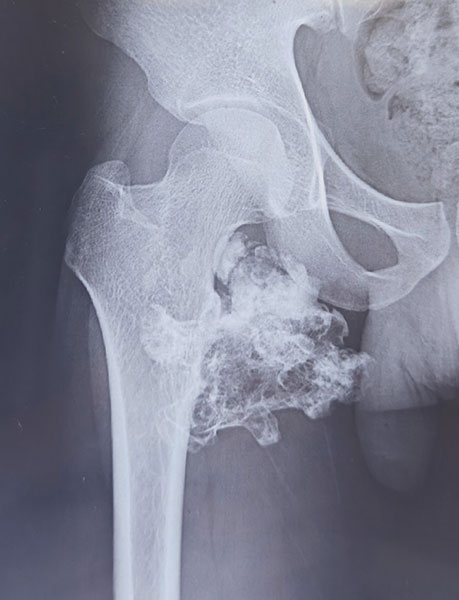
Figure 9. Chondrosarcoma of the proximal femur, showing a destructive cartilage-forming bone tumor.
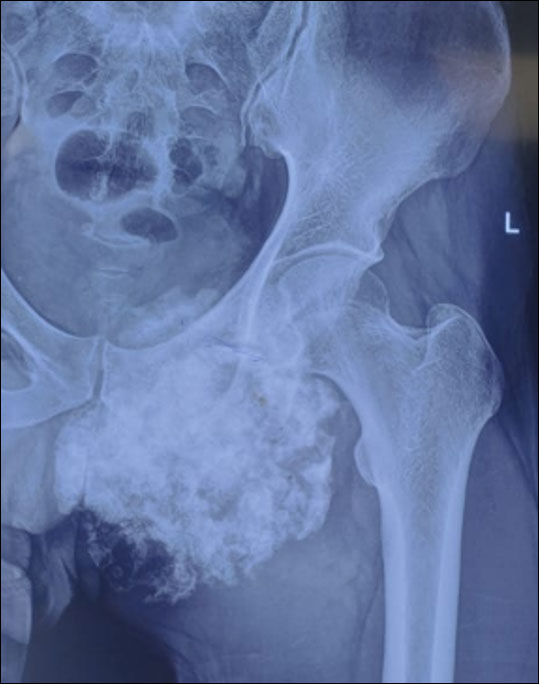
Figure 10. Chondrosarcoma of the pelvis presenting as an extensive bone tumor around the hip.
Metastatic Bone Disease
Sometimes a tumor found in the pelvis has spread from another cancer elsewhere in the body, such as the breast, prostate, lung, kidney, or thyroid.
Treatment depends on both the bone lesion and the primary cancer.
➡ Read more: Bone Metastasis
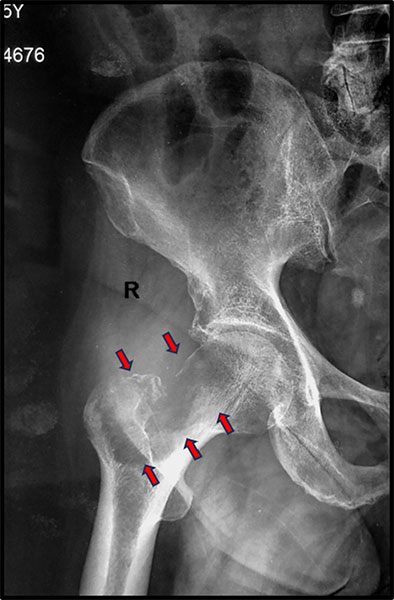
Figure 11. Metastatic bone tumor involving the proximal femur, a common location for secondary bone cancer.
Common Hip & Pelvic Bone Tumors
Clinical Pearl
Treatment is guided by the type and biological behavior of the tumor, not simply by how large it appears on imaging.
Reassurance
Being told you have a “bone tumor” does not necessarily mean you have bone cancer. Many tumors affecting the hip and pelvis are benign, and even malignant tumors often have successful treatment options when diagnosed and managed appropriately.
How Are Hip & Pelvic Bone Tumors Diagnosed?
Diagnosing a hip or pelvic bone tumor requires careful evaluation to determine:
- What type of tumor is present
- Whether it is benign or malignant
- Whether it has involved the hip joint
- Whether it has spread beyond the bone
This usually involves a combination of clinical examination, imaging studies, and biopsy.
Rather than discussing each investigation in detail here, this page focuses on how they guide surgical planning.
For comprehensive information on each investigation, please refer to the dedicated pages below.
The Diagnostic Process
Most patients undergo the following steps:
- Clinical Evaluation – Your doctor will assess your symptoms, examine the knee, and review your medical history.
- Imaging Studies – An X-ray is usually the first investigation, followed by an MRI, which is the most important scan for defining the extent of the tumor and planning surgery. Depending on the suspected diagnosis, CT, PET-CT, or a bone scan may also be required.
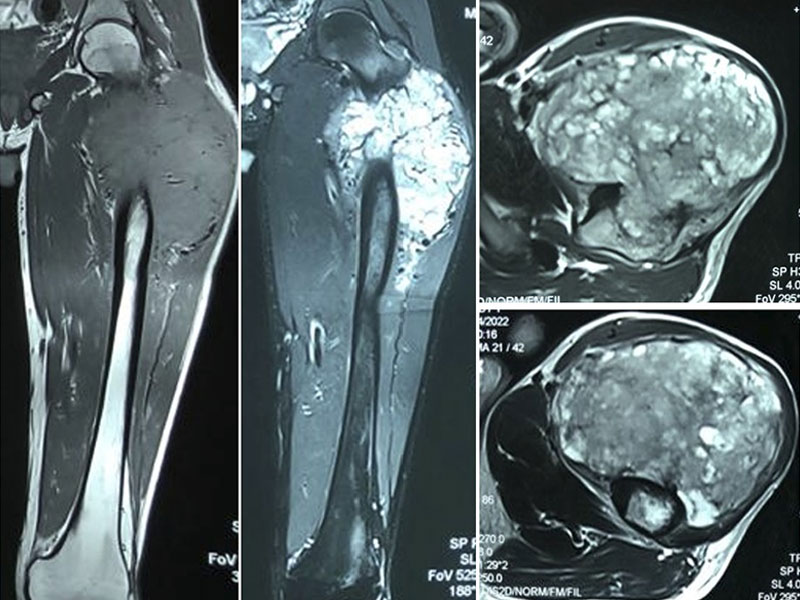
Figure 12. MRI showing the extent of a bone tumor around the hip, helping plan safe tumor removal.
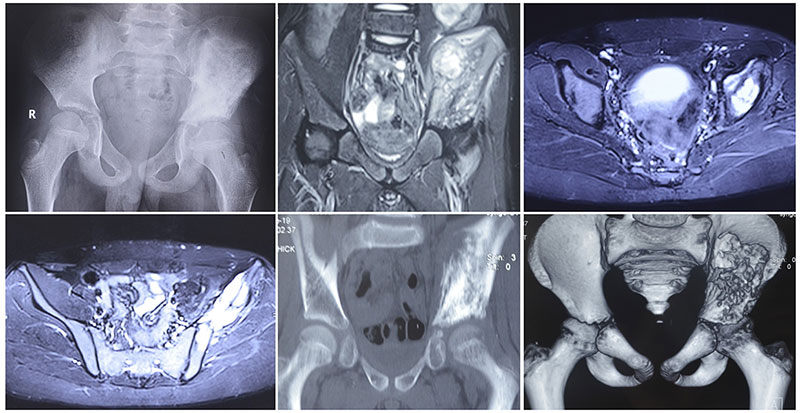
Figure 13. MRI assessment of a pelvic bone tumor, demonstrating its relationship to the hip joint and surrounding structures.
- Biopsy – A small tissue sample is obtained to establish the exact diagnosis. In most cases, a core needle biopsy is sufficient. The biopsy should ideally be planned and performed by the same specialist team that will undertake the definitive surgery.
- Multidisciplinary Team (MDT) Review – Orthopaedic oncologists, radiologists, pathologists, medical oncologists, and other specialists review all findings together to develop an individualized treatment plan.
Treatment Planning: Why Every Patient Is Different
Although two patients may appear to have similar tumors on imaging, their treatment plans may be completely different.
The decision depends on multiple factors, including:
- Tumor diagnosis
- Tumor grade
- Tumor location
- Hip joint involvement
- Bone destruction
- Soft tissue involvement
- Neurovascular involvement
- Patient age and activity level
- Overall health
- Functional expectations
Every patient is discussed in a Multidisciplinary Team (MDT) meeting involving orthopaedic oncologists, radiologists, pathologists, medical oncologists, radiation oncologists, and rehabilitation specialists. Together, they develop an individualized treatment plan that aims to achieve complete tumor removal while preserving the best possible function.
Limb Salvage Surgery for Hip & Pelvic Bone Tumors
For many patients, the greatest fear after being diagnosed with a pelvic bone tumor is, “Will I lose my leg?”
The good news is that advances in imaging, chemotherapy, surgical techniques, and reconstruction now allow limb salvage surgery for many patients with both benign and malignant bone tumors.
Limb salvage surgery is an operation in which the tumor is removed completely while preserving the affected leg. After removing the diseased bone, the surgeon reconstructs the pelvis or hip, when necessary, to restore stability and function.
However, limb salvage is not appropriate for every patient. The primary goal is always complete and safe tumor removal. Preserving the limb should never compromise cancer control.
Doctor Explains
Limb salvage does not mean removing less tumor. It means removing the entire tumor with an adequate margin of healthy tissue while preserving the leg whenever it can be done safely.
Limb Salvage Surgery vs External Hemipelvectomy
Clinical Pearl
The safest cancer operation is always the best operation. Limb preservation is considered only when complete tumor removal can still be achieved.
Reassurance Box
Most patients treated at specialized musculoskeletal oncology centers can now undergo limb salvage surgery. Whether this is possible depends on the location of the tumor and its relationship to critical nerves, blood vessels, and surrounding organs.
What Determines the Type of Pelvic Reconstruction?
Removing the tumor is only one part of surgery. The next challenge is deciding whether reconstruction is needed and, if so, which type will provide the best long-term outcome.
There is no single reconstruction that is ideal for every patient. Instead, surgeons evaluate several important factors before recommending the most appropriate option.
Six Questions Every Surgeon Must Answer
1. Has the Hip Joint Been Involved?
The most important question is whether the tumor has extended into the acetabulum—the socket of the hip joint.
If the hip joint can be preserved, surgery is often less complex and function may be better. If the acetabulum must be removed, reconstruction usually becomes necessary.
2. How Much Bone Needs to Be Removed?
The amount of pelvis removed varies widely.
Some tumors require removal of only a small part of the iliac wing, while others involve the acetabulum, pubis, ischium, or multiple regions of the pelvis.
Greater bone loss generally requires more complex reconstruction.
3. Can Important Muscles Be Preserved?
The hip muscles—particularly the gluteal muscles and hip abductors—play a major role in walking.
Even with an excellent implant, loss of these muscles can reduce hip function.
4. Are the Major Nerves and Blood Vessels Involved?
Tumors that involve the sciatic nerve, femoral nerve, or major pelvic blood vessels may require more extensive surgery.
Preserving these structures whenever it is oncologically safe helps maximize postoperative function.
5. Is There Enough Soft Tissue to Cover the Reconstruction?
Healthy muscles and soft tissues protect implants and promote wound healing.
When large amounts of muscle must be removed with the tumor, surgeons may choose a different reconstruction strategy or perform additional soft tissue reconstruction using muscle flaps.
6. What Are the Patient’s Functional Goals?
Treatment is individualized.
Factors such as:
- Age
- General health
- Activity level
- Occupation
- Expected survival
- Personal goals
all influence reconstruction planning.
For example, the ideal reconstruction for a teenager with osteosarcoma may differ considerably from that for an older adult with metastatic bone disease.
Doctor Insight
The reconstruction is chosen after deciding how the tumor should be removed—not the other way around. Cancer clearance always takes priority over implant selection.
Patient Tip
Ask your surgeon why a particular reconstruction has been recommended for you. Understanding the reasoning behind the decision often makes the treatment plan easier to understand and helps set realistic expectations for recovery.
Does the Hip Joint Need to Be Removed?
One of the most important decisions in pelvic tumor surgery is whether the hip joint can be preserved.
This depends primarily on whether the tumor involves the acetabulum, the cup-shaped socket of the hip joint.
MRI plays a crucial role in answering this question by showing:
- Whether the tumor extends into the acetabulum
- Whether the joint cartilage is involved
- Whether nearby muscles have been affected
- Whether important nerves or blood vessels are close to the tumor
If the acetabulum is free of disease, surgeons may be able to preserve the native hip joint. If it is involved, reconstruction of the hip joint usually becomes necessary after tumor removal.
Importantly, the size of the tumor alone does not determine whether the joint must be removed. A relatively small tumor involving the acetabulum may require joint-sacrificing surgery, while a larger tumor elsewhere in the pelvis may allow the hip joint to be preserved.
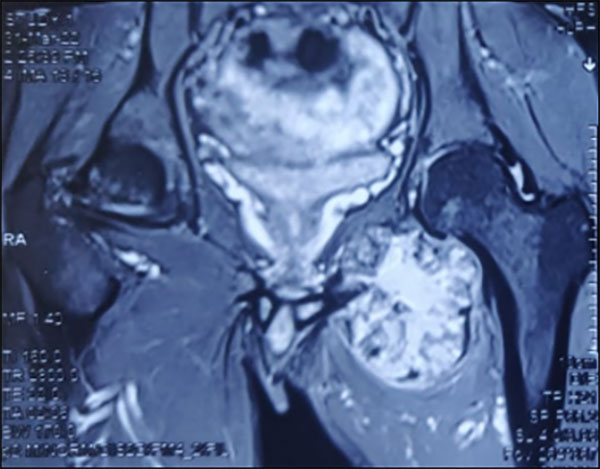
Figure 14. Pelvic bone tumor with the hip joint spared, allowing preservation of the natural hip during tumor surgery.
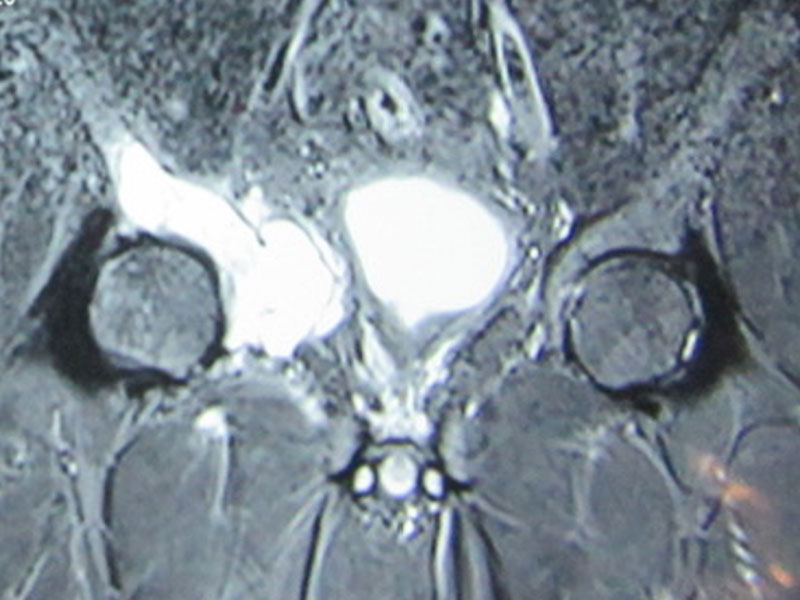
Figure 15. Pelvic bone tumor involving the hip joint, requiring more extensive resection and reconstruction.
Clinical Pearl
Preserving the hip joint depends on where the tumor is located, not simply on how large it is.
Reassurance Box
Even when the hip joint must be removed, modern reconstructive techniques can often restore a stable, functional limb and allow many patients to return to independent mobility.
How Much Bone Needs to Be Removed?
Every bone tumor is removed with a surgical margin—a cuff of normal tissue surrounding the tumor—to reduce the risk of local recurrence.
The amount of bone removed therefore depends on the extent of the tumor, not simply its visible boundaries on imaging.
Pelvic resections vary from removal of a small segment of bone to removal of multiple parts of the pelvic ring. Surgeons carefully plan the operation using MRI and CT scans to remove the tumor completely while preserving as much normal bone as possible.
Rather than using technical classification systems, patients can think of pelvic surgery in four broad categories:
Limited pelvic resection – Small portion of the pelvis removed.
Iliac resection – Removal of part of the upper pelvic wing.
Periacetabular resection – Removal of the hip socket (acetabulum).
Extended pelvic resection – Removal of multiple parts of the pelvis when required.
The extent of resection directly influences whether reconstruction is needed and which reconstructive option is most appropriate.
Types of Pelvic Bone Resection (Patient-Friendly Overview)
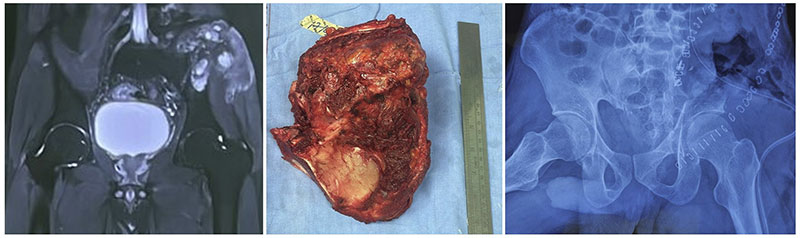
Figure 16. Iliac bone tumor resection, removing the tumor while preserving the hip joint.
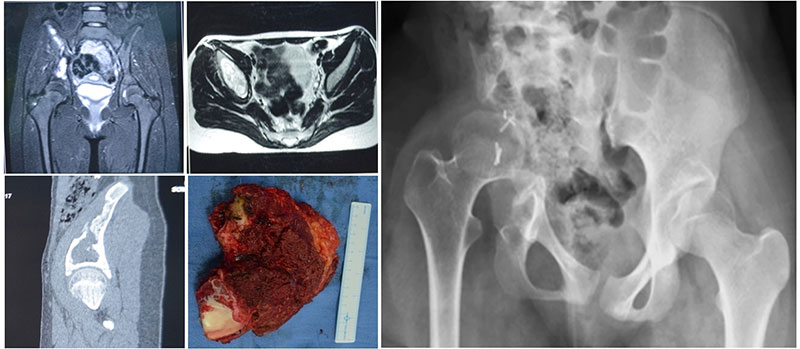
Figure 17. Periacetabular tumor resection with reconstruction of the hip and pelvic region.
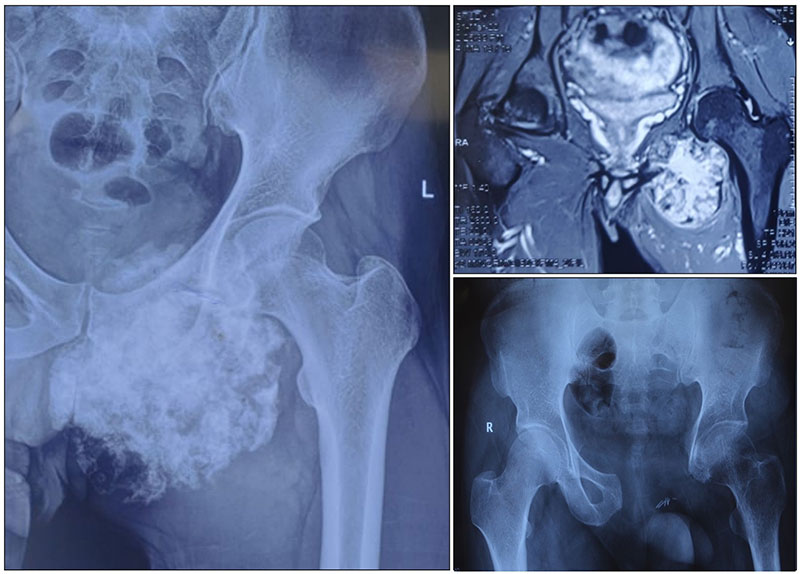
Figure 18. Pelvic tumor resection while preserving the hip joint, an important limb-salvage approach.
Doctor Explains
Patients often ask, “How much bone will you remove?” The answer depends on achieving a safe surgical margin while preserving as much healthy bone and soft tissue as possible.
Proximal Femur Resection and Megaprosthesis Reconstruction
The proximal femur is the upper part of the thigh bone that forms the ball of the hip joint. It includes the femoral head, femoral neck, and the bony prominences where important muscles attach. Tumors arising in this region can weaken the bone, cause severe pain, lead to pathological fractures, or destroy the hip joint, making surgical treatment necessary.
When a malignant bone tumor, aggressive benign tumor, or selected metastatic lesion involves the proximal femur, the affected bone is removed through a procedure known as proximal femur resection. The objective is to remove the entire tumor with an adequate margin of healthy tissue while preserving the surrounding nerves, blood vessels, and muscles whenever possible.
Because removal of the proximal femur also removes part of the hip joint, reconstruction is usually required to restore stability, maintain limb length, and allow the patient to walk again.
Learn more: Limb Salvage Surgery
Tumor Megaprosthesis Reconstruction
The most common method of reconstruction after proximal femur tumor resection is a tumor megaprosthesis.
A tumor megaprosthesis is a specially designed artificial implant that replaces the removed segment of the femur and recreates the hip joint. Unlike a conventional hip replacement, which replaces only the damaged joint surfaces, a tumor megaprosthesis replaces a much larger section of bone that has been removed during cancer surgery.
Modern megaprostheses are modular, allowing the implant to be customized according to the amount of bone removed. The remaining femur is securely fixed to the implant, and the artificial hip joint is reconstructed to restore stability and function.
The goal is not only to remove the tumor safely but also to provide a stable, pain-free limb that enables patients to return to walking and everyday activities as early as possible.
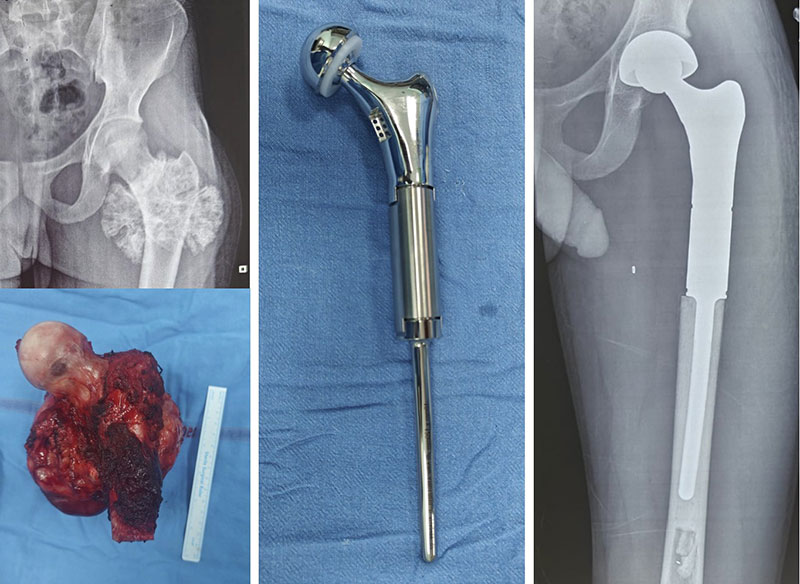
Figure 19. Limb-salvage surgery for a proximal femur bone tumor using a custom endoprosthetic reconstruction
Tumor Megaprosthesis vs. Standard Hip Replacement
Restoring Muscle Function
Successful reconstruction depends on more than replacing the bone. During surgery, every effort is made to preserve or reconstruct the muscles around the hip—particularly the hip abductors, which are essential for balance and walking.
Reattaching these muscles to the prosthesis helps improve hip stability, reduce limping, and enhance long-term function. The amount of muscle that can be preserved depends on the location and extent of the tumor.
Recovery After Proximal Femur Reconstruction
One of the major advantages of a tumor megaprosthesis is that it provides immediate structural stability, allowing rehabilitation to begin soon after surgery. Many patients are able to stand and start walking with the support of a walker or crutches within the first few days, although weight-bearing and activity are progressed according to the surgeon’s recommendations.
Recovery continues over several months as muscles strengthen and balance improves. Most patients regain independent mobility, although some may have a mild limp or require a walking stick for longer distances, particularly if important hip muscles had to be removed.
Clinical Pearl
A tumor megaprosthesis is not the same as a routine hip replacement. It is specifically designed to replace large sections of bone removed during tumor surgery while restoring hip stability and function.
Doctor Explains
The success of a proximal femur reconstruction depends not only on the implant but also on preserving healthy muscles and achieving complete tumor removal. Every reconstruction is tailored to the patient’s anatomy, diagnosis, and functional goals.
Reassurance Box
Advances in limb salvage surgery and modern megaprostheses mean that most patients with proximal femoral bone tumors can avoid amputation. With appropriate rehabilitation, many return to independent walking, work, and an active lifestyle.
Reconstruction After Pelvic Tumor Surgery
After a pelvic bone tumor is removed, the surgeon must decide whether reconstruction is needed to restore stability and function. The goal is not simply to replace missing bone, but to create a stable, pain-free limb that allows the patient to stand, walk, and perform daily activities.
Not every patient requires reconstruction. In some cases, the remaining pelvis is stable enough to function well without an implant. In others—particularly when the hip socket (acetabulum) is removed—reconstruction is essential. The best option is the one that provides safe tumor removal, durable function, and the lowest risk of complications, rather than the most complex implant.
Doctor Insight
Reconstruction is planned only after achieving complete tumor removal. Cancer clearance always takes priority over implant selection.
When Is Reconstruction Required?
The need for reconstruction depends on several factors, including:
- Which part of the pelvis has been removed
- Whether the hip joint is involved
- Stability of the remaining pelvis
- Quality of the surrounding muscles and soft tissues
- Patient’s age, activity level, and overall health
In general, reconstruction becomes more important when surgery affects the hip joint or significantly alters weight-bearing through the pelvis.
When Reconstruction May Not Be Necessary
Reconstruction is not always required. Tumors confined to the iliac wing, or selected lesions involving the pubis or ischium, can often be treated without reconstruction if the remaining pelvis remains stable.
Avoiding unnecessary implants may shorten surgery, reduce blood loss, lower the risk of infection, and eliminate implant-related complications while still providing excellent functional outcomes.
Clinical Pearl
Sometimes, not reconstructing the pelvis is the best reconstruction, provided stability and function can be safely preserved.
Endoprosthetic Reconstruction (Pelvic Megaprosthesis)
When the tumor involves the acetabulum (hip socket), reconstruction of the hip joint is usually necessary. A pelvic megaprosthesis is a modular metallic implant designed to replace the removed bone and recreate the hip joint.
Its main advantages include immediate stability, restoration of limb length, earlier rehabilitation, and reliable pain relief. However, like all major joint reconstructions, it carries risks such as infection, hip dislocation, implant loosening, and mechanical wear over time.
Custom-Made and 3D-Printed Pelvic Implants
For complex pelvic defects, surgeons may recommend patient-specific implants created using CT and MRI scans. These customized implants are designed to match the patient’s anatomy and may provide a better fit in selected cases. Modern 3D-printed titanium implants also encourage bone to grow into the implant, improving long-term fixation.
They are particularly useful for complex resections, revision surgery, and selected younger patients, but they are not necessary for every pelvic tumor.
Doctor Explains
A custom implant is chosen only when standard reconstruction cannot adequately restore the patient’s anatomy.
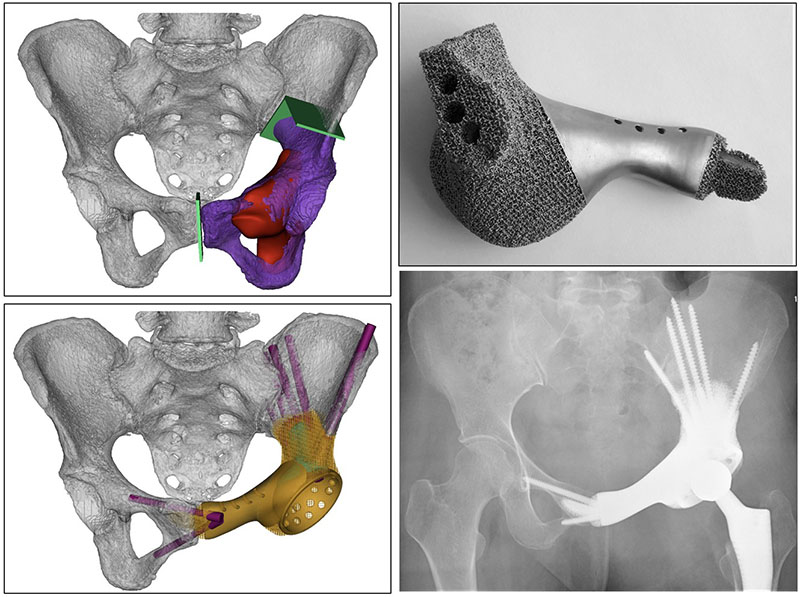
Figure 20. Patient-specific 3D-printed pelvic implant designed for reconstruction after pelvic bone tumor removal.
Biological Reconstruction
Instead of using metal implants, surgeons may reconstruct the pelvis using living or donated bone. Options include allografts, autografts, and vascularized fibular grafts.
Although biological reconstruction has the advantage of long-term bone incorporation, healing is slower and complications such as non-union or fracture may occur. For this reason, these techniques are reserved for carefully selected patients.
Learn more: Biological Reconstruction After Bone Tumor Surgery
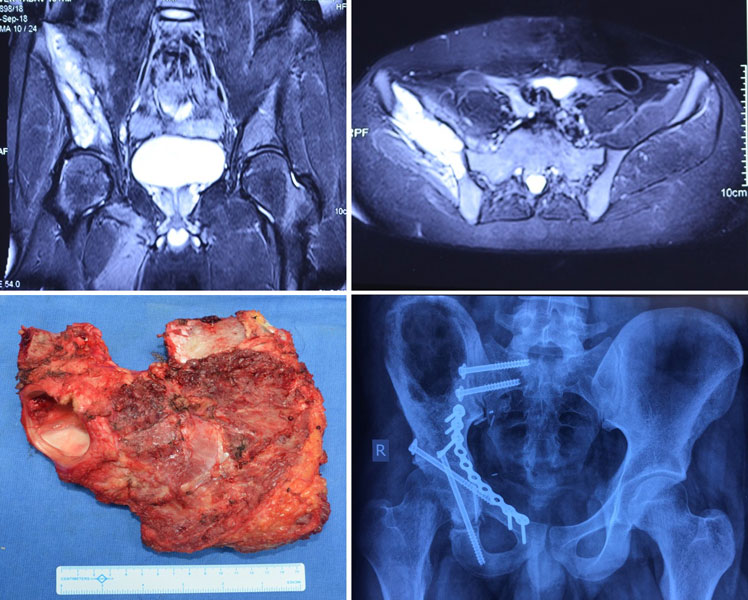
Figure 21. Extracorporeally irradiated autograft reconstruction following pelvic bone tumor resection, preserving the patient’s own bone.
Hip Transposition
Hip transposition is a specialized biological technique used after removal of the acetabulum. Rather than inserting an artificial hip socket, the patient’s own femur is repositioned to create a new functional articulation.
This approach avoids large implants and may reduce some long-term mechanical complications, although hip movement is generally more limited than with prosthetic reconstruction.
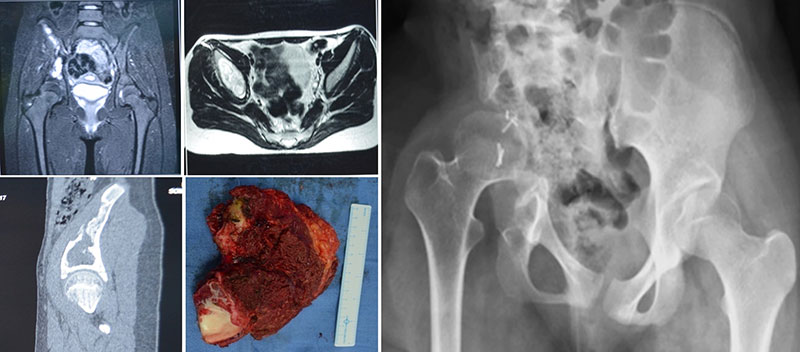
Figure 22. Hip transposition after pelvic tumor resection, a limb-salvage reconstruction that preserves the lower limb while removing the diseased pelvic bone.
Clinical Pearl
The best reconstruction is the one that matches the patient’s anatomy, remaining soft tissues, and functional needs—not necessarily the most complex implant.
Expected Function After Reconstruction
Recovery depends on more than the implant itself. Functional outcomes are influenced by the amount of bone removed, preservation of important muscles and nerves, soft tissue coverage, rehabilitation, and patient motivation.
While every reconstruction has its limitations, the goal is to provide a stable, pain-free limb that allows the greatest possible independence and quality of life.
Comparison of Reconstruction Options
Patient Tip
Ask your surgeon why a particular reconstruction has been recommended for you and what level of function you can realistically expect. Understanding the goals and limitations of your reconstruction helps set realistic expectations and prepares you for rehabilitation.
Recovery, Rehabilitation and Long-Term Follow-up
Recovery after hip and pelvic bone tumor surgery is a gradual process that extends beyond the operation itself. While surgery removes the tumor and reconstructs the bone when needed, rehabilitation is essential for restoring mobility, strength, and independence.
Recovery varies depending on the type of tumor, the extent of surgery, the reconstruction performed, and the patient’s overall health. Every patient follows a different timeline, so progress should be measured against your own recovery goals rather than someone else’s.
Immediately After Surgery
The first few days focus on pain control, wound care, prevention of blood clots, breathing exercises, and early mobilization. A multidisciplinary team of surgeons, physiotherapists, nurses, and pain specialists works together to ensure a safe recovery.
Depending on the procedure, sitting out of bed and assisted walking may begin within the first few days.
Walking Again
The timing of walking depends on the type of surgery and reconstruction. Some patients begin walking with a walker or crutches within days, while others require a longer period of protected weight-bearing.
Doctor Explains
Recovery is guided by healing, not by a fixed timeline. Walking is introduced gradually to protect the reconstruction and surrounding soft tissues.
Physiotherapy
Physiotherapy starts soon after surgery and continues for several months. It focuses on improving hip movement, muscle strength, balance, walking pattern, and endurance, helping patients return safely to daily activities.
Returning to Daily Life
Many patients regain independence and return to work, driving, household activities, and light exercise. High-impact activities such as running and contact sports may not be recommended after major reconstruction. Your surgeon will advise you on suitable activities based on your operation.
Recovery Timeline After Hip & Pelvic Bone Tumor Surgery
*Recovery varies between patients and procedures.
Clinical Pearl
Functional recovery often continues for 12–18 months after major pelvic reconstruction.
Patient Tip
Consistently following your rehabilitation program is one of the most important factors influencing long-term recovery.
Reassurance
Although recovery can be demanding, many patients return to independent walking, work, and an active lifestyle with appropriate rehabilitation.
Long-Term Follow-up
Regular follow-up is essential after treatment to monitor recovery, detect recurrence early, and assess the condition of biological reconstructions or implants.
Follow-up may include clinical examination, X-rays, MRI, CT scans (for selected malignant tumors), and other investigations based on your diagnosis. The frequency of visits depends on the type of tumor and treatment received, with closer surveillance usually required during the first few years after surgery.
Did You Know?
Follow-up appointments are important not only for detecting tumor recurrence but also for monitoring implant function, bone healing, and helping you safely return to normal activities.
Frequently Asked Questions (FAQs)
1. What are the symptoms of a hip or pelvic bone tumor?
Common symptoms include persistent hip or groin pain, pain at night, swelling, limping, reduced hip movement, and, in some cases, a pathological fracture. These symptoms can resemble arthritis or sports injuries, making specialist evaluation important if they persist.
2. Are all hip and pelvic bone tumors cancerous?
No. Many tumors affecting the hip and pelvis are benign (non-cancerous). However, some benign tumors can still weaken the bone or behave aggressively and may require surgery. Imaging and a biopsy are often needed to determine the exact diagnosis.
3. How are hip and pelvic bone tumors diagnosed?
Diagnosis usually involves a combination of clinical examination, X-rays, MRI, CT scans, and a biopsy. The biopsy confirms the exact type of tumor and helps guide the most appropriate treatment plan.
4. Can a hip or pelvic bone tumor be treated without surgery?
Yes. Some benign tumors only require observation or regular imaging. However, surgery is often recommended for aggressive benign tumors, malignant bone tumors, tumors causing severe pain, or those at risk of causing a pathological fracture.
5. Is limb salvage surgery possible for most patients?
Yes. Advances in imaging, chemotherapy, surgical techniques, and reconstruction allow limb salvage surgery for many patients with hip and pelvic bone tumors. Amputation is reserved for selected cases where safe tumor removal cannot be achieved while preserving the limb.
6. Will I need chemotherapy or radiotherapy?
It depends on the type of tumor. Osteosarcoma and Ewing sarcoma usually require chemotherapy, while chondrosarcoma is primarily treated with surgery. Some metastatic bone tumors may also benefit from radiotherapy or systemic therapy.
7. What is a tumor megaprosthesis?
A tumor megaprosthesis is a specialized implant designed to replace large sections of bone removed during tumor surgery. Unlike a standard hip replacement, it restores both the bone and the hip joint after extensive tumor resection.
8. Is reconstruction always required after pelvic tumor surgery?
No. Some pelvic tumors can be removed without reconstruction if the remaining pelvis remains stable. Reconstruction is usually necessary when the hip socket (acetabulum) or major weight-bearing structures have been removed.
9. How long does recovery take after hip or pelvic tumor surgery?
Recovery varies depending on the type of surgery and reconstruction performed. Many patients begin rehabilitation within a few days, but improvements in walking, strength, and function may continue for 12–18 months after major reconstruction.
10. Will I be able to walk normally after surgery?
Many patients regain independent walking after rehabilitation. However, the final outcome depends on the amount of bone removed, muscle preservation, the type of reconstruction, and commitment to physiotherapy.
11. What are the risks of hip and pelvic bone tumor surgery?
As with any major surgery, risks include infection, bleeding, blood clots, wound healing problems, nerve injury, implant-related complications, hip dislocation (after some reconstructions), and tumor recurrence. Your surgeon will discuss the risks specific to your condition.
12. Can a bone tumor come back after surgery?
Some bone tumors have a risk of local recurrence, even after complete removal. Regular follow-up with clinical examinations and imaging helps detect recurrence early and allows prompt treatment if needed.
13. How often will I need follow-up after surgery?
Follow-up schedules vary depending on the type of tumor and treatment received. Patients with malignant bone tumors usually require more frequent visits during the first few years, including imaging to monitor for recurrence and assess implant function.
14. Should I get a second opinion before surgery?
Yes. Hip and pelvic bone tumor surgery is highly specialized, and obtaining a second opinion from an orthopaedic oncologist or sarcoma center is often recommended, especially before undergoing major surgery or reconstruction.
15. Why should hip and pelvic bone tumors be treated at a specialized sarcoma center?
These tumors often require advanced imaging, expert pathology, multidisciplinary treatment planning, complex limb salvage surgery, and specialized reconstruction techniques. Treatment at a dedicated musculoskeletal oncology center improves the likelihood of accurate diagnosis, optimal treatment, and the best possible functional outcome.
Medical Disclaimer
The information provided on this page is intended for patient education only and should not be considered a substitute for professional medical advice, diagnosis, or treatment. Every hip and pelvic bone tumor is unique, and treatment decisions depend on the type of tumor, its location, imaging findings, biopsy results, overall health, and individual patient goals. Always consult a qualified orthopaedic oncologist or multidisciplinary sarcoma team for personalized evaluation and treatment recommendations. If you have persistent hip pain, a suspected bone tumor, or have been advised to undergo surgery, seek prompt specialist assessment rather than relying solely on online information.
References
- Hugate R Jr, Sim FH. Pelvic reconstruction techniques. Orthop Clin North Am. 2006;37(1):85-97
- Wilson RJ, Freeman TH Jr, Halpern JL, Schwartz HS, Holt GE. Surgical Outcomes After Limb-Sparing Resection and Reconstruction for Pelvic Sarcoma: A Systematic Review. JBJS Rev. 2018;6(4):e10.
- Hoffmann C, Gosheger G, Gebert C, Jürgens H, Winkelmann W. Functional results and quality of life after treatment of pelvic sarcomas involving the acetabulum. J Bone Joint Surg Am. 2006;88(3):575-582.
- Li B, Yu Y, Bao Y, Song J. Proximal femoral tumor resection followed by joint prosthesis replacement: a systematic review and meta-analysis. BMC Musculoskelet Disord. 2023;24(1):779. Published 2023 Oct 2.
- Janssen SJ, Langerhuizen DWG, Schwab JH, Bramer JAM. Outcome after reconstruction of proximal femoral tumors: A systematic review. J Surg Oncol. 2019;119(1):120-129.
 +91 93558 33005

