Quick Answer
Pediatric bone tumor treatment refers to the medical and surgical care used to treat bone tumors in children and adolescents. Treatment depends on whether the tumor is benign (non-cancerous) or malignant (cancerous), its location, size, and whether it has spread to other parts of the body.
A child’s treatment plan may include one or more of the following:
- Care by a multidisciplinary team (a group of specialists who work together)
- Surgery to remove the tumor
- Chemotherapy (medicines that destroy cancer cells)
- Radiotherapy (high-energy radiation used to kill cancer cells, when appropriate)
- Limb salvage surgery (removing the tumor while preserving the arm or leg)
- Bone reconstruction using biological tissue or a prosthesis (an artificial replacement)
- Physiotherapy and rehabilitation
- Long-term follow-up to monitor recovery, growth, and recurrence
For many children, modern treatment makes it possible to cure the disease while preserving excellent function and quality of life.
Quick Summary
Pediatric bone tumor treatment is highly individualized. There is no single treatment that is suitable for every child. Decisions are based on the type of tumor, its location, the child’s age, stage of skeletal growth, and overall health. Treatment is carefully planned by a team of specialists with the goals of curing the disease, preserving limb function whenever possible, minimizing treatment-related complications, and helping the child return to a healthy and active life.
Hero Image: A child walking confidently with family after successful limb salvage surgery, symbolizing recovery and hope.
Understanding Pediatric Bone Tumors
Hearing that your child may have a bone tumor can be frightening. Many parents immediately think of cancer, amputation, or lifelong disability. These fears are understandable—but they are not always accurate.
The good news is that not every bone tumor in a child is cancer, and even when a tumor is malignant, treatment has advanced tremendously over the past few decades. Today, many children can be treated successfully while preserving the affected limb and returning to school, sports, and everyday activities.
Understanding the basics of bone tumors and how they are treated can help you make informed decisions and reduce anxiety during what is often an overwhelming time.
Common Bone Tumors in Children
Several different bone tumors can occur during childhood and adolescence. Each behaves differently and requires a different treatment approach.
Common Pediatric Bone Tumors
Rather than treating all bone tumors the same way, doctors tailor treatment according to the specific diagnosis. This is why obtaining an accurate diagnosis before surgery is so important.
Did You Know?
Many children first notice pain after a sports injury or minor fall. In most cases, the injury does not cause the tumor—it simply draws attention to a problem that was already present.
Why Early Diagnosis Matters
Early diagnosis means recognizing persistent or unusual symptoms before the disease progresses, not necessarily diagnosing the tumor within days. Although most bone pain and swelling in children are caused by non-cancerous conditions, certain symptoms should never be ignored, including:
- Persistent bone pain lasting several weeks
- Pain that is worse at night
- Swelling or an enlarging lump over a bone
- Limping without an obvious injury
- A fracture after minimal trauma (pathological fracture)
Early evaluation allows timely imaging, accurate diagnosis, and appropriate treatment, improving the chances of successful outcomes.
Clinical Pearl
Persistent, localized bone pain in a growing child should never be dismissed as “growing pains” without proper clinical evaluation, particularly if associated with swelling or worsening symptoms.
Goals of Pediatric Bone Tumor Treatment
Treatment is not simply about removing a tumor—it aims to cure the disease while preserving the child’s growth, function, and quality of life.
The main goals are to:
- Completely remove or control the tumor.
- Maximize the chance of cure.
- Preserve the limb whenever safely possible.
- Maintain movement and function.
- Protect growth plates whenever feasible.
- Minimize treatment-related complications.
- Support emotional well-being.
- Help children return to school, sports, and daily activities.
For benign tumors, treatment focuses on relieving symptoms, preventing fractures or deformity, and preserving normal bone growth while avoiding unnecessary surgery.
Doctor Insight
Success is measured not only by survival but also by how well a child functions years later. The best treatment allows children to remain active, independent, and fully engaged in everyday life.
The Multidisciplinary Treatment Team
Pediatric bone tumors are best managed by a multidisciplinary team (MDT), where specialists work together to create an individualized treatment plan.
The team may include:
- Orthopaedic oncologist
- Pediatric medical oncologist
- Radiologist
- Pathologist
- Radiation oncologist
- Physiotherapist
- Pediatric oncology nurse
- Psychologist or child life specialist
- Nutritionist
Doctor Explains
Before treatment begins, the MDT reviews the child’s imaging, biopsy, overall health, and treatment goals together. This collaborative approach ensures every decision is based on combined expertise rather than a single opinion.
Patient Tip
Ask who is involved in your child’s care and what each specialist does. Understanding the team’s roles can make the treatment journey feel more organized and reassuring.
How Is Treatment Planned?
Every child is different, so treatment is carefully tailored to the tumor type, location, size, stage, growth potential, and overall health.
Planning usually includes:
Medical History and Physical Examination
Doctors assess symptoms, duration of pain, swelling, walking difficulties, previous injuries, general health, family history, and examine the affected limb, joints, muscles, and nerves.
Imaging Tests
Imaging defines the tumor and guides treatment.
Common investigations include:
- X-ray – First-line investigation.
- MRI – Evaluates the tumor, muscles, nerves, and blood vessels; essential for surgical planning.
- CT scan – Commonly used to assess the lungs for metastases.
- PET-CT or Bone Scan – Used selectively to detect disease elsewhere.
Biopsy
A biopsy confirms the diagnosis by examining tumor tissue under the microscope. It should be carefully planned by, or in consultation with, the team performing the definitive surgery, as an improperly placed biopsy can compromise limb salvage.
Biopsy in Bone & Soft Tissue Tumors
Clinical Pearl
For suspected malignant bone tumors, MRI should be performed before biopsy whenever possible. Proper biopsy planning is critical for successful limb salvage surgery.
Tumor Board Discussion
Once investigations are complete, the MDT reviews all findings and develops an individualized treatment plan.
How Are Pediatric Bone Tumors Treated?
Treatment depends on:
- Whether the tumor is benign or malignant.
- The exact diagnosis.
- Tumor size and location.
- Whether it has spread.
- The child’s age and stage of skeletal growth.
- Overall health.
Benign tumors may require observation or surgery, whereas malignant tumors are commonly treated with a combination of chemotherapy, surgery, and occasionally radiotherapy. The goal is always to achieve the highest chance of cure while preserving function and quality of life.
Doctor Explains
Treatment is individualized. Even children with the same diagnosis may receive different treatments depending on their age, tumor location, growth potential, and response to therapy.
Chemotherapy
Chemotherapy uses medicines to destroy cancer cells and is an essential part of treatment for many malignant bone tumors, particularly osteosarcoma and Ewing sarcoma. It is usually given intravenously in repeated treatment cycles.
Why Is Chemotherapy Given Before Surgery?
Neoadjuvant chemotherapy is administered before surgery to:
- Shrink the tumor.
- Destroy microscopic cancer cells.
- Assess the tumor’s response to treatment.
- Improve the chances of successful limb salvage.
Why Is Chemotherapy Given After Surgery?
Adjuvant chemotherapy is given after surgery to eliminate any remaining microscopic cancer cells and reduce the risk of recurrence.
What Happens During Chemotherapy?
Treatment is delivered in specialized pediatric oncology units and may involve:
- Intravenous chemotherapy via a vein or implanted port.
- Blood tests before each cycle.
- Medicines to control nausea and prevent infection.
- Regular monitoring of heart, kidney, and liver function.
Common Side Effects
Common side effects include:
- Hair loss
- Fatigue
- Nausea and vomiting
- Mouth ulcers
- Loss of appetite
- Low blood counts with increased infection risk
Most side effects are temporary and improve after treatment.
Reassurance Box
Supportive care has advanced significantly. Modern medications effectively control many side effects, allowing most children to remain active between chemotherapy cycles.
Did You Know?
Hair loss from chemotherapy is almost always temporary. Hair usually begins to regrow within a few months after treatment, although its texture or color may initially be different.
How Is Pediatric Bone Tumor Surgery Different from Adult Bone Tumor Surgery?
Pediatric bone tumor surgery is not simply a smaller version of adult surgery. In addition to removing the tumor, surgeons must preserve future growth, joint development, and long-term function. Whenever possible, the growth plate (physis) is protected to minimize limb-length differences and deformity. Children may benefit from specialized reconstructions such as expandable prostheses or biological reconstruction, which accommodate continued growth. Rehabilitation and follow-up are also more extensive, monitoring growth, limb function, and reconstruction until skeletal maturity. The ultimate goal is to help children return to an active, independent life with the best possible quality of life.
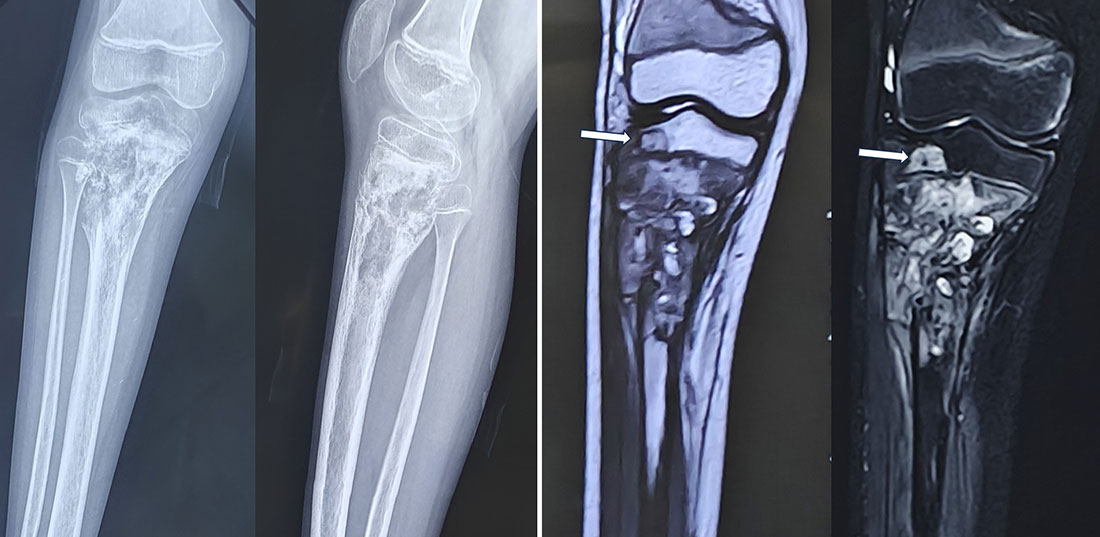
Figure 1. Importance of the growth plate in pediatric bone tumor surgery
Imaging showing a bone tumor near the growth plate in a child, highlighting the importance of preserving growth potential during pediatric bone tumor surgery.
Doctor Insight
In adults, surgeons usually ask, “How can we restore function?” In children, they ask an additional question: “How will this limb function and grow over the next 10 to 20 years?” Every treatment decision is made with the child’s future development in mind.
Pediatric vs Adult Bone Tumor Surgery
Clinical Pearl
Children are not simply “small adults.” Successful pediatric bone tumor surgery requires balancing complete tumor removal with preservation of growth, function, and lifelong mobility. The best surgical plan is one that provides excellent cancer control while allowing the child to develop into an active, independent adult.
Reassurance Box
Parents often worry that their child’s young age makes surgery more difficult. While pediatric bone tumor surgery is indeed more complex, advances in imaging, limb salvage techniques, biological reconstruction, expandable prostheses, and pediatric rehabilitation have dramatically improved outcomes. Today, many children go on to lead active, fulfilling lives after treatment.
Limb Salvage Surgery
Limb salvage surgery means removing the tumor completely while preserving the affected arm or leg.
Instead of removing the entire limb, surgeons remove the portion of bone containing the tumor along with a margin of healthy tissue to reduce the risk of recurrence.
The removed bone is then reconstructed so that the limb can continue to function.
For many children, limb salvage provides an excellent balance between cancer control and preservation of mobility.
Limb Salvage Surgery
Doctor Insight
The success of limb salvage surgery is measured not simply by saving the limb, but by preserving a limb that is comfortable, stable, functional, and free of disease.
Biological Reconstruction
After removing the tumor, surgeons often need to rebuild the missing segment of bone.
Biological reconstruction means rebuilding the bone using living bone tissue that has the potential to heal, unite with the patient’s own bone, and remodel over time.
Depending on the child’s age and the type of surgery, biological reconstruction may involve:
- Bone grafts taken from the patient’s own body (autografts)
- Donor bone from a bone bank (allografts)
- Vascularized fibular grafts (bone transferred with its own blood supply)
- Recycled tumor bone treated with specialized techniques before reimplantation
Each method has its own advantages and limitations, and the most appropriate option depends on the child’s individual situation.
Biological Reconstruction After Bone Tumor Surgery
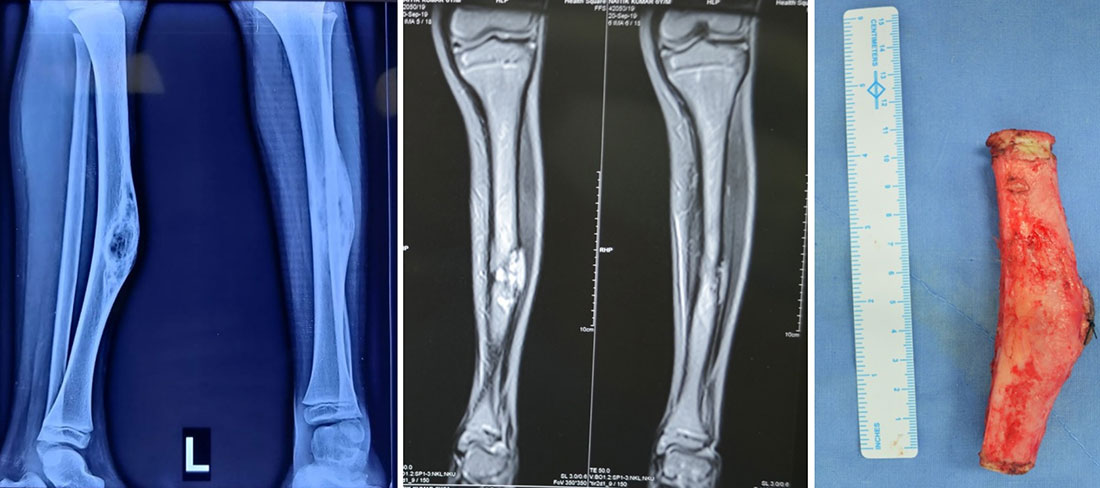
Figure 2A. Tumor resection with vascularized fibula reconstruction
Removal of a bone tumor in a child followed by reconstruction using a vascularized fibular graft to restore bone continuity and support limb function.
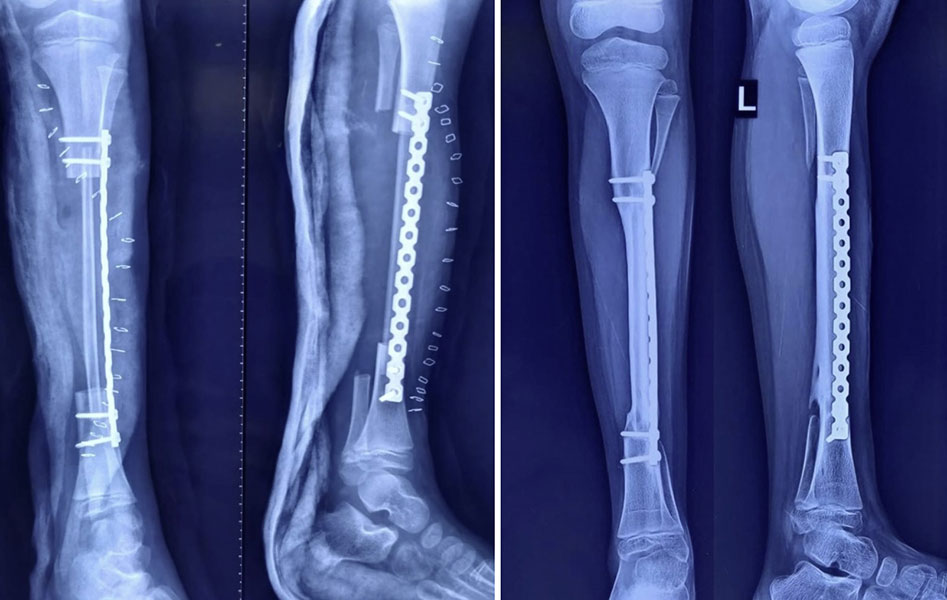
Figure 2B. Healing after vascularized fibula reconstruction
X-rays immediately after surgery and at 2-year follow-up showing incorporation and enlargement (hypertrophy) of the vascularized fibular graft.
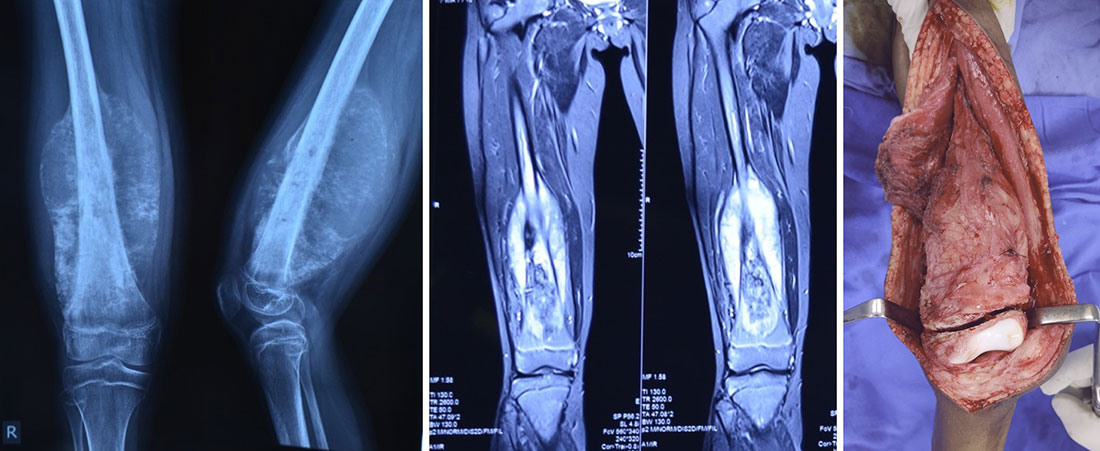
Figure 3A. Growth plate-sparing surgery for osteosarcoma
Imaging of pediatric osteosarcoma showing a tumor that can be removed while preserving the nearby growth plate.
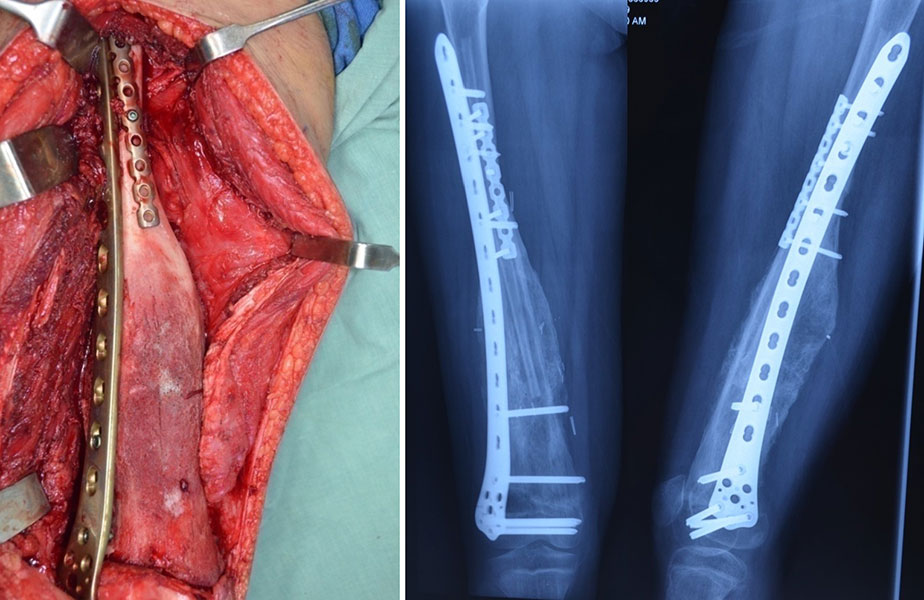
Figure 3B. Wide resection and biological reconstruction for osteosarcoma
After wide tumor removal, the affected bone segment was sterilized with radiation and re-implanted to achieve biological limb reconstruction.
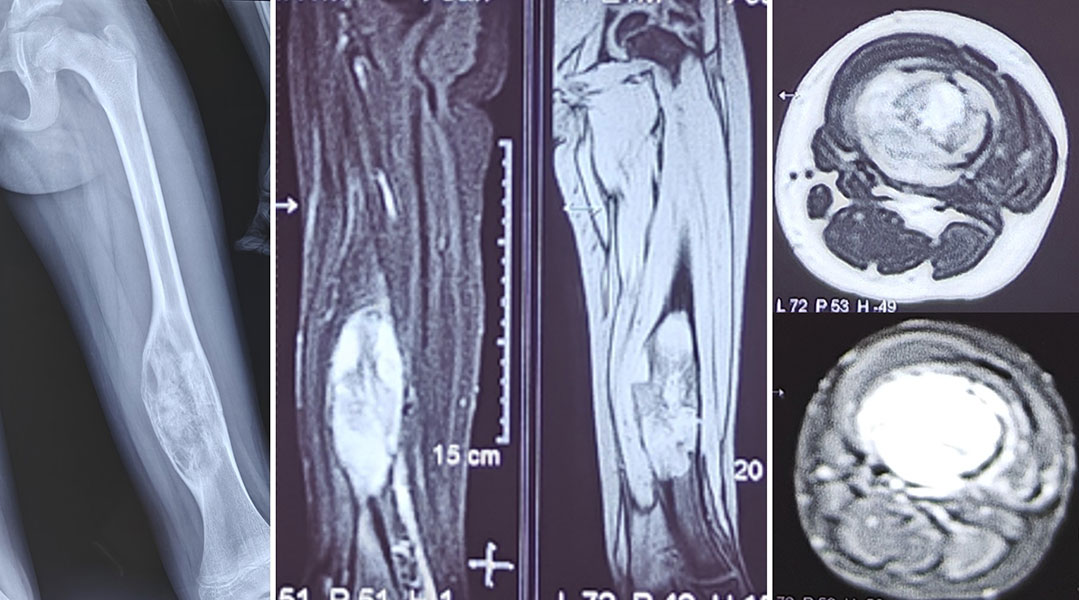
Figure 4A. Osteosarcoma with preservation of the growth plates
Imaging of osteosarcoma in a child planned for limb-sparing surgery while preserving the growth plates.
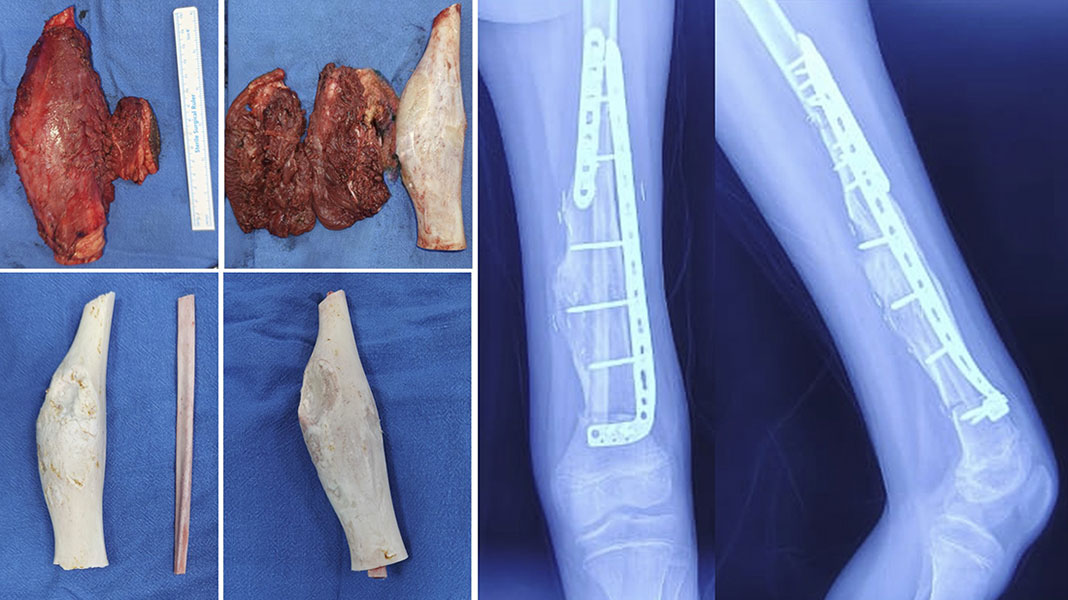
Figure 4B. Intercalary resection and biological reconstruction
Wide removal of the tumor with preservation of the joint and growth plates, followed by soft-tissue clearance, radiation sterilization, and re-implantation of the bone.
Expandable Prosthesis
One of the greatest challenges in treating pediatric bone tumors is that children are still growing. When a tumor involves the end of a long bone, surgeons often need to remove the growth plate (physis) along with the tumor. This can result in a limb-length discrepancy, where one limb becomes shorter than the other over time.
An expandable prosthesis (growing prosthesis) is a specialized artificial implant that replaces the removed bone while allowing gradual lengthening as the child grows. Unlike standard adult prostheses, it is specifically designed for children with significant growth remaining.
Why Is an Expandable Prosthesis Needed?
Most bone growth occurs at the growth plates near the ends of long bones such as the femur, tibia, and humerus. If a growth plate must be removed to achieve complete tumor removal, the affected limb will no longer grow normally.
An expandable prosthesis helps compensate for this lost growth by allowing the implant to be lengthened periodically, reducing future limb-length differences.
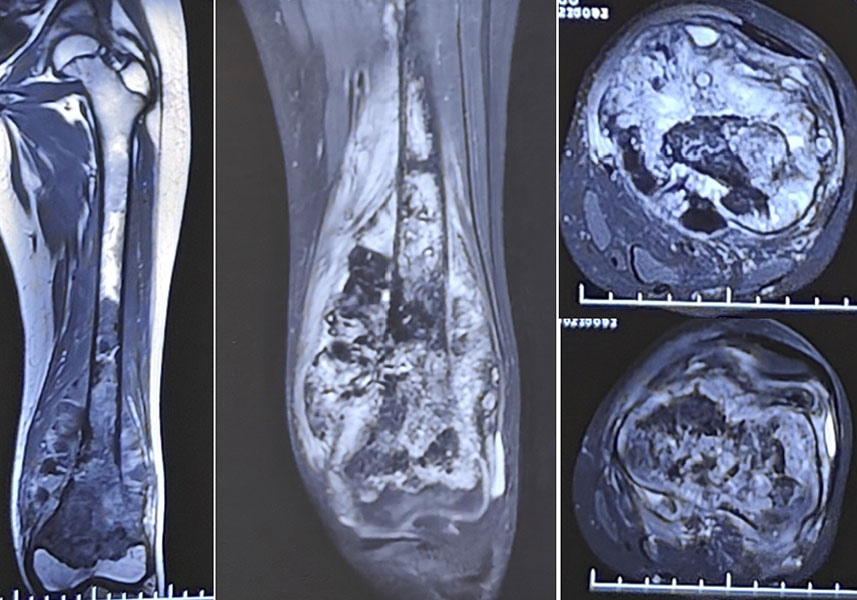
Figure 5A. Bone tumor involving the growth plate
Imaging showing a pediatric bone tumor extending into the growth plate, requiring careful surgical planning to achieve tumor removal while considering future growth.
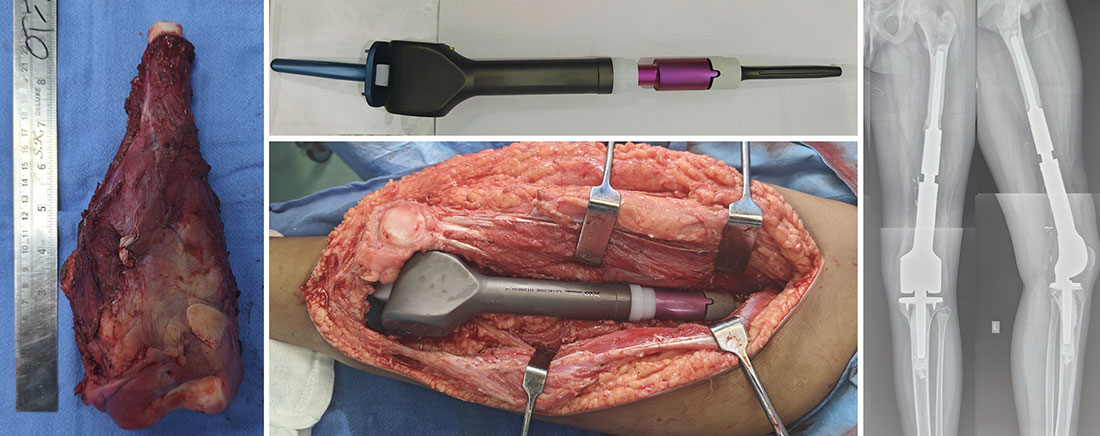
Figure 5B. Wide resection and expandable prosthetic reconstruction
Wide removal of osteosarcoma involving the growth plate followed by reconstruction with an expandable prosthesis designed to accommodate the child’s remaining growth.
How Does an Expandable Prosthesis Work?
Expandable prostheses contain a mechanism that allows controlled lengthening as the child grows. Older designs required surgery for each lengthening, but many modern implants use magnetic or other non-invasive technology, enabling outpatient lengthening without major surgery.
Lengthening is performed gradually based on the child’s age, expected growth, and regular clinical and X-ray assessments.
Doctor Explains
Think of an expandable prosthesis like an adjustable bicycle that grows with a child. Instead of replacing the bicycle every year, it is gradually adjusted to match the child’s growth.
Who Is a Candidate?
Expandable prostheses are most suitable for children who:
- Have a malignant bone tumor requiring removal of a growth plate.
- Have significant growth remaining.
- Have tumors around the knee, particularly the distal femur or proximal tibia.
- Have adequate muscles and soft tissues to support the implant.
- Can participate in long-term rehabilitation and follow-up.
For some children, biological reconstruction, rotationplasty, or a standard tumor prosthesis may be more appropriate.
Table: Advantages and Limitations of Expandable Prostheses
Life After an Expandable Prosthesis
Recovery includes physiotherapy, gradual return to walking, and regular follow-up. Most children can return to school, walk independently, participate in everyday activities, and enjoy a good quality of life. High-impact sports may be restricted to protect the implant.
Patient Tip
The long-term success of an expandable prosthesis depends not only on surgery but also on regular follow-up, physiotherapy, and maintaining an active lifestyle within your healthcare team’s recommendations.
Doctor Insight
An expandable prosthesis is designed to provide the best balance between cancer control, continued growth, mobility, and independence, rather than creating a perfectly normal limb.
Reassurance Box
Many parents worry that an expandable prosthesis will require repeated major operations. Fortunately, many modern implants can now be lengthened using minimally invasive or non-invasive techniques, reducing the need for additional surgery. Your surgical team will recommend the reconstruction that best suits your child’s age, growth potential, tumor location, and long-term needs.
Rotationplasty
Rotationplasty is a specialized limb salvage procedure used in carefully selected children with bone tumors, most commonly osteosarcoma or Ewing sarcoma involving the region around the knee. Although its appearance is unusual, rotationplasty can provide excellent long-term function, allowing many children to walk, run, participate in sports, and lead active, independent lives.
The operation was first described by the German surgeon Salzer and later popularized by Van Nes, and has become an established reconstructive option in pediatric musculoskeletal oncology.
Unlike a conventional amputation, rotationplasty preserves the child’s own lower leg, muscles, nerves, and blood vessels, enabling the ankle to function as a new knee joint after reconstruction.
Why Is Rotationplasty Performed?
Rotationplasty is a specialized limb salvage procedure used for selected children with bone tumors around the knee, particularly when preserving the knee joint would not provide a durable or functional reconstruction. It offers excellent cancer control while preserving long-term mobility.
It is most suitable for:
- Young children with significant growth remaining.
- Tumors of the distal femur or proximal tibia.
- Children who are not ideal candidates for an expandable prosthesis.
- Cases requiring removal of a large segment of bone around the knee.
By preserving the child’s muscles, nerves, and ankle joint, the ankle can function as a new knee after reconstruction.
How Is Rotationplasty Performed?
The tumor-bearing bone is removed with an adequate margin of healthy tissue. The remaining lower leg is then rotated 180° and reattached to the thigh.
Following surgery:
- The ankle functions as a new knee joint.
- The rotated foot fits inside a specially designed prosthesis.
- Preserved muscles and nerves allow excellent control and efficient walking.
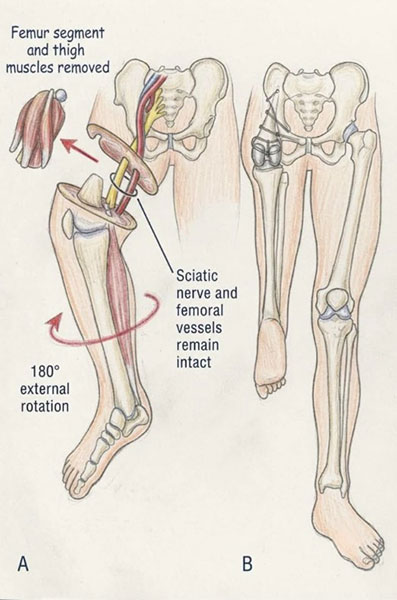
Figure 6. Rotationplasty after wide resection of a femoral bone tumour, with preservation of the sciatic nerve and femoral vessels.
Doctor Explains
Although the foot appears to face backwards, this allows the ankle to bend in the same direction as a normal knee, creating a stable and energy-efficient gait with a prosthesis.
Who Is a Candidate?
Rotationplasty may be recommended for children who:
- Have a malignant bone tumor around the knee.
- Have substantial growth remaining.
- Have intact major nerves and blood vessels.
- Require removal of a large bone segment.
- Are willing to participate in rehabilitation.
The decision is individualized after discussion by a multidisciplinary team.
Advantages of Rotationplasty
Rotationplasty provides excellent long-term function, particularly in active children.
Benefits include:
- Excellent mobility and durability.
- Preserves the child’s own muscles and nerves.
- Better energy efficiency than above-knee amputation.
- Allows participation in many sports and recreational activities.
- Accommodates future growth better than many prosthetic reconstructions.
- Lower risk of repeated revision surgery in selected patients.
Many patients treated in childhood remain highly active throughout adult life.
Limitations and Challenges
The main limitation is cosmetic appearance, which can be difficult for some families to accept initially. Other considerations include:
- Lifelong use of a prosthetic limb.
- Need for intensive physiotherapy.
- Shoe and clothing modifications.
- Not suitable for every tumor.
Meeting patients who have undergone rotationplasty often helps families better understand its excellent functional outcomes.
Life After Rotationplasty
Recovery includes wound healing, physiotherapy, and prosthetic training. Most children gradually learn to walk independently, climb stairs, cycle, attend school, and participate in many sports. Younger children often adapt remarkably well, and long-term studies show high levels of independence, quality of life, and patient satisfaction.
Patient Tip
The appearance of rotationplasty may seem overwhelming initially. Meeting another child or adult who has undergone the procedure can help families appreciate its excellent long-term function.
Doctor Insight
The success of rotationplasty is measured not by how the limb looks, but by how well the child functions. Many children go on to walk, run, play sports, and live active, independent lives for decades.
Reassurance Box
It is natural for parents to have concerns about the appearance of rotationplasty. However, many families later report that cosmetic appearance became far less important than their child’s ability to walk comfortably, participate in sports, and enjoy an active, independent life. Your surgical team will help you choose the reconstructive option that best balances cancer control, function, growth, and long-term quality of life.
Comparison of Surgical Reconstruction Options
Clinical Pearl
The choice of reconstruction is never based on a single factor. Surgeons carefully balance cancer control, future growth, expected function, durability of reconstruction, and the child’s overall well-being before recommending the most appropriate option.
Reassurance Box
Parents often fear that choosing one surgical option means “settling” for a less effective treatment. In reality, every recommendation is made with the same primary objective: achieving the best possible chance of cure while maximizing your child’s long-term quality of life. The “best” operation is the one that offers the safest cancer treatment and the most functional outcome for your child’s individual circumstances.
Rehabilitation After Pediatric Bone Tumor Treatment
Treatment does not end with surgery or chemotherapy. Rehabilitation is an essential part of recovery, helping children regain movement, strength, independence, and confidence. Each rehabilitation program is individualized based on the child’s age, tumor type, surgery, reconstruction, and additional treatments such as chemotherapy or radiotherapy.
Why Is Rehabilitation Important?
After treatment, muscles may become weak, joints stiff, and mobility limited. Rehabilitation helps children:
- Restore joint movement and muscle strength.
- Improve balance, coordination, and walking.
- Reduce pain and stiffness.
- Regain independence in daily activities.
- Support physical, emotional, and social recovery.
Recovery progresses gradually under the guidance of a multidisciplinary team.
Doctor Explains
Rehabilitation is more than physiotherapy. It also includes pain management, nutritional support, psychological care, school reintegration, and helping children safely return to everyday activities.
Recovery in the Hospital
Rehabilitation begins soon after surgery. Early care focuses on pain control, wound healing, preventing complications, gentle exercises, and safe mobilization. Depending on the surgery, children may temporarily use crutches, a walker, wheelchair, or prosthetic limb. Early movement helps reduce stiffness, improve circulation, and speed recovery.
Physiotherapy
A pediatric physiotherapist develops an individualized program that may include:
- Range-of-motion and strengthening exercises.
- Balance and gait training.
- Stair climbing and functional activities.
- Prosthetic training, when required.
As recovery progresses, therapy focuses on restoring normal daily activities and independence.
Learning to Walk Again
Whether a child walks normally again depends on the tumor location and the type of reconstruction. Many children regain independent walking after limb salvage surgery, while those undergoing rotationplasty or amputation receive specialized prosthetic training. Young children often adapt remarkably well, but recovery occurs over weeks to months, not days.
Patient Tip
Every child recovers differently. Celebrate each milestone and avoid comparing your child’s progress with others.
Returning to School
Returning to school restores routine, friendships, and confidence. The timing depends on recovery, chemotherapy schedules, and overall health. Schools should be informed about temporary activity restrictions, mobility aids, and medical appointments to help ensure a smooth transition.
Returning to Sports and Physical Activity
Physical activity is encouraged once healing is adequate. Walking, swimming, and cycling are often suitable, while high-impact sports may not be advisable after some reconstructions. Your healthcare team will recommend activities based on your child’s recovery.
Emotional Recovery
Recovery involves emotional as well as physical healing. Children may experience anxiety, body-image concerns, or frustration during rehabilitation. Support from family, psychologists, teachers, and support groups can help children adjust and regain confidence.
Doctor Insight
Children are remarkably resilient. With rehabilitation and encouragement, many regain confidence through milestones such as taking their first independent steps, returning to school, or resuming favorite activities.
Did You Know?
Children often recover movement faster than adults because their growing bones, muscles, and nervous systems have an exceptional ability to adapt.
Reassurance Box
Recovery takes time, and temporary setbacks are common. With patience, structured rehabilitation, and ongoing support, many children return to school, participate in recreational activities, and lead active, fulfilling lives.
Clinical Pearl
Successful rehabilitation begins before surgery. Preparing families, setting realistic expectations, and involving physiotherapists early are key to achieving the best long-term functional outcomes.
Why Is Long-Term Follow-up Important?
Completing treatment is a major milestone, but it is not the end of your child’s journey. Long-term follow-up is an essential part of pediatric bone tumor care, ensuring your child remains healthy, continues to grow normally, and achieves the best possible long-term function.
Regular follow-up helps the healthcare team:
- Detect tumor recurrence early.
- Monitor healing after surgery.
- Assess reconstructed bones or prosthetic implants.
- Identify growth-related problems.
- Monitor late effects of chemotherapy or radiotherapy.
- Support your child’s physical, emotional, and social development.
Even if your child feels well, follow-up appointments remain important because some problems develop gradually without obvious symptoms.
Table: What Is Monitored During Long-Term Follow-up?
Doctor Insight
Long-term follow-up is about more than detecting recurrence. It helps ensure your child continues to grow, develop, and enjoy the best possible quality of life.
Transition to Adult Care
As children become young adults, care is gradually transferred to adult orthopaedic oncology and survivorship services. Even after skeletal maturity, some patients require periodic follow-up to monitor reconstruction, prosthetic implants, and overall function.
Patient Tip
Keep a record of your child’s diagnosis, surgeries, chemotherapy, imaging reports, and follow-up visits. A personal treatment summary is invaluable when transitioning to a new healthcare team.
Reassurance Box
Many parents experience “scan anxiety” before follow-up visits. These feelings are completely normal. Remember that most appointments are routine, and the majority of children continue to recover without major problems.
Possible Complications
Modern treatment for pediatric bone tumors is highly effective, and most children recover without serious complications. However, every treatment carries some risks, and understanding them helps families recognize warning signs early without unnecessary anxiety.
Surgical Complications
Although uncommon, surgery may occasionally lead to:
- Infection or wound healing problems.
- Bleeding.
- Injury to nearby nerves or blood vessels.
- Delayed bone healing or graft fracture.
- Implant loosening or mechanical failure.
- Joint stiffness.
Most of these complications can be treated successfully, particularly when identified early.
Treatment-Related Complications
Chemotherapy and radiotherapy may cause temporary or long-term side effects, including fatigue, low blood counts, increased susceptibility to infection, effects on growth, fertility concerns, or heart, kidney, and hearing problems. Your oncology team monitors these throughout treatment and follow-up.
Growth-Related Challenges
As children continue to grow, some may develop:
- Limb-length discrepancy.
- Angular deformity.
- Joint stiffness.
- Reduced muscle strength.
- Need for future reconstructive procedures.
Regular follow-up helps detect these problems early and allows timely treatment when needed.
Reassurance Box
Most complications are possibilities, not expectations. Advances in surgery, chemotherapy, rehabilitation, and long-term follow-up have significantly improved outcomes. With regular monitoring and prompt treatment of any concerns, the majority of children recover well and go on to lead active, healthy lives.
Prognosis: What Is the Outlook for Children with Bone Tumors?
A common question parents ask is, “Will my child be cured?” The outlook depends on the type of tumor, whether it is benign or malignant, the stage at diagnosis, response to treatment, and whether the tumor can be completely removed.
Most benign bone tumors have an excellent prognosis, with children returning to normal activities after treatment. For malignant tumors, advances in chemotherapy, limb salvage surgery, and supportive care have significantly improved outcomes, and many children with localized osteosarcoma or Ewing sarcoma can be successfully treated.
Doctor Insight
Prognosis is individualized. While survival statistics are helpful, they cannot predict the outcome for any one child. Your treating team can provide the most accurate information based on your child’s condition.
Reassurance Box
Many children treated for bone tumors return to school, sports, higher education, and lead active, fulfilling adult lives.
Supporting Your Child and Family Through Treatment
A bone tumor diagnosis affects the entire family. Open communication, maintaining routines, encouraging school and social activities, celebrating milestones, and seeking emotional support can help children cope better. Parents should also look after their own well-being, as supported caregivers are better able to care for their child.
Patient Tip
You are not alone. Lean on your healthcare team, family, friends, teachers, and support groups. Asking for help is a sign of strength, not weakness.
Frequently Asked Questions
1. Can my child be cured?
Many children with benign bone tumors are cured with observation or surgery alone. For malignant bone tumors, treatment outcomes have improved significantly, and many children with localized disease can be successfully treated.
2. Will my child lose an arm or leg?
Not necessarily. Modern limb salvage surgery allows many children to keep their limb while achieving excellent cancer control. However, amputation remains the safest option in some situations.
3. Why does my child need chemotherapy before surgery?
Preoperative (neoadjuvant) chemotherapy helps shrink the tumor, treats microscopic cancer cells elsewhere in the body, and provides information about how the tumor responds to treatment.
4. Will treatment affect my child’s growth?
It can, particularly if the growth plate must be removed during surgery. Your healthcare team will discuss strategies to preserve growth or compensate for future limb-length differences whenever possible.
5. Can my child return to school?
Yes. Most children gradually return to school during or after treatment, although the timing depends on recovery, chemotherapy schedules, and overall health.
6. Can children play sports after treatment?
Many children return to recreational activities after recovery. The type of sport that is safe depends on the reconstruction performed, bone healing, and your surgeon’s recommendations.
7. Will my child need more surgery in the future?
Some children, particularly those with expandable prostheses or growing reconstructions, may require additional procedures as they grow. Others may never need further surgery after completing treatment.
8. How often will follow-up visits be needed?
Follow-up is usually more frequent during the first few years after treatment and gradually becomes less frequent over time. The schedule is individualized for each child.
9. Should we get a second opinion?
Seeking a second opinion is entirely reasonable, particularly before major surgery. It can help families better understand the diagnosis and treatment options while providing additional reassurance.
10. Can my child live a normal life after treatment?
Many children treated for bone tumors grow into healthy, independent adults who attend school, pursue careers, participate in sports and hobbies, and enjoy fulfilling family and social lives.
11. Is every bone tumor in a child cancer?
No. In fact, most bone tumors in children are benign (non-cancerous). Conditions such as osteochondroma, non-ossifying fibroma, and simple bone cysts are much more common than malignant tumors. However, because some malignant bone tumors can initially resemble benign conditions, any persistent bone pain, swelling, or unexplained fracture should be evaluated by a doctor.
12. How long does treatment usually take?
The duration of treatment depends on the type of tumor and the treatment required.
13. Can the bone tumor come back after treatment?
Yes, although many children remain disease-free after successful treatment.
14. Will my child need a prosthetic limb after surgery?
Not always. A prosthetic limb is required only after procedures such as amputation or rotationplasty. Children who undergo limb salvage surgery usually keep their own limb, although they may receive an internal implant (endoprosthesis) or a biological reconstruction instead of an external artificial limb.
15. When should we seek care at a specialized bone tumor center?
Children should ideally be referred to a specialized center before any biopsy or surgery whenever a bone tumor is suspected.
References
- Hopyan S, Tan JW, Graham HK, Torode IP. Function and upright time following limb salvage, amputation, and rotationplasty for pediatric sarcoma of bone. J Pediatr Orthop. 2006;26(3):405–8.
- Kumta SM, Cheng JC, Ii CK, Griffith JF, Chow LT, Quintos AD. Scope and limitations of limb-sparing surgery in childhood sarcomas. J Pediatr Orthop. 2002;22(2):244–8.
- Schindler OS, Cannon SR, Briggs TWR, Blunn GW. Expanding endoprosthesis for pediatric musculoskeletal malignancy: current concepts and results. Int Orthop. 2010;34(8):1221-1232.
- Winkelmann W. Rotationplasty. Orthop Clin North Am. 1996;27(3):503-523.
- Tang N, Yang J, Huang S, Tang X, Ji T. Development and clinical application of extendable prostheses in limb salvage surgery for primary malignant bone tumours in children: a systematic review of functional outcomes and complications. Bone Joint Res. 2025;14(6):578-588.
- Ferrari S, Bielack SS, Smeland S, Whelan JS. Surgical treatment of bone sarcoma. Cancers (Basel). 2022;14(11):2694.
- Healey JH, Morris CD. Limb salvage in musculoskeletal oncology: recent advances. World J Orthop. 2014;5(2):89-95.
Medical Disclaimer
The information provided on this page is intended for educational purposes only and should not be considered a substitute for professional medical advice, diagnosis, or treatment. Every child with a bone tumor is unique, and treatment decisions should always be made after careful evaluation by a qualified healthcare team. If you have concerns about your child’s condition or treatment, consult your orthopaedic oncologist or pediatric oncology specialist for personalized medical advice.
 +91 93558 33005

