Quick Summary
- Limb salvage surgery removes the tumor while preserving the arm or leg whenever it is oncologically safe.
- The primary goal is complete cancer removal; limb preservation is the second goal.
- Modern limb salvage is possible for many patients with bone tumors and selected soft tissue sarcomas.
- Reconstruction may involve a mega prosthesis, biological reconstruction, or other specialized techniques.
- Most patients require structured rehabilitation after surgery.
- Not every patient is a candidate, and in selected situations amputation remains the safest treatment.
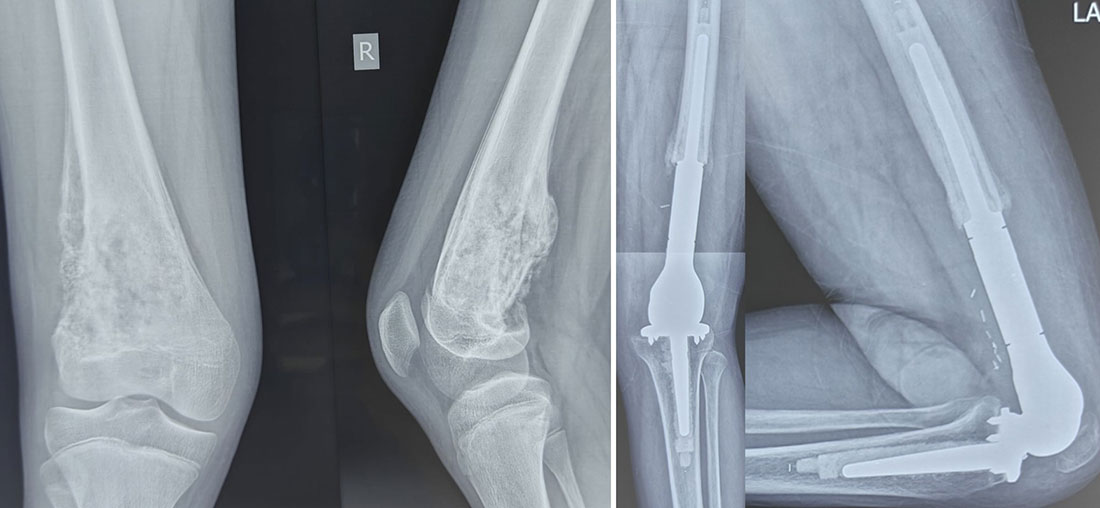
Figure 1. From Bone Tumor to Limb Salvage
Tumor prosthesis after removal of a bone tumor, restoring the affected bone and joint and allowing limb-salvage surgery.
A diagnosis of a bone tumor often brings one overwhelming question:
“Will I lose my arm or leg?”
For many patients and families, the fear of amputation can be as distressing as the diagnosis itself. Fortunately, remarkable advances in orthopaedic oncology over the past few decades mean that many patients who once required amputation can now undergo limb salvage surgery.
However, the priority is always complete removal of the tumor with an adequate margin of healthy tissue. Limb preservation is pursued only when it does not compromise the safety or effectiveness of cancer treatment.
This guide explains how limb salvage surgery is planned, who is a suitable candidate, how reconstruction is performed, what recovery involves, and what life may look like after surgery. Whether you are a patient, family member, or referring doctor, understanding these principles will help you make informed decisions and know what to expect throughout the treatment journey.
What is Limb Salvage Surgery?
Limb Salvage Surgery (also called limb-sparing surgery) is a specialized operation performed to remove a bone or soft tissue tumor while preserving the affected arm or leg whenever it is safe to do so.
Instead of removing the entire limb (amputation), the surgeon removes the tumor along with a margin of healthy tissue and then reconstructs the resulting defect using techniques such as a mega prosthesis (tumor prosthesis), biological bone reconstruction, bone grafts, or custom implants.
Today, advances in imaging, chemotherapy, surgical techniques, and reconstruction mean that most patients with primary bone tumors can be treated without amputation. However, limb salvage is appropriate only when it allows complete tumor removal without compromising cancer control.
The decision is individualized for every patient and is made by a multidisciplinary sarcoma team after careful review of imaging, biopsy findings, tumor location, and overall health. Every patient is different. Factors such as the type of tumor, its size, response to chemotherapy, involvement of nearby nerves or blood vessels, and the patient’s age, activity level, and overall health all influence the surgical plan.
The aim of limb salvage surgery extends beyond simply avoiding amputation. It is about helping patients regain independence, maintain mobility, and return to meaningful daily activities while achieving the best possible cancer control.
Clinical Pearl
The success of limb salvage surgery is measured not only by preserving the limb but by achieving complete tumor removal, durable reconstruction, and meaningful long-term function.
Doctor Explains
Is Limb Salvage Better Than Amputation?
Neither procedure is “better” for every patient.
The best operation is the one that removes the tumor completely while providing the safest and most functional long-term outcome.
For many patients, limb salvage offers excellent function and quality of life. However, if complete tumor removal cannot be achieved safely or the expected function after limb salvage would be poor, amputation may provide the better overall result.
This decision is individualized and should always be made after careful discussion with an experienced orthopaedic oncologist.
Did You Know?
💡 Today, the majority of patients with primary bone sarcomas of the limbs can undergo limb salvage surgery, thanks to advances in MRI, chemotherapy, surgical planning, and reconstructive techniques. Nevertheless, careful patient selection remains essential to ensure the best oncological and functional outcomes.
Patient Tip
Before discussing reconstruction options, ask your surgeon:
- Am I a candidate for limb salvage surgery?
- What factors influence this decision in my case?
- What level of function can I realistically expect after recovery?
Understanding the reasons behind your treatment plan often reduces anxiety and helps you participate in shared decision-making.
If You Have Been Told You May Need Limb Salvage Surgery
It is normal to feel anxious when facing major surgery.
Remember these important points:
- Limb salvage surgery is a well-established treatment, not an experimental procedure.
- Every operation is carefully planned using detailed imaging and biopsy results.
- The goal is to remove the tumor completely while preserving as much normal function as possible.
- If limb salvage is recommended, it means your team believes it can be performed without compromising cancer treatment.
- If amputation is advised instead, it is because your doctors believe it offers the safest chance of long-term disease control or better overall function in your specific situation.
Take time to ask questions, involve your family in discussions, and seek a second opinion if you feel uncertain. Decisions about limb salvage and amputation are among the most important choices in orthopaedic oncology and should always be made with a clear understanding of the benefits, limitations, and expected outcomes.
Key Facts Box
Can My Limb Be Saved?
For most patients, this is the first and most important question after being diagnosed with a bone tumor.
The encouraging news is that many patients with bone tumors can now undergo limb salvage surgery instead of amputation. However, the decision is never based on a single scan or one test. It requires careful evaluation by an experienced multidisciplinary sarcoma team, including an orthopaedic oncologist, radiologist, pathologist, medical oncologist, radiation oncologist (when appropriate), and reconstructive specialists.
The decision is guided by one fundamental principle:
The tumor must be removed completely without compromising cancer control.
If preserving the limb would increase the risk of leaving tumor behind or significantly compromise long-term function, another treatment option—including amputation—may provide a safer and more durable outcome.
How We Decide Between Limb Salvage and Amputation
There is no single rule that determines whether a limb can be saved. Instead, surgeons assess several factors together to determine which approach offers the best balance between cancer control, safety, and long-term function.
The most important considerations include:
1. Can the Tumor Be Removed Completely?
The first priority is to achieve a wide surgical margin, meaning the tumor is removed along with a cuff of normal tissue surrounding it. This reduces the risk of leaving microscopic tumor cells behind.
If a complete removal can be achieved while preserving essential structures, limb salvage is often possible.
If this cannot be achieved safely, amputation may provide better oncological control.
2. Are the Major Nerves and Blood Vessels Involved?
Large nerves control movement and sensation, while major blood vessels supply the limb with oxygen-rich blood.
If the tumor surrounds or extensively invades these critical structures, limb salvage becomes more complex. In selected patients, blood vessels can be reconstructed, but extensive nerve involvement may result in a limb that has little useful function despite being preserved.
The aim is to preserve a useful limb, not simply retain the limb itself.
3. How Much Bone and Soft Tissue Must Be Removed?
Some tumors require removal of:
- A small segment of bone.
- An entire joint.
- Large portions of surrounding muscles.
- Tendons or ligaments.
The greater the amount of tissue removed, the more complex the reconstruction and rehabilitation.
Modern reconstructive techniques allow many large defects to be reconstructed successfully, but realistic expectations remain essential.
4. Has the Tumor Responded to Chemotherapy?
For tumors such as osteosarcoma and Ewing Sarcoma, chemotherapy is usually given before surgery.
A good response often:
- Shrinks the tumor.
- Makes surgery technically easier.
- Improves the likelihood of preserving important structures.
Although response alone does not determine whether limb salvage is possible, it is an important part of surgical planning.
5. What Function Can Be Expected After Surgery?
Preserving the limb is meaningful only if the reconstructed limb is expected to provide reasonable long-term function.
Your surgeon considers questions such as:
- Will you be able to walk independently?
- Will the reconstructed joint be stable?
- Will the hand or foot remain functional?
- Will pain be manageable?
- What activities are realistically achievable after rehabilitation?
Sometimes a well-fitted prosthetic limb following amputation may provide better long-term function than a severely compromised salvaged limb.
Doctor Explains
Saving the Limb Is Not the Same as Saving Its Function
Patients often believe that keeping the limb is always the best outcome. In reality, the goal is to preserve a limb that is functional, durable, and free of disease.
If a preserved limb would remain painful, unstable, or non-functional, another treatment option may ultimately provide a better quality of life.
Every recommendation is made with your long-term wellbeing in mind.
Clinical Pearl
The decision between limb salvage and amputation is based on oncological safety first and functional outcome second. The objective is not simply to preserve the limb but to preserve a limb that will serve the patient well in the long term.
Who Is a Candidate for Limb Salvage Surgery?
Many patients with primary bone tumors are suitable candidates, particularly when the tumor is localized and can be removed completely.
Patients who may be considered include those with:
- Osteosarcoma
- Ewing Sarcoma
- Chondrosarcoma
- Giant Cell Tumor of Bone
- Selected metastatic bone tumors
- Selected soft tissue sarcomas involving bone
Suitability depends on the individual characteristics of the tumor rather than the diagnosis alone.
Patient Tip
Ask your surgeon:
- Why do you think limb salvage is suitable for me?
- What structures will be removed?
- What type of reconstruction do you recommend?
- What level of function should I realistically expect one year after surgery?
These questions often provide more useful information than simply asking whether the limb can be saved.
Does Being Offered Amputation Mean My Cancer Is Worse?
Not necessarily.
Sometimes amputation is recommended not because the cancer is more aggressive, but because it provides the safest and most reliable way to remove the tumor while offering the best long-term function.
The recommendation is based on the location of the tumor, involvement of important structures, and expected functional outcome, rather than on a single factor.
When Is Amputation Still Necessary?
Although limb salvage has become the standard approach for many patients, amputation remains the best treatment in selected situations.
Examples include:
- Extensive involvement of major nerves where useful limb function cannot be preserved.
- Tumors that cannot be completely removed with safe margins.
- Severe infection preventing successful reconstruction.
- Recurrent tumors after previous limb salvage in selected patients.
- Situations where reconstruction would be unlikely to provide a durable, functional limb.
Modern amputation surgery, combined with advanced prosthetic technology and rehabilitation, allows many patients to return to highly active and independent lives.
Doctor Insight
One of the most difficult conversations in orthopaedic oncology is discussing amputation. While preserving a limb is always considered, recommending amputation when appropriate reflects a commitment to the patient’s long-term survival, function, and quality of life rather than simply avoiding a major operation.
Seek an Orthopaedic Oncology Opinion Before Amputation If:
- A bone tumor has been diagnosed but no multidisciplinary discussion has taken place.
- Amputation has been recommended before a biopsy-confirmed diagnosis.
- You have not been offered an opinion from a specialist sarcoma centre.
- You would like to understand whether modern limb salvage techniques could be appropriate in your case.
A second opinion may clarify the available treatment options and help you make an informed decision.
- How We Decide Between Limb Salvage and Amputation: An Orthopaedic Oncologist Explains
“What exactly happens before and during the operation?”
Planning the Surgery
Limb salvage surgery begins long before the day of the operation. Careful planning is one of the most important factors determining whether the surgery will successfully remove the tumor while preserving function.
Every patient undergoes an individualized evaluation that considers the tumor, the surrounding anatomy, and the most appropriate method of reconstruction. This planning is carried out by a multidisciplinary team to ensure that cancer control and long-term function remain the priorities.
Why Careful Planning Matters
Unlike routine orthopaedic procedures, limb salvage surgery is not a standard operation. Every tumor differs in its location, size, relationship to nearby structures, and response to treatment.
Before surgery, your team must answer several critical questions:
- How far has the tumor spread within the bone?
- Has it extended into the surrounding muscles?
- Are important nerves or blood vessels involved?
- Can the nearby joint be preserved?
- What amount of bone must be removed?
- Which reconstruction will provide the best long-term function?
Answering these questions before entering the operating room allows surgeons to perform the operation safely and precisely.
Doctor Insight
Successful limb salvage surgery depends far more on meticulous planning than on technical skill alone. A carefully planned operation minimizes unexpected findings during surgery and improves both oncological and functional outcomes.
Preoperative Evaluation
Several investigations are required before surgery, each serving a specific purpose.
MRI (Magnetic Resonance Imaging)
MRI uses magnetic fields to produce highly detailed images of the tumor and surrounding soft tissues.
It helps the surgical team determine:
- The exact length of bone involved.
- Extension into nearby muscles.
- Relationship to nerves and blood vessels.
- Joint involvement.
- The appropriate level of bone resection.
MRI is the single most important investigation for planning limb salvage surgery.
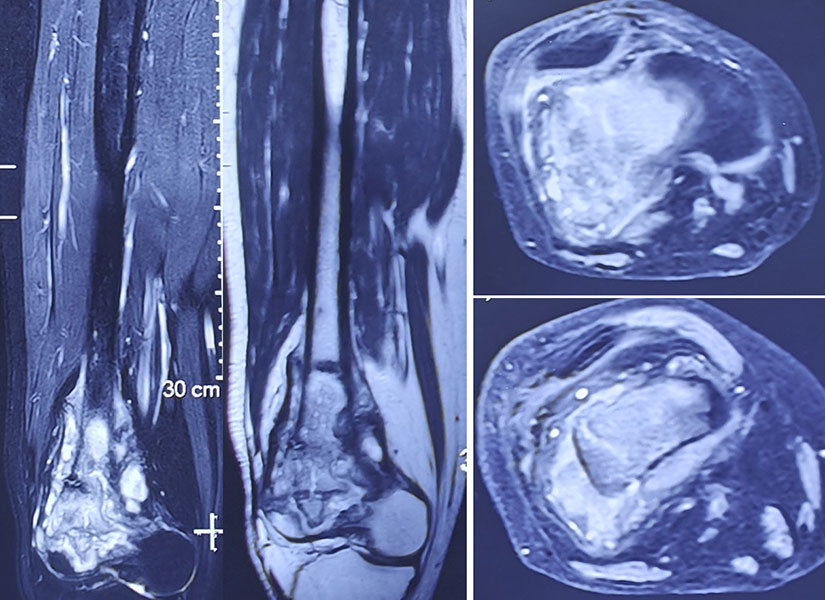
Figure 2. MRI of a distal femur osteosarcoma, showing the extent of the tumour and its relationship to surrounding structures. Careful MRI assessment helps plan safe limb-salvage surgery while achieving adequate tumour removal.
MRI for Bone Tumors
CT Scan (Computed Tomography)
CT provides excellent visualization of bone and helps assess:
- Cortical bone destruction.
- Complex anatomical regions such as the pelvis.
- Implant sizing and reconstruction planning.
- Three-dimensional anatomy.
In selected patients, CT images may also be used for computer-assisted planning or 3D-printed surgical guides.
PET-CT and Chest CT
These investigations help determine whether the cancer has spread beyond the primary site.
Although they do not directly influence the technical steps of reconstruction, they are essential for determining the overall treatment strategy.
Biopsy Review
Before surgery, the surgical team carefully reviews:
- Histopathology
- Molecular diagnosis (when applicable)
- Biopsy tract location
The biopsy tract is planned so that it can be removed together with the tumor during definitive surgery, reducing the risk of leaving behind tumor cells.
Bone Tumor Biopsy
Clinical Pearl
A biopsy should be performed only after appropriate imaging and, whenever possible, at the centre where definitive surgery will be undertaken. Proper biopsy planning protects future limb salvage options.
What Happens During Limb Salvage Surgery?
Although every operation is unique, most limb salvage procedures follow the same general principles.
Step 1. Tumor Exposure
The surgeon carefully exposes the affected bone while protecting healthy muscles, nerves, and blood vessels.
Step 2. Wide Tumor Resection
The tumor is removed en bloc, meaning it is removed in one piece along with a surrounding margin of healthy tissue.
This technique reduces the risk of leaving microscopic tumor cells behind.
Step 3. Reconstruction
After the tumor has been removed, the resulting bone defect is reconstructed using the most appropriate technique.
Depending on the individual patient, reconstruction may involve:
- Mega prosthesis
- Biological reconstruction
- Bone grafts
- Expandable prosthesis
- Custom implants
The choice depends on the patient’s age, tumor location, expected function, and remaining bone.
Step 4. Soft Tissue Reconstruction
The surrounding muscles, tendons, and other soft tissues are repaired or reconstructed to:
- Protect the implant.
- Improve stability.
- Restore movement.
- Reduce the risk of infection.
Occasionally, plastic surgeons assist with soft tissue coverage using muscle or skin flaps.
What We Look For During Surgery
Although every operation is individualized, the surgical team continuously assesses several important factors.
These include:
Complete Tumor Removal
The highest priority is removing the tumor with an adequate margin of healthy tissue.
Healthy Surgical Margins
The removed specimen is assessed to ensure that the margins are free of tumor. Achieving negative margins significantly reduces the risk of local recurrence.
Preservation of Function
Whenever oncologically safe, surgeons preserve:
- Muscles
- Tendons
- Joints
- Nerves
- Blood vessels
Preserving these structures contributes to better long-term mobility and function.
Stable Reconstruction
The reconstruction must provide:
- Mechanical stability
- Proper limb alignment
- Appropriate limb length
- Durable fixation
A stable reconstruction allows rehabilitation to begin safely.
Doctor Explains
What Are Surgical Margins?
A surgical margin is the rim of normal tissue removed together with the tumor.
Removing a margin of healthy tissue helps ensure that microscopic cancer cells are not left behind, reducing the risk of the tumor returning in the same area.
Your surgeon plans these margins carefully before the operation using MRI and other imaging studies.
Clinical Pearl
The goal is not simply to remove the visible tumor but to remove all potentially involved tissue while preserving as much normal anatomy as safely possible.
Common Mistakes to Avoid
Certain avoidable errors can complicate treatment and reduce the likelihood of successful limb salvage.
These include:
- Performing surgery before obtaining a biopsy-confirmed diagnosis.
- Inadequate MRI evaluation before surgery.
- Biopsy performed through an inappropriate surgical approach.
- Internal fixation of a suspected tumor before specialist assessment.
- Delayed referral to an orthopaedic oncology centre.
Early referral allows optimal planning and improves the chances of successful limb preservation.
Seek Specialist Evaluation Before Surgery If:
- A bone tumor is suspected on X-ray or MRI.
- Surgery has been recommended before a biopsy.
- A pathological fracture has occurred through a suspected tumor.
- You are uncertain whether limb salvage is possible.
Early specialist involvement helps avoid procedures that may compromise future treatment options.
Patient Tip
Bring copies of your MRI, CT scans, pathology report, biopsy slides (if available), and previous treatment records to your consultation. Having complete information enables the multidisciplinary team to develop the safest and most effective surgical plan.
Reconstruction Options After Limb Salvage Surgery
Once the tumor has been completely removed, the remaining bone and surrounding tissues must be reconstructed to restore stability, movement, and function.
Patients often ask, “Which option is right for me, and what can I expect?”
There is no single reconstruction that is best for every patient. The ideal method depends on several factors, including:
- The patient’s age and activity level
- The type and location of the tumor
- The amount of bone removed
- Whether a joint has been preserved
- Expected long-term survival
- The condition of the surrounding muscles and soft tissues
- Previous treatments such as chemotherapy or radiotherapy
The aim is to choose a reconstruction that provides the best balance between durability, function, and quality of life.
How Do We Choose the Best Reconstruction?
Selecting the reconstruction is as important as removing the tumor itself.
The decision is individualized after considering:
Tumor Location
Different parts of the skeleton require different reconstructive techniques.
For example:
- Around the knee → Mega prosthesis is often preferred.
- Mid-shaft of long bones → Biological reconstruction may be suitable.
- Pelvis → Custom implants or complex biological reconstruction.
- Shoulder → Endoprosthetic reconstruction or biological options depending on the extent of resection.
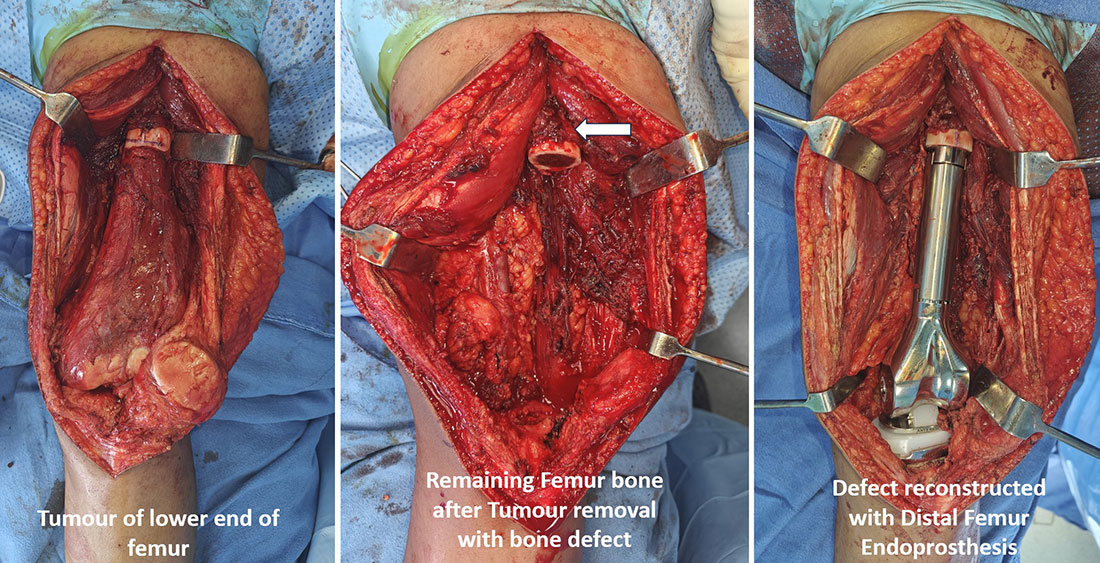
Figure 3. Distal Femur Tumor – Limb-Salvage Reconstruction
Removal of a distal femur tumor creates a bone defect that is reconstructed with a distal femur megaprosthesis, restoring limb length and alignment and allowing early weight bearing and mobilization.
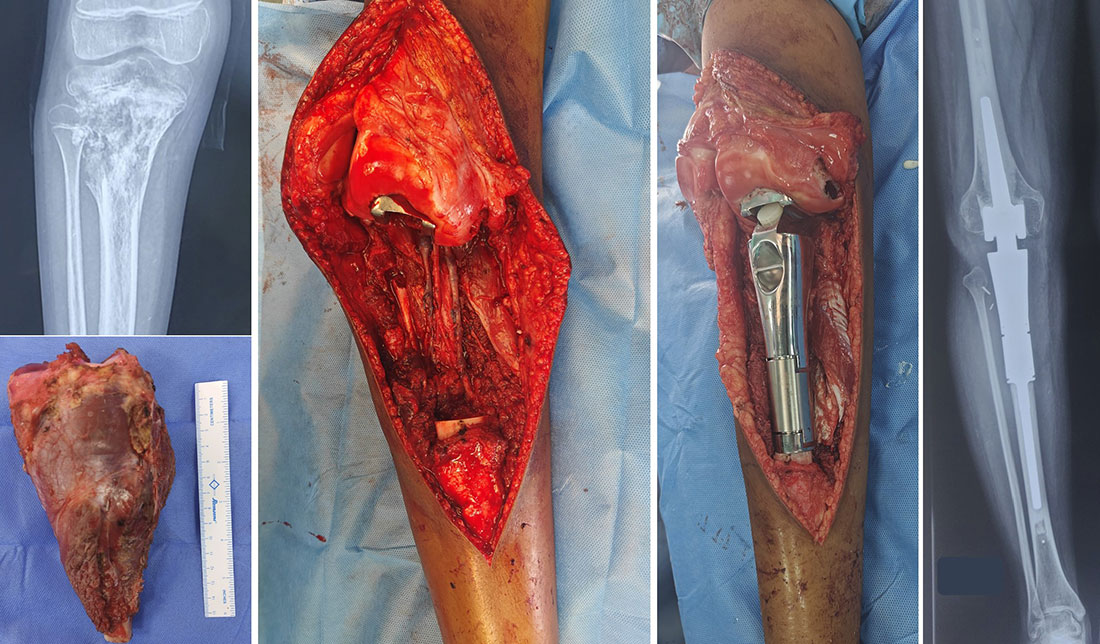
Figure 4. Proximal Tibia Tumor – Limb-Salvage Reconstruction
Removal of a proximal tibia tumor creates a bone defect that is reconstructed with a proximal tibia megaprosthesis, restoring limb length and alignment and allowing early weight bearing and mobilization.
Patient’s Age
Children present unique challenges because their bones continue to grow.
Whenever possible, reconstruction aims to preserve future growth and minimize limb-length inequality.
Adults generally require durable reconstruction that allows early mobilization and long-term function.
Bone and Soft Tissue Loss
Some tumors require removal of only bone, while others involve muscles, tendons, ligaments, or skin.
The greater the amount of tissue removed, the more complex the reconstruction becomes.
Expected Functional Demands
A young athlete, an office worker, and an elderly patient may all require different reconstructive strategies despite having similar tumors.
Lifestyle, occupation, and personal goals are important considerations during shared decision-making.
Clinical Pearl
The best reconstruction is not necessarily the most complex one. It is the option that offers the safest cancer treatment, the greatest durability, and the most useful long-term function for that individual patient.
Mega Prosthesis (Tumor Prosthesis)
A mega prosthesis, also called a tumor prosthesis or endoprosthesis, is an artificial metallic implant used to replace the section of bone and joint removed during tumor surgery.
It is the most commonly used method of reconstruction after limb salvage surgery involving the shoulder, hip, or knee.
Advantages
- Immediate structural stability.
- Early weight-bearing in many patients.
- Reliable restoration of limb length.
- No need for bone healing before mobilization.
- Widely used with predictable functional outcomes.
Limitations
- Mechanical wear over time.
- Risk of infection.
- Implant loosening.
- Occasional need for revision surgery.
Modern modular prostheses have significantly improved long-term durability compared with earlier designs.
Mega Prosthesis Surgery
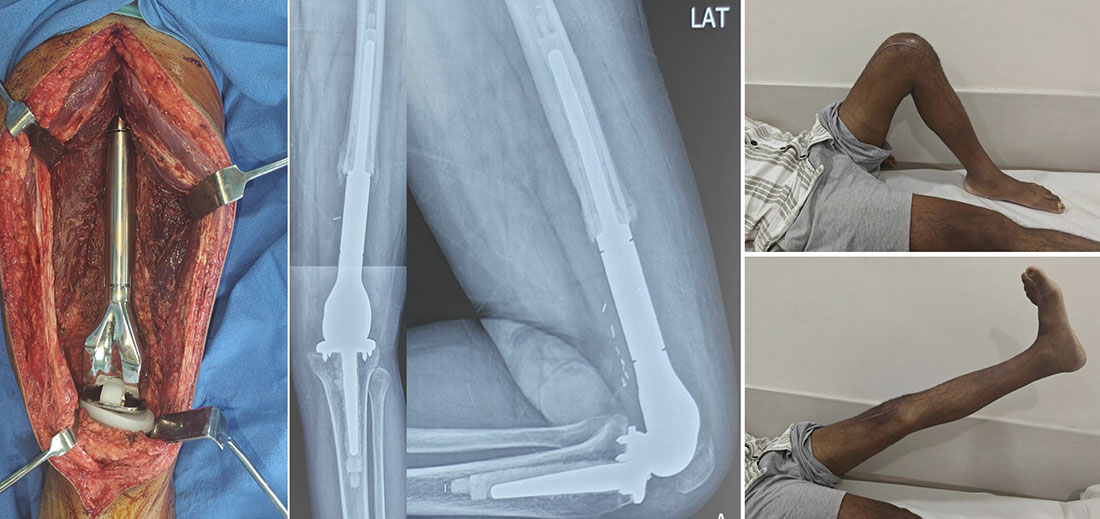
Figure 5. Distal Femur Tumor Prosthesis After Limb Salvage
Distal femur megaprosthesis used to reconstruct the knee after removal of a bone tumor, with good postoperative knee movement.
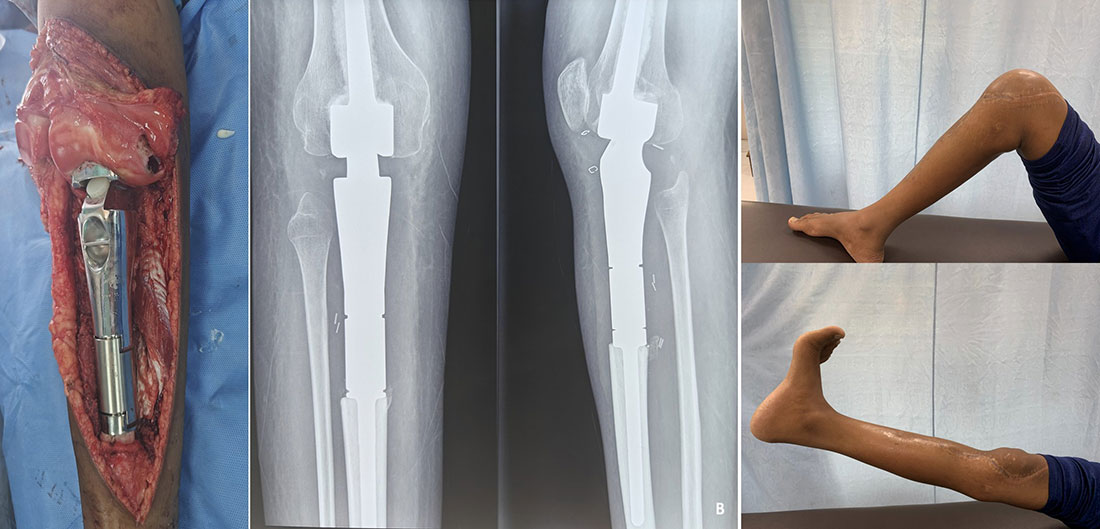
Figure 6. Proximal Tibia Megaprosthesis After Limb Salvage
Proximal tibia megaprosthesis reconstructing the knee after tumor removal, with good recovery of knee movement.
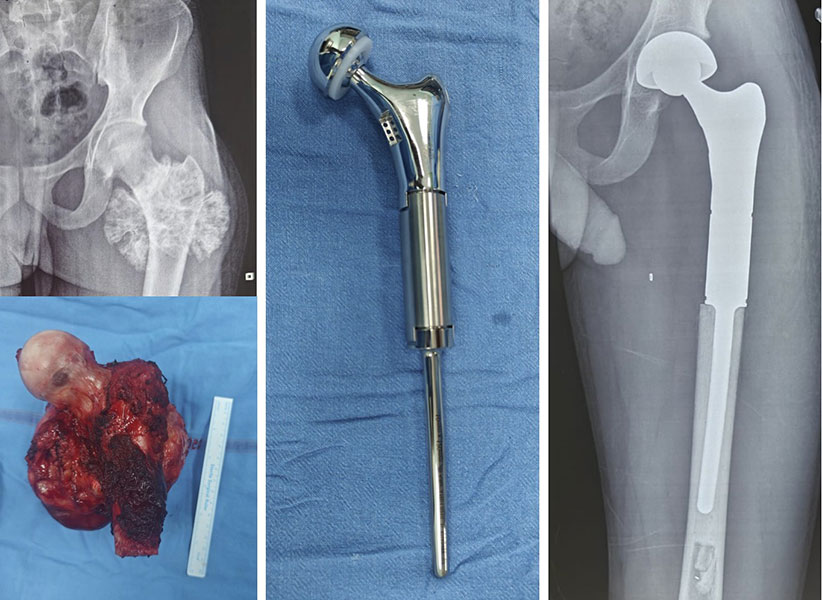
Figure 7. Proximal Femur Tumor Prosthesis After Limb Salvage
Proximal femur tumor removed and reconstructed with a tumor megaprosthesis to preserve the hip and limb.
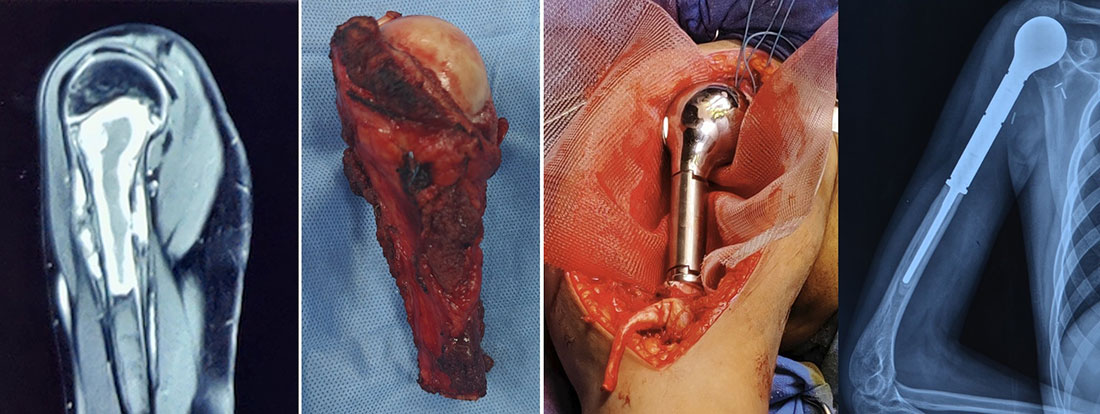
Figure 8. Proximal Humerus Megaprosthesis After Limb Salvage
Proximal humerus tumor removed and reconstructed with a megaprosthesis as part of limb-salvage surgery.
Doctor Explains
What Is a Mega Prosthesis?
A mega prosthesis is not the same as a routine hip or knee replacement performed for arthritis.
It is a specialized implant designed to replace large segments of bone removed during cancer surgery while restoring joint function and allowing patients to return to daily activities.
Biological Reconstruction
Biological reconstruction restores the bone using living tissue rather than an artificial implant.
Techniques may include:
- Autograft – bone taken from another part of the patient’s own body.
- Allograft – donor bone obtained from a tissue bank.
- Vascularized fibular graft – a segment of the fibula transferred with its blood supply intact.
- Reimplantation of treated bone (selected centres).
Biological reconstruction has the advantage of preserving living bone, which may remodel over time.
However, healing takes longer than with biological reconstruction and requires patience during rehabilitation.
Advantages
- Biological incorporation with the patient’s own skeleton.
- Potential for long-term durability.
- Suitable for selected younger patients.
Limitations
- Longer healing time.
- Risk of delayed union or non-union.
- Possibility of graft fracture.
- More prolonged rehabilitation.
Biological Reconstruction After Bone Tumor Surgery
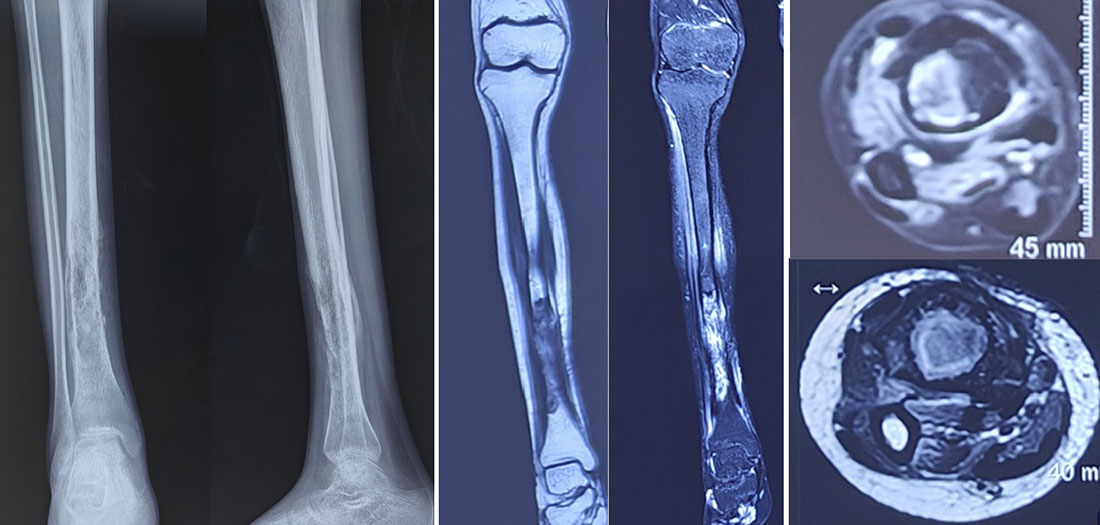
Figure 9A. Imaging shows an osteosarcoma of the tibia and its extent, helping the surgical team plan limb-salvage surgery.
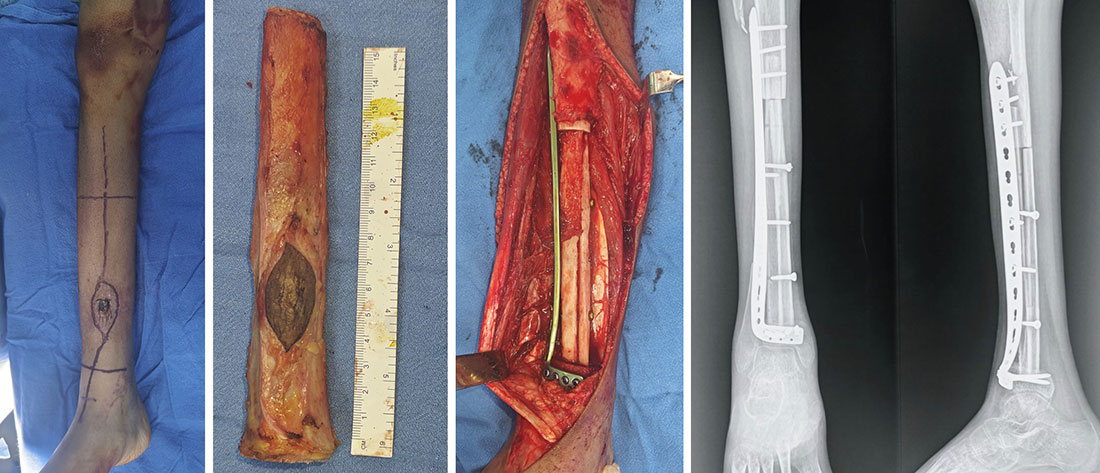
Figure 9B. The tumor was widely removed and the bone reconstructed using a vascularized fibular graft, preserving the limb and providing a biological solution for bone reconstruction.
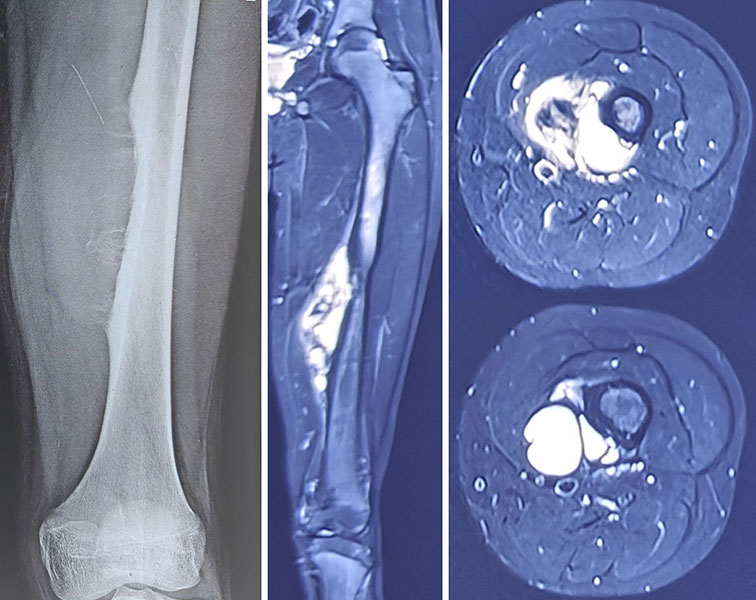
Figure 10A. X-ray and MRI reveal a Ewing sarcoma of the femur, allowing careful planning of limb-salvage surgery
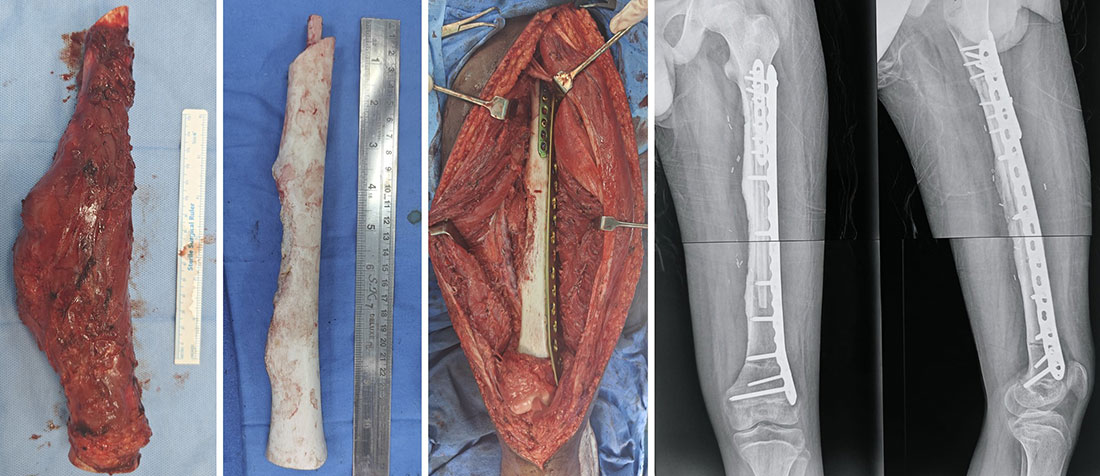
Figure 10B. After wide tumor removal, the affected bone was sterilized with high-dose radiation and reimplanted, allowing the patient’s own bone to be used for reconstruction and gradually incorporate with the surrounding bone.
Expandable Prosthesis in Children
Children present a unique challenge because their bones continue to grow.
If a growth plate must be removed during tumor surgery, one limb may become shorter than the other over time.
An expandable prosthesis is designed to gradually increase in length as the child grows, helping reduce limb-length discrepancy.
Not every child requires an expandable prosthesis. The decision depends on:
- Remaining growth potential.
- Tumor location.
- Expected limb-length difference.
- Overall treatment plan.
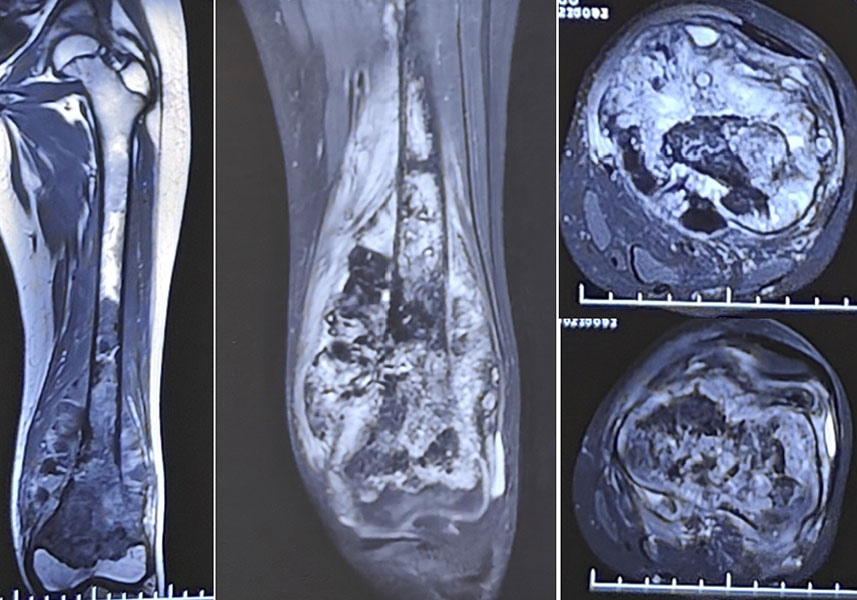
Figure 11A. Bone tumor involving the growth plate
Imaging showing a pediatric bone tumor extending into the growth plate, requiring careful surgical planning to achieve tumor removal while considering future growth.
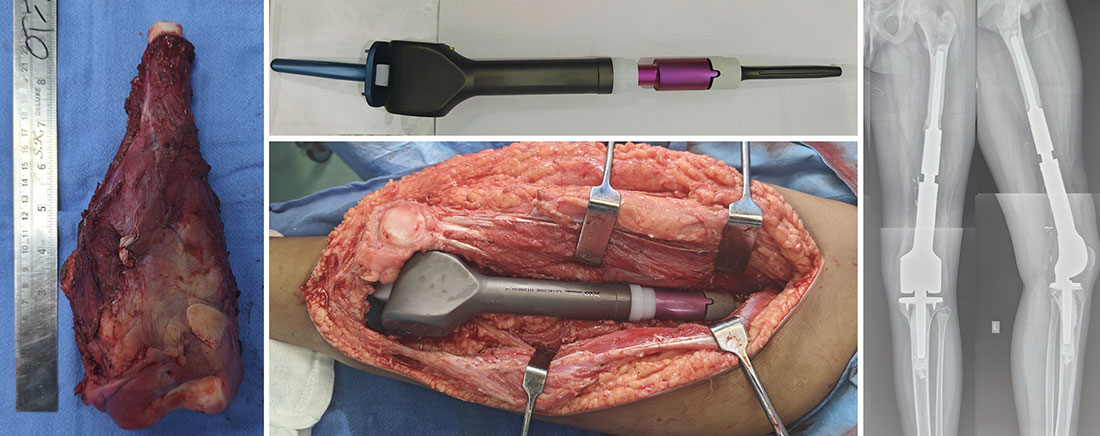
Figure 11B. Wide resection and expandable prosthetic reconstruction
Wide removal of osteosarcoma involving the growth plate followed by reconstruction with an expandable prosthesis designed to accommodate the child’s remaining growth.
Did You Know?
💡 Expandable prostheses can often be lengthened without major surgery using modern non-invasive systems, reducing the number of procedures required during childhood.
Figure 8. Expandable prosthesis used in a skeletally immature child.
Soft Tissue and Vascular Reconstruction
Removing the tumor is only one part of successful limb salvage.
The surrounding soft tissues—including muscles, tendons, ligaments, skin, nerves, and blood vessels—must also function effectively.
Depending on the extent of surgery, reconstruction may involve:
- Muscle flaps
- Skin flaps
- Tendon reconstruction
- Ligament repair
- Blood vessel reconstruction
- Collaboration with plastic or vascular surgeons
These procedures improve wound healing, protect the implant, restore movement, and reduce complications.
Doctor Insight
The durability of a reconstruction depends not only on the implant but also on the quality of the surrounding soft tissue envelope. Adequate muscle coverage and healthy blood supply are essential for long-term success.
Which Reconstruction Is Best?
There is no universally superior reconstruction technique.
Each option has distinct advantages and limitations.
The final decision is based on tumor characteristics, patient goals, expected function, and long-term durability, rather than on a single factor.
Patient Tip
Ask your surgeon:
- Why have you recommended this reconstruction?
- What alternatives are available?
- How long is the implant expected to last?
- Will additional surgery be needed in the future?
- What level of activity should I realistically expect after recovery?
Understanding the reasons behind the recommendation will help you make an informed decision.
Is One Reconstruction Better Than Another?
Not necessarily.
Every reconstruction has strengths and limitations.
The “best” reconstruction is the one that:
- Removes the tumor safely.
- Matches your age and activity level.
- Provides reliable long-term function.
- Minimizes future complications.
- Supports your rehabilitation goals.
Your surgeon’s recommendation is individualized and based on achieving the best overall outcome rather than simply choosing the newest implant or technique.
Recovery, Rehabilitation & Life After Limb Salvage Surgery
Patients want to know:
“What will my life be like after surgery?”
Recovering from limb salvage surgery is a gradual process. While the operation itself is an important milestone, successful recovery depends just as much on rehabilitation, patience, and long-term follow-up.
Every patient’s recovery is unique. It depends on:
- The type and location of the tumor
- The amount of bone and soft tissue removed
- The reconstruction performed
- Whether chemotherapy or radiotherapy was required
- Age and general health
- Commitment to rehabilitation
The aim of recovery is not simply healing the surgical wound—it is helping patients regain independence, mobility, confidence, and quality of life.
Hospital Recovery
Immediately after surgery, your medical team will focus on:
- Pain control
- Monitoring wound healing
- Preventing infection
- Protecting the reconstruction
- Beginning gentle movement exercises
- Preventing blood clots
Most patients begin sitting out of bed and performing simple physiotherapy exercises within the first few days, depending on the type of reconstruction.
Walking may begin early with the assistance of a physiotherapist, although weight-bearing depends on the reconstruction performed and your surgeon’s recommendations.
Patient Tip
Do not compare your recovery with that of other patients. Two people undergoing limb salvage surgery may have completely different rehabilitation timelines because their tumors, operations, and reconstructions are different.
Rehabilitation After Limb Salvage Surgery
Rehabilitation is one of the most important parts of successful treatment. Even the best surgical reconstruction requires structured physiotherapy to restore movement and strength.
The goals of rehabilitation include:
- Restoring joint movement
- Improving muscle strength
- Regaining balance and coordination
- Learning safe walking techniques
- Returning to daily activities
- Maximizing long-term independence
Depending on the surgery, your rehabilitation team may include:
- Physiotherapists
- Occupational therapists
- Rehabilitation physicians
- Prosthetists (if required)
- Psychologists
- Pain specialists
Rehabilitation After Bone Tumor Surgery
Recovery Timeline
Although recovery varies considerably, the following timeline provides a general guide.
Typical Recovery After Limb Salvage Surgery
Recovery after biological reconstruction is often slower than after mega prosthesis reconstruction because the transplanted bone must heal before full weight-bearing is permitted.
Clinical Pearl
Successful rehabilitation begins before surgery. Patients who understand the recovery process and actively participate in physiotherapy generally achieve better functional outcomes.
Returning to Everyday Life
One of the most encouraging aspects of modern limb salvage surgery is that many patients gradually return to an active and independent lifestyle.
The timing depends on the type of reconstruction and the progress of rehabilitation.
Walking
Most patients gradually progress from:
- Walker or frame
- Crutches
- Walking stick (when needed)
- Independent walking
Some patients with extensive muscle removal may require walking aids for longer periods.
Climbing Stairs
Stair climbing usually becomes easier as muscle strength improves.
Your physiotherapist will teach safe techniques before discharge from hospital.
Driving
Driving should only be resumed after:
- Adequate wound healing
- Good muscle control
- Safe reaction times
- Clearance from your surgeon
The timing varies depending on which limb was operated upon and the type of reconstruction.
Returning to Work
Patients with desk-based occupations often return earlier than those performing physically demanding work.
Return to work depends on:
- Mobility
- Strength
- Fatigue
- Ongoing chemotherapy (if applicable)
- Nature of employment
Sports and Exercise
Regular exercise is encouraged after rehabilitation.
However, high-impact sports such as competitive football, basketball, or long-distance running may not be advisable after certain reconstructions because they increase stress on the implant.
Low-impact activities such as:
- Walking
- Swimming
- Cycling
- Light gym exercises
are commonly recommended after recovery.
Did You Know?
💡 Many patients who undergo limb salvage surgery return to university, employment, travel, recreational sports, and family life after completing rehabilitation.
Possible Complications
Every major operation carries potential risks. Fortunately, most patients recover without major complications.
Possible complications include:
- Infection
- Delayed wound healing
- Blood clots
- Implant loosening
- Mechanical wear of the prosthesis
- Fracture around the implant
- Local recurrence of the tumor
- Need for revision surgery
Not every patient experiences these complications, and regular follow-up allows many problems to be identified and treated early.
Doctor Explains
Does a Complication Mean the Surgery Has Failed?
No.
Many complications can be successfully treated while preserving the reconstruction.
For example:
- Infections may respond to antibiotics and additional surgery.
- Worn implants can often be revised or replaced.
- Fractures around the reconstruction can frequently be repaired.
Early recognition and prompt treatment usually produce the best outcomes.
How Long Does a Tumor Prosthesis Last?
This is one of the most common questions patients ask.
Unlike natural bone, no artificial implant lasts forever.
The lifespan of a tumor prosthesis depends on several factors, including:
- Patient age
- Activity level
- Tumor location
- Implant design
- Body weight
- Previous infection
- Mechanical loading over time
Many modern prostheses function well for many years, but some patients may eventually require revision surgery because of wear, loosening, or mechanical failure.
Importantly, needing a revision operation does not mean the original surgery was unsuccessful. It is often a consequence of long-term implant use, particularly in younger and more active patients.
Doctor Insight
Tumor prostheses are designed to restore mobility and quality of life over many years. When counselling patients, it is important to balance optimism with realism—most reconstructions perform well, but younger patients should understand that future revision surgery may eventually become necessary.
What Does Life Look Like After Limb Salvage Surgery?
Most patients gradually regain independence and return to many of the activities they enjoyed before treatment.
Although recovery requires patience and commitment, many people go on to:
- Walk independently
- Return to school or work
- Travel
- Drive
- Participate in recreational exercise
- Live active, fulfilling lives
Recovery is measured in months rather than weeks, and improvement often continues for a year or longer after surgery.
Frequently Asked Questions (FAQs)
1. What is limb salvage surgery?
Limb salvage surgery is a specialized cancer operation that removes a bone or soft tissue tumor while preserving the affected arm or leg whenever it is safe to do so. After removing the tumor, the bone is reconstructed using a prosthesis, bone graft, or another reconstructive technique.
2. Is limb salvage better than amputation?
Neither procedure is universally better. The best option is the one that completely removes the tumor while providing the safest and most functional long-term outcome. Your surgeon will recommend the approach that best suits your individual situation.
3. Can everyone undergo limb salvage surgery?
No. Suitability depends on factors such as the type of tumor, its location, involvement of nearby nerves or blood vessels, expected function after reconstruction, and your overall health.
4. What is a mega prosthesis?
A mega prosthesis (tumor prosthesis) is a specialized metallic implant used to replace the section of bone and joint removed during tumor surgery. It is commonly used around the knee, hip, and shoulder.
5. How long does limb salvage surgery take?
The duration varies depending on the complexity of the operation and the type of reconstruction. Your surgical team can provide a more accurate estimate based on your individual case.
6. How long will I stay in the hospital?
Hospital stay depends on the type of surgery, your recovery, pain control, wound healing, and progress with physiotherapy. Your healthcare team will decide when it is safe for you to return home.
7. Will I be able to walk again?
Most patients gradually regain the ability to walk after rehabilitation. The timeline depends on the location of the surgery, the reconstruction performed, muscle strength, and physiotherapy progress.
8. Will I need physiotherapy?
Yes. Physiotherapy is an essential part of recovery and helps restore movement, strength, balance, and confidence. The programme is individualized according to your surgery and functional goals.
9. Can I climb stairs after limb salvage surgery?
Most patients can climb stairs after rehabilitation, although this may take several weeks or months depending on the operation and muscle recovery.
10. When can I drive after surgery?
Driving can usually be resumed once you have adequate strength, control, and reaction time, and your surgeon confirms that it is safe to do so. Recovery time varies depending on which limb was operated upon.
11. Can I travel after limb salvage surgery?
Yes. Once you have recovered and your surgeon approves, most patients can travel safely. During long journeys, it is important to move your legs regularly, stay hydrated, and follow your doctor’s advice regarding blood clot prevention.
12. Will airport security detect my implant?
Possibly. Metal implants may activate airport security scanners. Carrying a summary of your surgery or implant information can be helpful, although modern airport security procedures do not always require documentation.
13. Can I undergo MRI after a tumor prosthesis?
In many cases, yes. Modern tumor prostheses are generally MRI compatible, although the implant may create image artefacts around the operated area. Always inform the radiology team about your implant before undergoing MRI.
14. How long does a tumor prosthesis last?
There is no fixed lifespan. Modern tumor prostheses often function well for many years, but longevity depends on age, activity level, implant design, and individual circumstances. Some patients may eventually require revision surgery.
15. Will I need another operation in the future?
Not necessarily. However, younger and more active patients have a greater likelihood of requiring revision surgery during their lifetime because of implant wear or mechanical failure.
16. Can the cancer come back after limb salvage surgery?
Yes. Although complete tumor removal reduces the risk of local recurrence, no treatment can eliminate the risk entirely. Regular follow-up is essential for early detection of recurrence.
17. Is limb salvage surgery painful?
Pain is expected after any major operation, but modern pain management techniques help keep patients comfortable. Pain gradually improves as healing progresses and rehabilitation advances.
18. Can children undergo limb salvage surgery?
Yes. Many children with bone tumors can undergo limb salvage surgery. In selected cases, expandable prostheses or biological reconstruction techniques are used to accommodate future growth.
19. Should I seek a second opinion before amputation?
Seeking a second opinion is reasonable, particularly if amputation has been recommended. An orthopaedic oncology specialist can review your imaging and pathology to determine whether limb salvage is a safe option.
20. What is the most important factor for a successful outcome?
The best outcomes are achieved when treatment is provided by an experienced multidisciplinary sarcoma team, the tumor is completely removed, rehabilitation is completed, and regular follow-up is maintained.
Myths and Facts
When Should You Consult an Orthopaedic Oncologist?
You should seek evaluation by an orthopaedic oncologist if:
- A bone tumor is suspected on X-ray or MRI.
- You have persistent bone pain with an unexplained swelling.
- A biopsy has confirmed a bone or soft tissue tumor.
- Limb salvage surgery or amputation has been recommended.
- You would like a second opinion before major surgery.
- A previous reconstruction has become painful or unstable.
- There are concerns about recurrence after treatment.
Early referral to a specialist centre allows comprehensive evaluation and helps ensure that surgery is planned appropriately from the outset.
Is It Worth Seeking a Specialist Opinion?
Yes.
Limb salvage surgery requires careful planning and experience. If you have been diagnosed with a bone tumor or advised to undergo amputation, consultation with an orthopaedic oncologist can help you understand all available treatment options and make an informed decision based on current evidence and your individual circumstances.
References
This article is based on current evidence and internationally recognized guidance, including:
- National Comprehensive Cancer Network (NCCN). Bone Cancer Guidelines (latest available version).
- ESMO–EURACAN–GENTURIS Clinical Practice Guidelines for Bone Sarcomas.
- World Health Organization (WHO). WHO Classification of Soft Tissue and Bone Tumours, 5th Edition.
- Musculoskeletal Tumor Society (MSTS). Educational resources and consensus recommendations.
- International Society of Limb Salvage (ISOLS). Educational resources and consensus statements.
- American Academy of Orthopaedic Surgeons (AAOS). Relevant educational guidance on limb reconstruction and orthopaedic oncology.
- British Sarcoma Group. Clinical management guidelines.
- Journal of Bone and Joint Surgery (JBJS).
- Clinical Orthopaedics and Related Research (CORR).
- Bone & Joint Journal.
- Journal of Clinical Oncology.
- The Lancet Oncology.
- Medical Review: This page should be reviewed regularly to incorporate advances in reconstructive techniques, implant technology, and international sarcoma guidelines.
Medical Disclaimer
The information provided on this page is intended for educational purposes only and should not replace consultation with a qualified healthcare professional. Every patient with a bone or soft tissue tumor has unique clinical circumstances, and treatment decisions should be individualized after careful assessment by a multidisciplinary sarcoma team.
If you have persistent bone pain, a suspected bone tumor, or have been advised to undergo limb salvage surgery or amputation, consult an experienced orthopaedic oncologist. Early specialist evaluation helps ensure accurate diagnosis, appropriate treatment planning, and the best opportunity for long-term cancer control and functional recovery.
About the Author
Dr. Love Kapoor, MS (Orthopaedics), Fellowship in Musculoskeletal Oncology (AIIMS, New Delhi), Former Assistant Professor, Orthopaedic Oncology, AIIMS, New Delhi.
Orthopaedic Oncologist specializing in bone tumors, soft tissue sarcomas, limb salvage surgery, bone reconstruction, mega prosthesis surgery, and metastatic bone disease.
Meet Your Orthopaedic Oncologist
Choosing treatment for a bone or soft tissue tumor often involves complex decisions. An orthopaedic oncologist specializes in diagnosing and treating tumors affecting the bones, joints, and soft tissues while working closely with medical oncologists, radiation oncologists, radiologists, pathologists, plastic surgeons, vascular surgeons, physiotherapists, and rehabilitation specialists.
Dr. Love Kapoor is an orthopaedic oncologist with dedicated fellowship training in musculoskeletal oncology. His clinical practice focuses on:
- Primary bone tumors
- Soft tissue sarcomas
- Limb salvage surgery
- Bone reconstruction
- Mega prosthesis surgery
- Management of metastatic bone disease
- Complex revision surgery after tumor reconstruction
His approach emphasizes:
- Accurate diagnosis before treatment
- Multidisciplinary decision-making
- Evidence-based care
- Limb preservation whenever oncologically safe
- Personalized treatment planning
- Long-term functional recovery
If you have been diagnosed with a bone tumor, have been advised to undergo amputation, or would like a second opinion regarding limb salvage surgery, consultation with an experienced orthopaedic oncologist can help you better understand your treatment options.
 +91 93558 33005

