Quick Answer
A benign bone tumor is a non-cancerous growth within a bone. Unlike malignant (cancerous) bone tumors, benign tumors do not spread (metastasize) to other parts of the body. Many benign bone tumors are discovered incidentally on X-rays or MRI scans and never require treatment. Others may need treatment if they cause pain, weaken the bone, increase the risk of fracture, interfere with joint function, or continue to grow.
Treatment is individualized and may include observation (active surveillance), medications, minimally invasive procedures such as radiofrequency ablation (heat treatment that destroys the tumor), or surgery. Surgical treatment often involves curettage (scraping the tumor out of the bone), followed by filling the resulting cavity with bone graft or bone cement to restore strength. With appropriate treatment and follow-up, most people recover well, maintain normal function, and enjoy an excellent quality of life.
Quick Summary
What You Need to Know
- Most benign bone tumors are not cancer and do not spread to other organs.
- Not every benign bone tumor requires treatment—many can be safely monitored with regular imaging.
- Treatment depends on the type of tumor, its location, symptoms, size, and risk of weakening the bone.
- When surgery is needed, limb-preserving procedures are almost always possible.
- Modern techniques aim to remove the tumor while preserving as much healthy bone as possible.
- Most patients recover well and return to normal daily activities after treatment.
- Regular follow-up helps detect recurrence early and ensures the bone heals properly.
Reassurance Box
Being told that you have a bone tumor can be frightening. However, the word “tumor” simply means an abnormal growth of tissue—it does not automatically mean cancer. Most benign bone tumors have an excellent prognosis, and many never require surgery.
What Is a Benign Bone Tumor?
A benign bone tumor is an abnormal growth of bone, cartilage, fibrous tissue, or other cells within a bone that is not cancerous. Unlike malignant bone tumors, benign tumors usually grow slowly, remain confined to their original location, and do not spread to other parts of the body.
Although they are called “tumors,” many benign bone tumors behave more like developmental or reactive conditions than true cancers. Some remain unchanged for years, while others gradually enlarge or weaken the surrounding bone.
Benign bone tumors can occur at any age, although certain tumors are more common in children, adolescents, or young adults because the skeleton is still growing. Others are more frequently diagnosed in adults, often as an incidental finding during imaging performed for an unrelated injury or medical problem.
Most benign bone tumors arise in the long bones, such as the femur (thigh bone), tibia (shin bone), and humerus (upper arm bone), but they can develop in almost any bone, including the pelvis, spine, hands, and feet.
Common Benign Bone Tumors
*Although giant cell tumor of bone is classified as a benign tumor, it is locally aggressive, meaning it can destroy nearby bone and has a higher risk of recurrence than most other benign bone tumors.
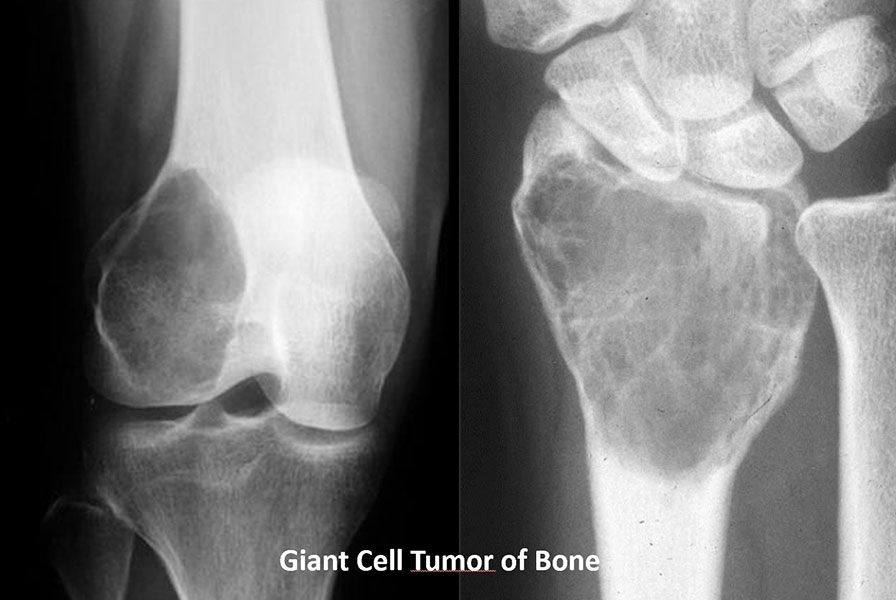
Figure 1. Giant cell tumor at common locations
X-rays showing giant cell tumors at some of their common locations around the knee and wrist.
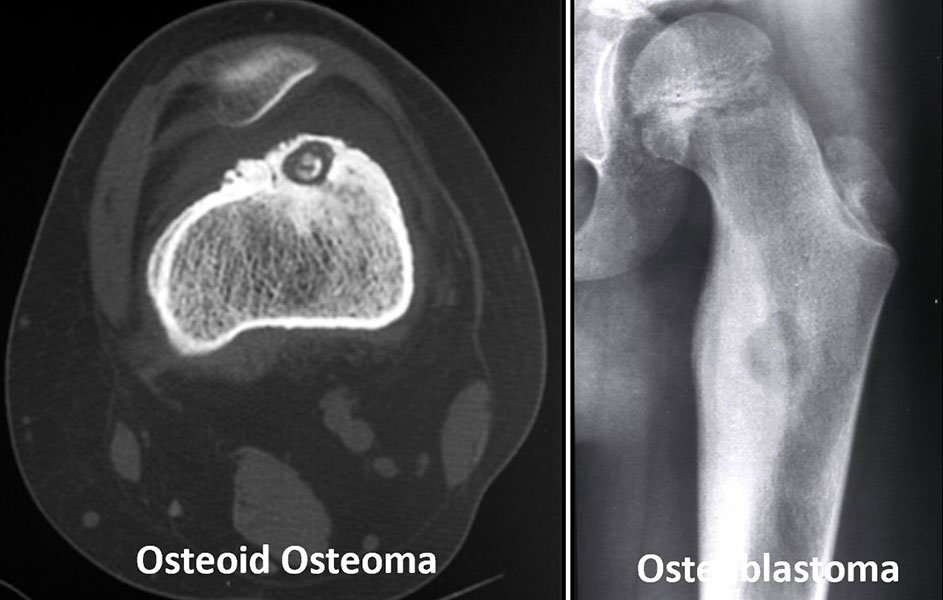
Figure 2. Osteoid osteoma and osteoblastoma
Examples of two benign bone tumors that can cause persistent or troublesome bone pain.
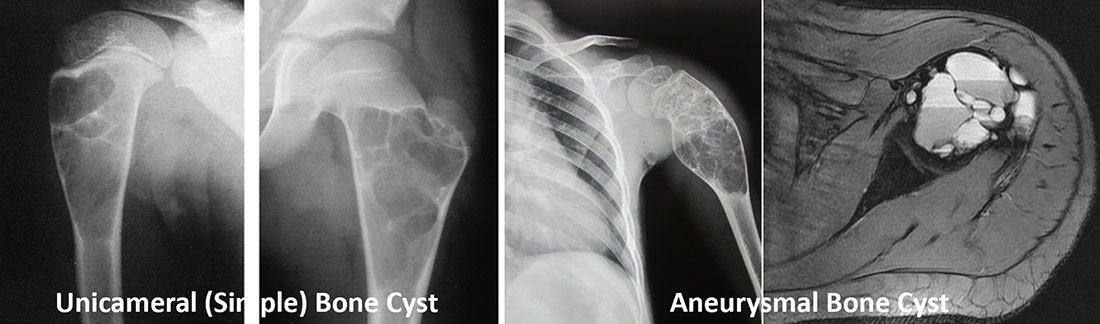
Figure 3. Simple and aneurysmal bone cysts
Imaging examples of two types of benign bone cysts that can weaken the bone and sometimes increase the risk of fracture.
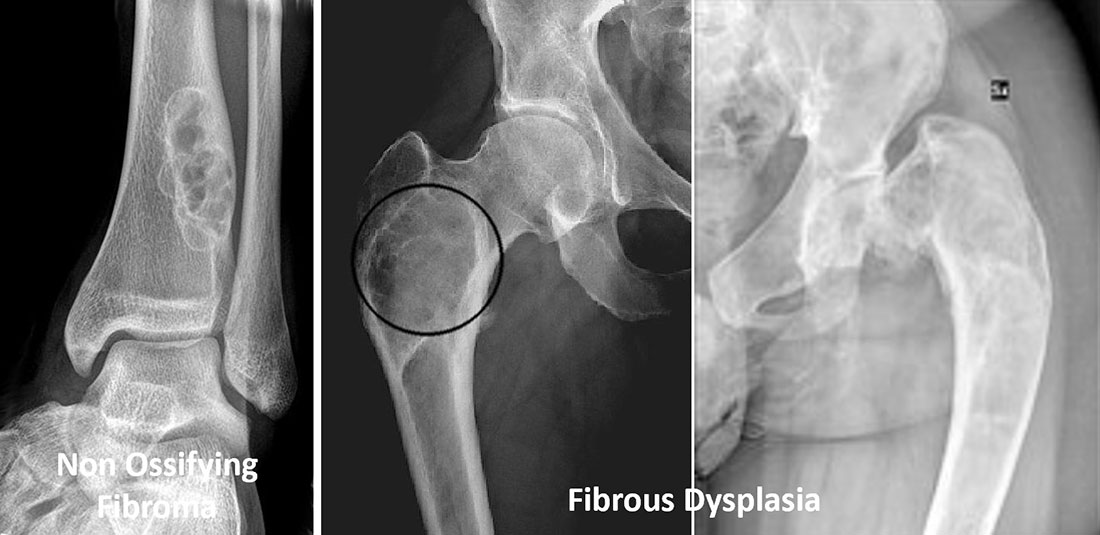
Figure 4. Non-ossifying fibroma and fibrous dysplasia
Examples of common benign bone conditions that are often found incidentally but may occasionally require treatment.
Doctor Explains
The term “benign” means that a tumor does not spread to distant organs like lung, liver, or brain. However, benign does not always mean harmless. Some benign bone tumors can enlarge, weaken the bone, cause fractures, or damage nearby joints if left untreated. This is why every bone tumor deserves careful evaluation.
How Is a Benign Bone Tumor Different from Bone Cancer?
Many patients immediately associate the word “tumor” with cancer. In reality, most bone tumors encountered in clinical practice are benign.
The key differences are shown below.
Benign Bone Tumor vs Malignant Bone Tumor
It is important to remember that imaging alone cannot always determine whether a bone tumor is benign or malignant. Some benign tumors can appear aggressive on scans, while some malignant tumors may initially look harmless. When uncertainty exists, additional imaging or a biopsy—a procedure in which a small tissue sample is removed for microscopic examination—may be recommended before deciding on treatment.
Clinical Pearl
A bone tumor should never be labeled as benign based solely on an X-ray if the imaging features are uncertain. Correlating the patient’s age, symptoms, imaging findings, and, when necessary, biopsy results leads to the most accurate diagnosis.
Do All Benign Bone Tumors Need Treatment?
One of the most common misconceptions is that every bone tumor must be removed surgically. In fact, many benign bone tumors never require an operation.
Some tumors remain stable throughout life, cause no symptoms, and are discovered purely by chance. In these situations, the safest approach is often active surveillance, also called observation, where the tumor is monitored with periodic clinical examinations and imaging to ensure it remains unchanged.
Treatment becomes necessary when the tumor:
- Causes persistent pain.
- Continues to enlarge.
- Weakens the bone and increases the risk of a pathological fracture (a bone break occurring through diseased bone).
- Interferes with joint movement or normal function.
- Compresses nearby nerves or blood vessels.
- Has imaging features suggesting a more aggressive lesion.
- Cannot be confidently diagnosed without tissue examination.
Choosing observation is not the same as ignoring the tumor. Instead, it is a carefully planned strategy supported by clinical evidence and regular follow-up.
Doctor Insight
One of the most important principles in orthopaedic oncology is treating the patient—not just the X-ray. An incidental benign lesion that is causing no symptoms often does not benefit from surgery, whereas a smaller lesion causing pain or weakening the bone may require treatment.
Patient Tip
If your doctor recommends observation, ask:
- How often should I have follow-up imaging?
- What symptoms should prompt an earlier review?
- What activities, if any, should I avoid?
Understanding the follow-up plan can help you feel confident and involved in your care.
Goals of Treatment
The treatment of benign bone tumors is individualized, meaning it is tailored to the specific tumor and the needs of each patient. The objective is not simply to remove the tumor, but to preserve bone strength, maintain function, relieve symptoms, and minimize the risk of recurrence while avoiding unnecessary treatment.
The main goals are to:
- Relieve pain and improve quality of life.
- Prevent pathological fractures.
- Preserve healthy bone, joints, and surrounding muscles.
- Maintain normal movement and limb function.
- Confirm the diagnosis when uncertainty exists.
- Reduce the chance of recurrence in tumors that are more aggressive.
- Enable patients to return safely to work, school, sports, and everyday activities.
Clinical Pearl
Successful treatment is measured not only by removing the tumor but also by how well the patient regains function and quality of life.
How Is Treatment Planned?
No single treatment works for every benign bone tumor. Before recommending observation, a minimally invasive procedure, or surgery, your healthcare team carefully evaluates several factors to determine the safest and most effective approach.
Treatment planning begins with answering three important questions:
- Is the tumor truly benign?
- Does it require treatment at all?
- If treatment is needed, which option will provide the best long-term outcome with the least risk?
The evaluation usually includes:
Medical History
Your doctor will ask about the onset of pain, swelling, previous injuries, activity-related symptoms, and whether the symptoms are worsening. Certain tumors, such as osteoid osteoma, have characteristic patterns—for example, pain that is worse at night and relieved by anti-inflammatory medicines.
Physical Examination
The affected limb is examined for tenderness, swelling, deformity, joint movement, muscle strength, nerve function, and signs that the bone may be weakened.
Imaging Studies
Imaging is the foundation of diagnosis.
- X-ray is usually the first investigation and often provides enough information to identify many benign tumors.
- Magnetic Resonance Imaging (MRI) uses magnetic fields to produce detailed images of bone marrow and surrounding soft tissues, helping define the tumor’s exact extent.
- Computed Tomography (CT) provides detailed images of bone architecture and is particularly useful for certain tumors such as osteoid osteoma.
- In selected situations, additional investigations such as a bone scan or PET-CT may be recommended.
Biopsy
A biopsy is a procedure in which a small sample of tissue is removed and examined under a microscope by a pathologist. It is not required for every benign bone tumor, especially when the imaging appearance is characteristic. However, if the diagnosis remains uncertain or the lesion appears aggressive, a biopsy may be essential before treatment.
Biopsy in Bone & Soft Tissue Tumors
Multidisciplinary Team (MDT)
Complex cases are best managed by a multidisciplinary team (MDT) comprising orthopaedic oncologists, musculoskeletal radiologists, pathologists, medical oncologists when needed, and physiotherapists. Combining expertise from different specialists improves diagnostic accuracy and helps select the most appropriate treatment.
Doctor Explains
The decision to treat a benign bone tumor is based on the whole clinical picture, not on imaging alone. Your age, symptoms, examination findings, imaging, and, when necessary, biopsy results all contribute to choosing the safest and most effective treatment plan.
Treatment Options for Benign Bone Tumors
The treatment of a benign bone tumor depends on its type, location, size, symptoms, biological behavior, and the risk it poses to the surrounding bone. While some tumors can be safely monitored for years, others require treatment to relieve pain, prevent fractures, preserve joint function, or reduce the risk of recurrence.
The good news is that most benign bone tumors can be treated successfully while preserving the affected limb and maintaining excellent long-term function.
Doctor Insight
The goal is not to remove every benign tumor, but to choose the treatment that provides the greatest benefit with the least risk. In many patients, avoiding unnecessary surgery is just as important as performing surgery well.
Observation (Active Surveillance)
Many patients are surprised to learn that the best treatment for some benign bone tumors is no immediate treatment at all.
Active surveillance, also called observation, means the tumor is monitored through regular clinical examinations and imaging rather than being removed immediately. This approach is recommended only when there is strong evidence that the lesion is benign and unlikely to cause problems.
Observation avoids unnecessary surgery while allowing doctors to detect any significant changes early.
Who Can Be Safely Observed?
Observation is often appropriate for patients who have:
- No pain or only mild symptoms.
- A tumor with a typical benign appearance on imaging.
- A stable lesion that is not increasing in size.
- Low risk of weakening the bone.
- No interference with nearby joints or muscles.
Common examples include many:
- Enchondromas
- Non-ossifying fibromas
- Small osteochondromas
- Fibrous cortical defects
Some tumors in children may even become less noticeable as the skeleton matures.
What Happens During Follow-up?
The frequency of follow-up depends on the tumor type, patient age, and imaging findings.
A typical surveillance program may include:
- Periodic clinical examinations.
- Repeat X-rays to monitor size and appearance.
- MRI only if symptoms change or imaging becomes concerning.
Most tumors remain stable over time, allowing patients to continue normal activities without intervention.
Patient Tip
Keep copies of your previous X-rays and MRI scans. Comparing current images with earlier studies often helps your doctor determine whether the tumor has changed over time.
Reassurance Box
Observation does not mean your doctor is ignoring the tumor. It is an evidence-based treatment strategy that avoids unnecessary procedures while ensuring the lesion is monitored carefully.
Medications
Most benign bone tumors cannot be cured with medicines alone, but medications may play an important role in relieving symptoms or managing selected conditions.
Commonly used medications include:
- Non-steroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen or naproxen to reduce pain and inflammation, particularly in osteoid osteoma.
- Bisphosphonates, medicines that reduce bone breakdown, may be used in selected patients with conditions such as fibrous dysplasia.
- Denosumab, a medication that blocks bone destruction, may be considered for selected patients with giant cell tumor of bone, especially when surgery would be difficult or associated with significant functional loss.
Medication is usually combined with observation or surgery rather than replacing these treatments.
Doctor Explains
Medicines can relieve symptoms or help control certain tumors, but they are not appropriate for every benign bone tumor. Your treatment plan depends on the specific diagnosis.
Minimally Invasive Treatments
Advances in imaging and technology have made it possible to treat some benign bone tumors without large surgical incisions. These procedures are usually performed through a small skin puncture under CT or X-ray guidance, resulting in less pain, shorter hospital stays, and faster recovery.
Although not suitable for every tumor, minimally invasive techniques have become the preferred treatment for selected lesions.
Radiofrequency Ablation (RFA)
Radiofrequency ablation (RFA) uses heat generated by high-frequency electrical energy to destroy the tumor.
A thin needle-like probe is accurately placed into the tumor under CT guidance. Heat is then applied to destroy the abnormal tissue while preserving the surrounding healthy bone.
RFA has become the treatment of choice for most osteoid osteomas, offering excellent pain relief with a success rate exceeding 90% in experienced centers.
Most patients return home the same day and resume normal activities within a few days.
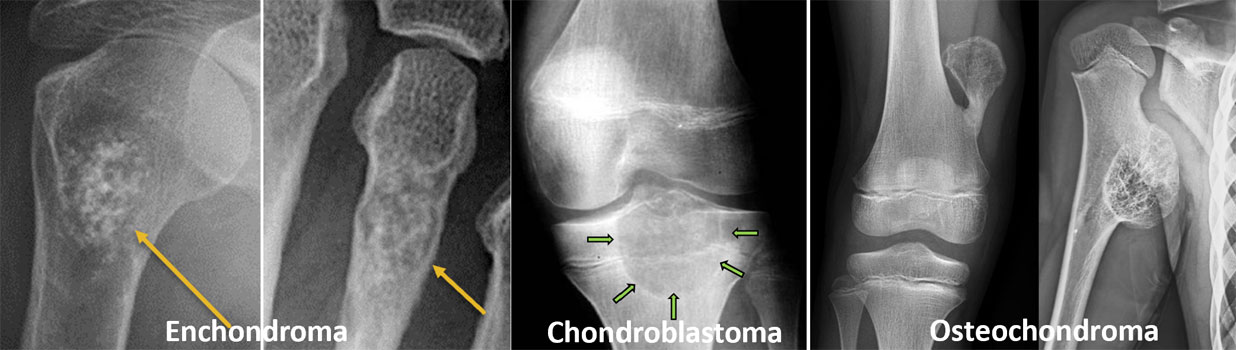
Figure 5. Various chondroid bone tumors: X-ray images illustrating common cartilage-forming bone tumors, including enchondroma, chondroblastoma, and osteochondroma
Cryoablation
Cryoablation destroys abnormal tissue by exposing it to extremely low temperatures.
Although less commonly used than RFA, it may be appropriate for selected benign tumors located near important nerves or joints where controlled freezing offers certain technical advantages.
Other Percutaneous Treatments
Depending on the diagnosis, some tumors may also be treated using:
- Image-guided injections
- Percutaneous drilling
- Sclerotherapy (injecting medicines that shrink cystic lesions)
- Microwave ablation in selected cases
These techniques continue to evolve and are available in specialized musculoskeletal oncology centers.
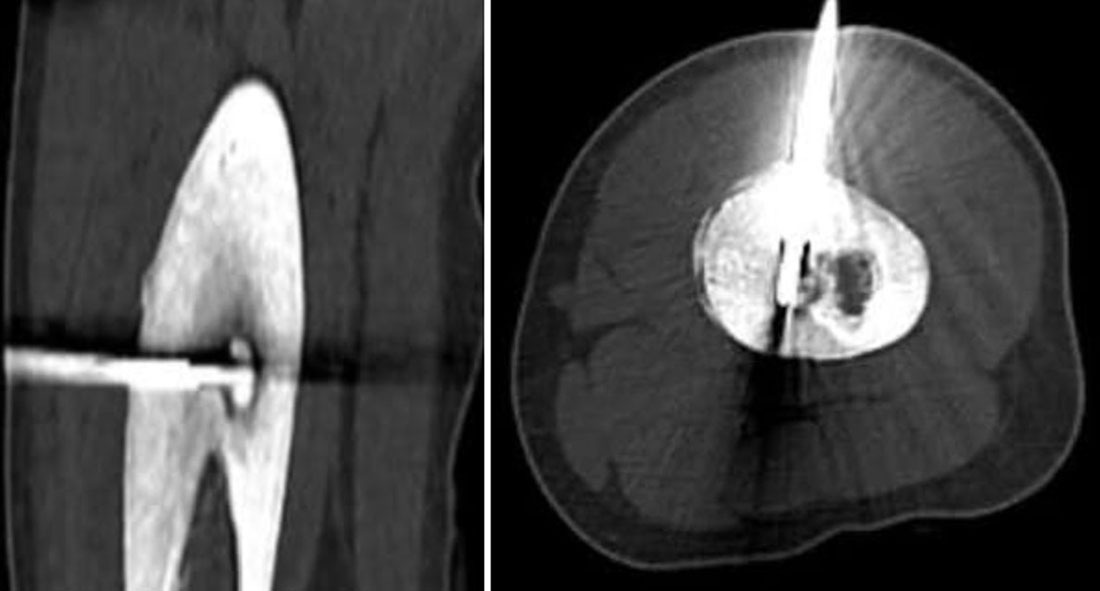
Figure 6. Biopsy of a bone tumor.
A CT-guided biopsy helps doctors identify exactly what type of bone tumor is present before deciding on the most appropriate treatment.
Minimally Invasive Treatment vs Open Surgery
Doctor Insight
Today, many patients with osteoid osteoma can be treated through a tiny skin puncture rather than undergoing traditional open surgery—a major advance in orthopaedic oncology.
Surgery for Benign Bone Tumors
Surgery is recommended only when its benefits clearly outweigh its risks. The aim is to remove the tumor while preserving as much normal bone, joint function, and surrounding soft tissue as possible.
Common reasons for surgery include:
- Persistent pain despite conservative treatment.
- Progressive enlargement of the tumor.
- Increased risk of a pathological fracture.
- Functional limitation.
- Compression of nearby nerves or blood vessels.
- A locally aggressive tumor with a higher chance of recurrence.
- Diagnostic uncertainty requiring tissue confirmation.
The type of surgery depends on the tumor’s biological behavior rather than simply its size.
Curettage
Curettage is the most commonly performed operation for many benign bone tumors.
During this procedure, the surgeon creates a small opening in the bone and carefully scrapes out the tumor using specialized instruments. A high-speed burr (a rapidly rotating surgical drill) is often used afterward to remove microscopic tumor cells from the cavity and reduce the risk of recurrence.
Once the tumor has been removed, the remaining cavity is usually filled with bone graft, bone cement, or another bone substitute to restore strength.
Title: Steps of Curettage
- Bone opened
- Tumor removed
- High-speed burr used
- Bone cavity filled
- Bone heals
Doctor Explains
Curettage removes the tumor from inside the bone, allowing the healthy outer shell of the bone to be preserved. This makes it one of the most effective limb-preserving procedures for many benign bone tumors.
Extended Curettage
Some tumors, particularly giant cell tumor of bone and aneurysmal bone cyst, have a higher tendency to recur after simple curettage.
In these situations, surgeons perform extended curettage, which combines curettage with additional techniques called local adjuvants. These treatments destroy microscopic tumor cells that may remain after scraping.
Local adjuvants may include:
- High-speed burr
- Phenol
- Hydrogen peroxide
- Liquid nitrogen (cryotherapy)
- Argon beam coagulation (in selected centers)
Using these techniques can significantly reduce the risk of recurrence while preserving the joint.
Clinical Pearl
For many aggressive benign tumors, extended curettage provides excellent local control while avoiding the need for more extensive bone removal.
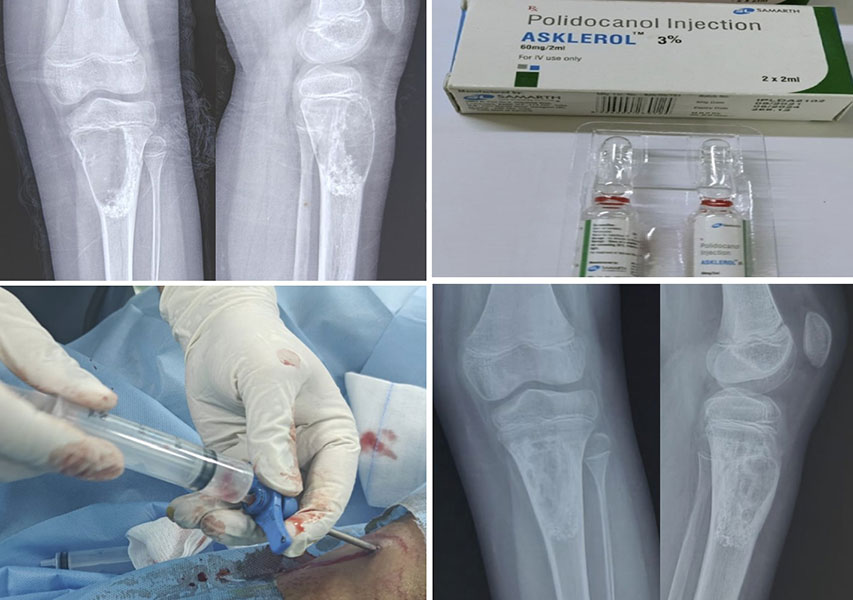
Figure 7. Treating an aneurysmal bone cyst without open surgery
An aneurysmal bone cyst being treated with sclerotherapy, a minimally invasive procedure that helps the cyst heal gradually.
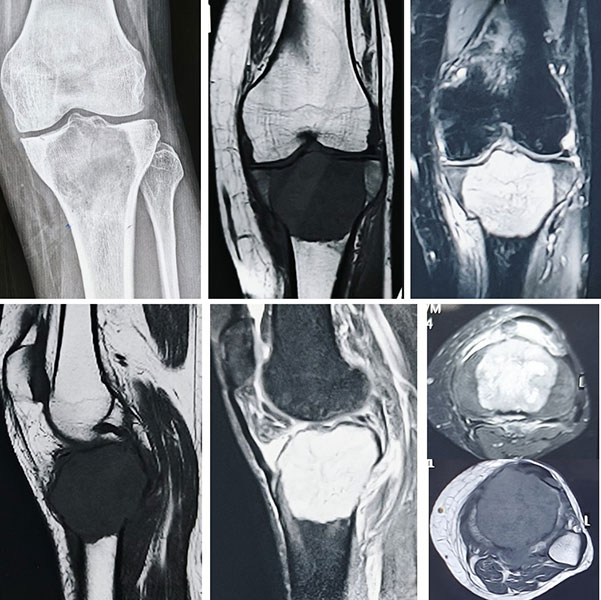
Figure 8A. Giant cell tumor around the knee
X-rays and MRI showing a giant cell tumor near the knee, helping the surgical team understand the size and extent of the tumor before treatment.
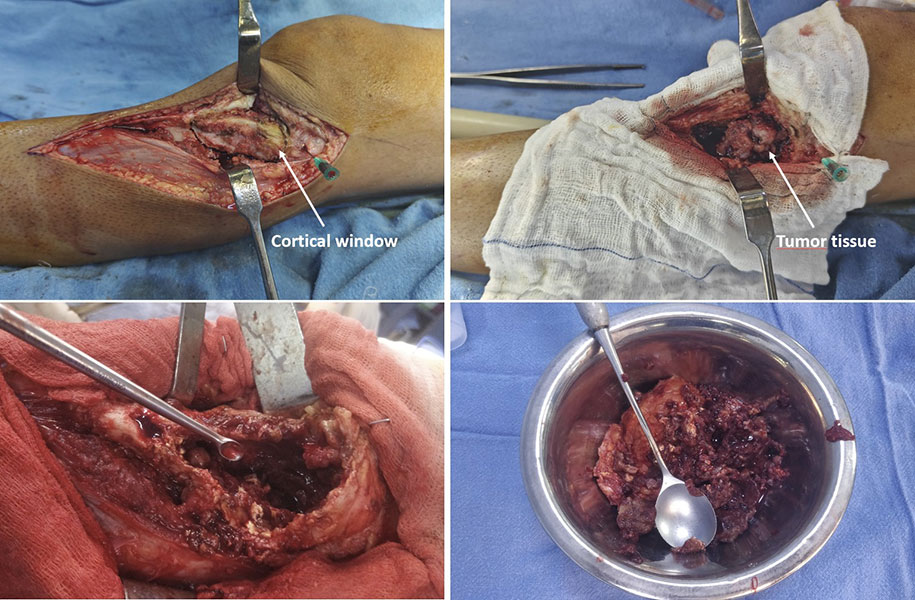
Figure 8B. Removing the tumor from inside the bone
Curettage involves carefully removing the tumor from inside the bone while preserving the surrounding healthy bone.
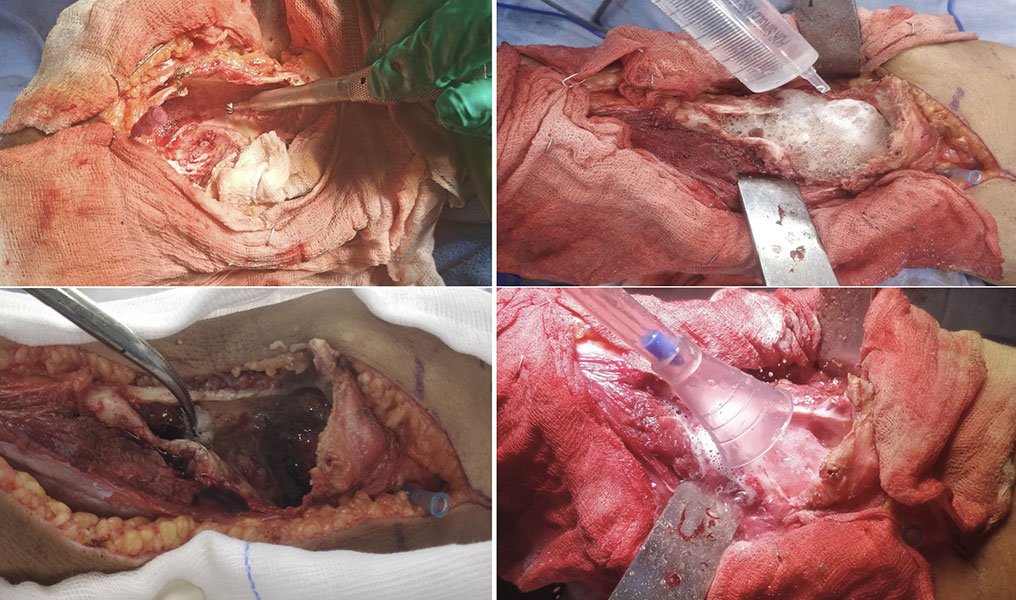
Figure 8C. Reducing the chance of tumor coming back
After curettage, additional techniques such as a high-speed burr, chemical agents and thorough washing are used to clean the cavity and reduce the risk of recurrence.
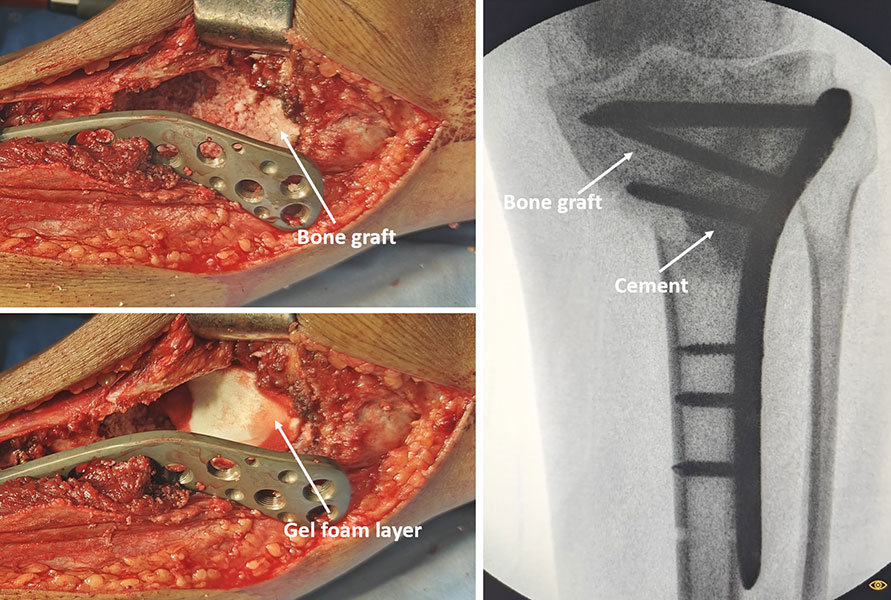
Figure 8D. Rebuilding the bone after tumor removal
The cavity left after removing the tumor is filled with bone graft and/or bone cement, with fixation used when needed to restore strength and stability.
Bone Grafting
After curettage, a cavity remains inside the bone. Bone grafting fills this space, supports healing, and helps restore bone strength.
Bone grafts may come from:
- Autograft — bone taken from another part of the patient’s own body.
- Allograft — donor bone obtained from a certified bone bank.
- Synthetic bone substitutes — laboratory-manufactured materials that gradually integrate with natural bone.
The choice depends on the size of the defect, patient age, tumor type, and surgeon preference.
Bone Cement
Instead of bone graft, surgeons may fill the cavity with bone cement, most commonly polymethyl methacrylate (PMMA)—a strong material that hardens within minutes.
Bone cement provides immediate structural support and allows earlier weight-bearing in many patients. The heat generated during curing may also destroy residual tumor cells, potentially lowering recurrence in selected tumors such as giant cell tumor of bone.
Bone Graft vs Bone Cement
Doctor Explains
Bone cement is not an artificial bone replacement. Instead, it acts like a strong filler that supports the bone after tumor removal. Your surgeon will recommend bone graft or cement based on your individual condition.
Internal Fixation
Sometimes the bone remains weak even after the tumor has been removed. In these cases, internal fixation may be required.
Internal fixation uses plates, screws, rods, or nails to stabilize the bone and reduce the risk of fracture while healing occurs.
Not every patient needs internal fixation. The decision depends on:
- Size of the bone defect.
- Bone quality.
- Tumor location.
- Patient activity level.
Plates and Screws Supporting Bone Healing
En Bloc Excision
Some benign tumors are too aggressive to be treated effectively with curettage alone.
En bloc excision involves removing the tumor in one piece along with a small margin of surrounding healthy tissue. Although this procedure may reduce recurrence, it also removes more normal bone and may require more complex reconstruction.
It is usually reserved for selected tumors where preserving the bone with curettage is unlikely to provide durable disease control.
Doctor Insight
Modern orthopaedic oncology emphasizes preserving bone whenever it is safe to do so. En bloc excision is recommended only when it offers a clear advantage over less extensive surgery.
Reassurance Box
Most patients with benign bone tumors do not require removal of an entire bone or limb. Advances in surgical techniques now allow surgeons to preserve normal anatomy while achieving excellent long-term outcomes.
Recovery After Treatment
Recovery after treatment for a benign bone tumor varies depending on the type of tumor, the treatment performed, the location of the lesion, and the patient’s age and overall health. Some patients undergoing minimally invasive procedures return to normal activities within a few days, while those who undergo reconstructive surgery may require several months of rehabilitation.
Recovery should be viewed as a gradual process rather than a single event. The focus is not only on healing the bone but also on restoring strength, movement, confidence, and quality of life.
Doctor Explains
Successful treatment does not end when surgery is completed. Recovery continues through rehabilitation, bone healing, and regular follow-up until you can safely return to your normal activities.
Hospital Recovery
The length of hospital stay depends on the procedure performed.
- Patients treated with radiofrequency ablation (RFA) or other minimally invasive procedures are often discharged the same day or within 24 hours.
- After curettage or bone grafting, patients usually remain in the hospital for a few days.
- More extensive reconstructive procedures may require a longer stay, particularly if internal fixation or large bone defects are involved.
Pain is managed using a combination of medications, and movement is encouraged as early as it is safe to do so.
Walking and Weight-Bearing
Whether you can put weight on the affected limb immediately depends on how much bone was removed and how the defect was reconstructed.
Some patients can walk with full weight-bearing shortly after surgery, particularly if bone cement has been used. Others may need crutches or a walker for several weeks while the bone heals.
Your surgeon will provide individualized instructions based on the stability of the reconstruction.
Clinical Pearl
Following weight-bearing restrictions is one of the most important factors in preventing postoperative fractures and ensuring successful healing.
Physiotherapy
Physiotherapy (physical rehabilitation to restore strength, movement, and function) is an essential part of recovery for many patients.
A structured rehabilitation program may include:
- Improving joint movement.
- Restoring muscle strength.
- Improving balance and coordination.
- Gait training (learning to walk normally again).
- Gradual return to work, sports, and daily activities.
The duration of physiotherapy varies from a few weeks after minimally invasive procedures to several months following complex surgery.
Returning to Daily Activities
Most patients gradually resume normal activities as pain decreases and bone healing progresses.
Typical recovery milestones vary depending on the procedure:
General Recovery Timeline
*Recovery varies according to the type of tumor, surgery performed, and individual healing.
High-impact sports or heavy lifting may need to be delayed until the bone has healed completely.
Patient Tip
It is normal to recover at a different pace from someone with the same diagnosis. Focus on steady progress rather than comparing your recovery with others.
Returning to School and Sports
Children can usually return to school once they are comfortable, mobile, and no longer require strong pain medication.
Participation in sports depends on:
- The location of the tumor.
- Bone strength.
- The type of reconstruction.
- The risk of fracture.
Low-impact activities are often resumed earlier, whereas contact sports may need to be postponed until complete bone healing.
Did You Know?
After successful treatment, most children and adults can return to an active lifestyle, although some high-impact activities may need to be modified to protect the treated bone.
Reassurance Box
Most patients recover well after treatment for a benign bone tumor. Although healing takes time, the majority regain good function and return to work, school, and everyday activities.
Long-Term Follow-up
Even after successful treatment, regular follow-up remains an important part of care.
Follow-up allows your healthcare team to:
- Confirm that the bone has healed properly.
- Monitor any bone graft or reconstruction.
- Detect recurrence early in tumors with a higher recurrence risk.
- Identify complications before they become serious.
The frequency of follow-up depends on the type of tumor and treatment performed.
Patients who undergo observation generally require periodic imaging to confirm that the lesion remains stable, whereas those treated surgically are monitored until healing is complete and then at longer intervals.
Typical Follow-up Schedule*
*The schedule varies depending on the diagnosis and your surgeon’s recommendations.
Doctor Insight
Most recurrences, when they occur, are detected during routine follow-up before they cause significant symptoms. Keeping scheduled appointments is an important part of successful treatment.
Possible Complications
Serious complications after treatment for benign bone tumors are uncommon, particularly when treatment is performed in experienced centers. However, every procedure carries some degree of risk.
Potential complications include:
Surgical Complications
- Infection.
- Bleeding.
- Delayed wound healing.
- Injury to nearby nerves or blood vessels.
- Blood clots (rare).
Bone-Related Complications
- Delayed bone healing.
- Pathological fracture.
- Failure of internal fixation.
- Bone graft not incorporating fully.
- Mechanical problems with implants.
Tumor-Related Complications
Some benign tumors—particularly giant cell tumor of bone and aneurysmal bone cyst—have a higher likelihood of recurring after treatment. Recurrence does not mean that the tumor has become cancerous, but it may require further treatment.
Possible Complications and Their Management
Red Flag Box
Contact your healthcare team promptly if you develop:
- Increasing pain after initial improvement.
- Fever or chills.
- Redness, swelling, or discharge from the surgical wound.
- Sudden inability to bear weight.
- New numbness or weakness.
Early assessment can often prevent more serious complications.
Reassurance Box
Most patients do not experience major complications, and when complications occur, they can often be treated successfully if recognized early.
Prognosis
The outlook for patients with benign bone tumors is generally excellent.
Most benign tumors do not affect life expectancy, and the majority of patients return to normal work, school, sports, and family life after treatment or observation.
The prognosis depends on several factors, including:
- The specific type of tumor.
- Its location.
- Whether the bone was weakened before treatment.
- The type of treatment performed.
- The likelihood of recurrence.
Some tumors, such as osteoid osteoma, are almost always cured after treatment. Others, including giant cell tumor of bone, require closer long-term follow-up because of a higher recurrence risk.
Doctor Insight
For most patients, the greatest challenge is recovering from treatment—not living with the tumor itself. With appropriate care, long-term function and quality of life are usually excellent.
Did You Know?
Most benign bone tumors never spread to other organs and do not shorten life expectancy.
When Should You See an Orthopaedic Oncologist?
Although many benign bone tumors can be managed successfully, some situations require assessment by an orthopaedic oncologist—a surgeon with specialized training in diagnosing and treating bone and soft tissue tumors.
You should consider referral if:
- The diagnosis is uncertain.
- Imaging suggests a locally aggressive lesion.
- Surgery may involve a joint or major bone.
- The tumor has recurred.
- A pathological fracture has occurred.
- A biopsy is being considered.
- Complex reconstruction may be required.
Early referral helps ensure that the diagnosis, biopsy, and treatment are carefully planned from the beginning.
Clinical Pearl
A well-planned first operation offers the best chance of preserving bone, joint function, and long-term outcomes.
Frequently Asked Questions (FAQs)
1. Can a benign bone tumor become cancer?
Most benign bone tumors never become cancerous. However, a few rare tumors have a very small risk of malignant transformation. Your doctor will explain if your specific diagnosis requires long-term monitoring.
2. Do all benign bone tumors require surgery?
No. Many benign bone tumors remain stable throughout life and can be managed safely with regular observation and imaging. Surgery is recommended only when the tumor causes symptoms, weakens the bone, grows, or has a higher risk of recurrence.
3. Can a benign bone tumor disappear on its own?
Some lesions in children, such as certain bone cysts or non-ossifying fibromas, may improve or resolve as the skeleton matures. Most benign tumors, however, remain stable rather than disappearing completely.
4. Is a biopsy always necessary?
No. Many benign bone tumors have characteristic appearances on X-rays or MRI scans and do not require biopsy. A biopsy is usually recommended only when the diagnosis is uncertain or imaging suggests a more aggressive lesion.
5. What is curettage?
Curettage is an operation in which the surgeon removes the tumor by carefully scraping it out from inside the bone. The remaining cavity is then filled with bone graft, bone cement, or another bone substitute to restore strength.
6. What is the difference between bone graft and bone cement?
A bone graft gradually becomes living bone as it heals, whereas bone cement provides immediate structural support but does not become living bone. The choice depends on the tumor type, location, patient age, and the size of the bone defect.
7. Can I walk after surgery?
Most patients can walk again after surgery, although some may need crutches or a walker temporarily. Your surgeon will advise when it is safe to bear weight based on the type of procedure performed.
8. Can I return to sports?
Yes, many patients eventually return to sports. The timing depends on bone healing, the location of the tumor, and the type of treatment. High-impact sports may need to be delayed until complete healing has occurred.
9. Can benign bone tumors come back after treatment?
Some tumors, particularly giant cell tumor of bone and aneurysmal bone cyst, have a higher risk of recurrence. Most recurrences can be detected early during follow-up and treated successfully.
10. How long will I need follow-up?
The duration of follow-up depends on the diagnosis. Some patients require only a few months of monitoring, while others with more aggressive benign tumors may benefit from periodic follow-up for several years.
11. Should I seek a second opinion?
A second opinion can be valuable when:
- The diagnosis is uncertain.
- Surgery has been recommended.
- The tumor is close to a major joint.
- Reconstruction may be required.
- You have concerns about the proposed treatment plan.
12. Can children with benign bone tumors grow normally?
In most cases, yes. If treatment involves a growth plate, your surgeon will monitor limb growth carefully during follow-up. Most children continue to lead active, healthy lives after treatment.
13. Are benign bone tumors hereditary?
Most benign bone tumors occur sporadically and are not inherited. However, a few rare conditions, such as multiple hereditary exostoses, have a genetic basis and may affect several family members.
14. Can a bone injury cause a benign bone tumor?
No. Injuries do not cause benign bone tumors. Minor trauma may draw attention to an existing lesion by prompting an X-ray, leading to its incidental discovery.
15. What is the long-term outlook?
The long-term prognosis for most patients is excellent. The majority regain normal function, maintain good quality of life, and do not experience any reduction in life expectancy.
References
- World Health Organization. WHO Classification of Soft Tissue and Bone Tumours. 5th ed. Lyon, France: International Agency for Research on Cancer (IARC); 2020.
- NCCN Clinical Practice Guidelines in Oncology (NCCN Guidelines®). Bone Cancer. National Comprehensive Cancer Network. Latest available version.
- Kapoor, L., Kumar, V.S. and Khan, S.A., 2026. Limb Salvage Surgery in Bone Tumors. CRC Press, Taylor and Francis Group.
- Campanacci M. Bone and Soft Tissue Tumors. 2nd ed. Vienna: Springer-Verlag; 1999.
- Gibbs CP Jr, Peabody TD, Simon MA. Principles of Musculoskeletal Oncology. In: Campbell’s Operative Orthopaedics. 14th ed. Elsevier; 2021.
- Enneking WF. Musculoskeletal Tumor Surgery. New York: Churchill Livingstone; 1983.
- American Academy of Orthopaedic Surgeons (AAOS). OrthoInfo: Bone Tumors. Available at:
- Musculoskeletal Tumor Society (MSTS). Clinical Resources and Educational Materials. Available at:
- International Society of Limb Salvage (ISOLS). Consensus Statements and Educational Resources. Available at:
Medical Disclaimer
The information provided in this article is intended for educational purposes only and should not replace professional medical advice, diagnosis, or treatment. Every benign bone tumor is unique, and treatment decisions depend on the type of tumor, its location, symptoms, imaging findings, and individual patient factors. Always consult a qualified orthopaedic oncologist or your healthcare provider for personalized medical advice. Never ignore professional medical guidance or delay seeking medical attention because of information you have read online.
 +91 93558 33005

